
Health
Mak Researchers Partner with Safe Bangle Technologies to Roll out a Real-Time Domestic Violence Reporting Bracelet


By Joseph Odoi
A Consortium of Researchers from Makerere University School of Public Health/Resilient Africa Network (MakSPH/RAN), Medical College of Wisconsin (MCW), Somero Uganda together with Safe Bangle Technologies have rolled out a real time domestic violence reporting bracelet.
This roll out was made possible with support from the United States Agency for International Development (USAID) under the PARTNERSHIPS FOR ENHANCED ENGAGEMENT IN RESEARCH (PEER) program and the National Academies of Sciences.
Dr. Juliet Kiguli, the Principal Investigator from Makerere University, along with Dr. Roy Mayega, Deputy Chief of Party at RAN, and Dr. Agnes Nyabigambo, the study coordinator, initiated the PEER program to identify entry points for testing SafeBangle Technologies (a social enterprise based at Resilient Africa Network (RAN) with a mission to create a safer and more secure environment for women and children through innovative, affordable, and creative technology solutions to curb GBV in Africa.) wearable safety bracelet in the informal settlements. This decision stemmed from findings of increased intimate partner violence (IPV) and gender-based violence (GBV) in three informal settlements in Kampala, Uganda, following a longitudinal study, geospatial mapping, and interviews. The project, titled ‘The Impact of the COVID-19 Pandemic on Gender-Based Violence among Women and Girls in Informal Settlements in Kampala,’ highlighted the urgent need for affordable and immediate reporting mechanisms for violence.”
‘’While carrying out a study after the Covid-19 Pandemic, we identified gaps when it comes to reporting and response to Gender Based Violence (GBV) among women in informal settlements. Therefore, we used incorporated the SafeBangle intervention to solve the problem of lack of affordable and immediate reporting mechanisms for violence using a bracelet that reports violence in real time’’ explained Dr. Kiguli.
Innovation details
According to Saul Kabali and Messach Luminsa, the innovators behind SafeBangle from SafeBangle Technologies, hosted at the Resilient African Network Lab. ‘’The inspiration behind SafeBangle came from a deeply personal place. ‘’We heard countless stories of women who couldn’t call for help during moments of danger. We were deeply affected by the story of Aisha, a young woman in a rural village who was attacked while walking home alone at night. With no way to call for help, she felt helpless and vulnerable. This incident made us realize the critical need for immediate reporting alert tools, accessible to women like Aisha. We knew technology could play a crucial role and this incident awakened a strong desire in us to create a solution’’

“While developing SafeBangle, we tested with the users in both rural and urban contexts. We piloted the innovation around Kampala with support from Digital Human Righs Lab and Naguru Youth Health Network as well as it in five districts of Karamoja region with support from Save the Children and Response Innovation Lab. Right now it has become handy in Kamapala‘s informal settlements. We envision a future where SafeBangle becomes a standard tool in the fight against GBV, ensuring every woman feels safe and secure as it has the potential to transform how we respond to GBV in Africa” added Kabali.
HOW THE SAFEBANGLE TECHNOLOGY WORKS
The SafeBangle is wearable technology similar to a smartwatch that sends an alarm by SMS to people chosen by a woman herself if she feels threatened.

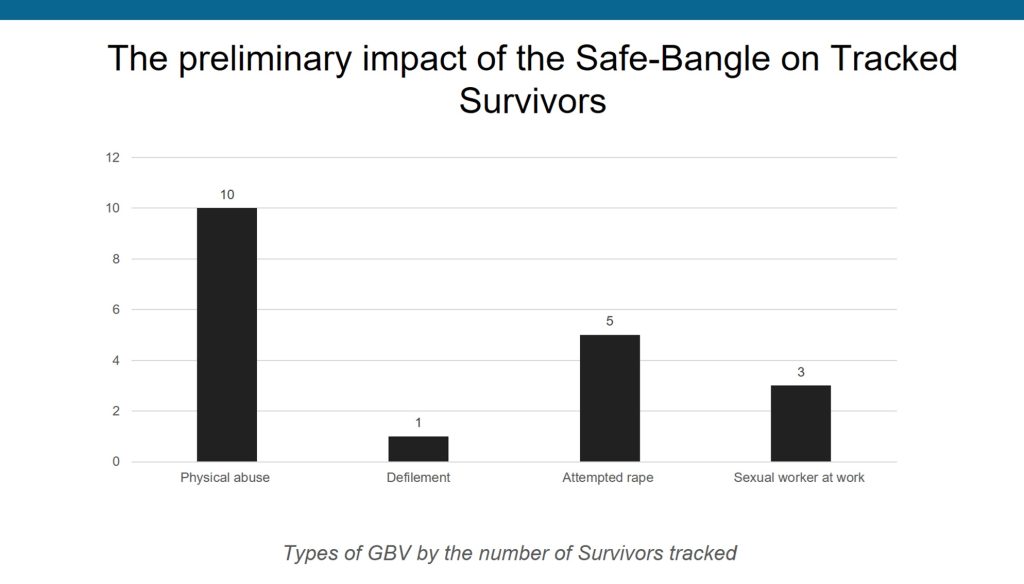
In terms of the acceptability of the SafeBangle innovation as a solution to GBV among at-risk women in informal settlements Of the 72 adolescent girls and women who received the SafeBangle, 22 activated the reporting button, resulting in 19 receiving immediate and appropriate support, including counseling, police intervention, and health services.
All adolescent girls and women who experienced GBV received a phone call from Somero Uganda to discuss the most appropriate intervention, including counseling, police cases being handled by the probation office, referral for health services, and post-exposure prophylaxis. All the GBV survivors received support and are still receiving continuous follow-up.
Researchers conducted a survey among 644 girls and women in Kinawataka (Nakawa Division) and Bwaise (Kawempe Division) to gain insights into awareness and understanding of sexual and gender-based violence among adolescent girls and women in informal settlements. The survey measured socioeconomic factors, mental health symptoms, and exposure to GBV. Focus group interviews were conducted with a separate sample of women over 18 in the settlements to explore responses to GBV.
A tabular representation of the key findings and lessons learned from your study on gender-based violence (GBV)
| Key Findings | Lessons learned |
| Prevalence of GBV. – Overall prevalence: 34.1% of women and girls reported experiencing GBV. – Among adolescents (15-19 years): Over 50% reported experiencing GBV. | – The pandemic highlighted the need for accessible and comprehensive support services for GBV survivors. – Schools emerged as crucial safe spaces for girls, emphasizing their well-being during crises. – Economic independence proved crucial, enabling women to leave abusive environments. – Involving men and boys as allies in GBV prevention efforts is essential. |
| Age-related trends | – GBV prevalence tends to decrease with increasing age. |
| Physical and health consequences. | – Women and girls suffered physical violence, injuries, and deaths, primarily from domestic violence and unsafe abortions due to limited healthcare access. – GBV resulted in unintended pregnancies, unsafe abortions, and increased risk of sexually transmitted diseases (STIs) like HIV/AIDS. |
| Social and economic impact. . | – GBV contributed to family breakups, strained marriages due to financial stress. – Economic hardships forced some women and girls into transactional sex, exposing them to further health risks and exploitation. – Pandemic-related job losses and economic constraints increased financial dependence on abusers, trapping women in violent situations. – School closures and increased household responsibilities limited women’s job opportunities and subjected them to sexual harassment. |
| Psychological effects | – Survivors experienced guilt, shame, anxiety, fear, and suicidal thoughts due to ongoing abuse. |
| Long-term effects | – Post-COVID-19, survivors faced disrupted education, early marriages, pregnancies, social stigma, and persistent mental health issues. |
Reproductive Health Consequences: GBV resulted in unintended pregnancies, unsafe abortions, and increased risk of sexually transmitted diseases (STIs) like HIV/AIDS.
Family Breakdown: The rise in GBV led to family breakups as women fled abusive relationships. Marriages were strained due to increased financial stress.
Transactional Sex for Survival: Desperate for basic needs due to job losses and economic hardship, some women and girls resorted to transactional sex, exposing them to further health risks and exploitation.
One study participant stated, “The time of COVID-19 was so terrible for some of us. We in fact got a lot of diseases from it because you would want to get food and didn’t have money. That way you would be forced to get a man who would use you and pay.” – (FGD_Girls_19–24years_Kinawataka).
Economic Effects: COVID-19 restrictions caused job losses and limited economic opportunities, particularly for women in the informal sector. This increased financial dependence on abusers and trapped women in violent situations.
Limited Access to Employment: School closures and increased household chores limited women’s ability to seek employment, perpetuating gender inequality in the workforce. Some faced sexual harassment from potential employers.
Psychological Effects: Survivors of GBV experienced guilt, shame, anxiety, fear, and even suicidal thoughts due to the constant threat and unpredictability of abuse.
Post-COVID Effects: GBV survivors faced long-term consequences, including disrupted education, early marriage, early pregnancy, social stigma, and persistent mental health issues.
Lessons learned
The pandemic highlighted the need for accessible and comprehensive support services for survivors of GBV, the significance of schools as safe spaces for girls, and the need to prioritize their well-being during crises. Economic empowerment emerged as a significant protective factor for women and girls. Those with greater economic independence were better equipped to leave abusive environments and secure their safety and well-being, while dependent ones suffered abuses. Engaging men and boys as allies in the fight against GBV and involving them in prevention efforts can help promote positive behavior change and foster more equitable relationships.
Recommendations
To address GBV against women and girls, the researchers recommend the following moving forward;
- There is need to integrate technology-driven solutions like SafeBangle into national GBV prevention and response strategies. SafeBangle can be a valuable tool for policymakers as cases of violence that would have gone unreported will be brought to light and the would-be victims will be able to get immediate help from trusted relatives and friends.
- Provide economic opportunities and vocational training for women and girls to enhance their financial independence and reduce vulnerability to violence. There is therefore a need to introduce education and training programs that empower women and girls, by providing them with skills, resources, and opportunities to start their own ventures and to participate fully in community affairs.
- Strengthen and enforce existing laws and policies related to GBV, including laws against domestic violence, child marriage, and sexual assault without discrimination be it for law enforcers, leaders, and employers where such cases were suffocated. Ensure that perpetrators are held accountable through swift and fair legal processes that have no room for corruption.
- Establish and promote effective, accessible, and confidential reporting mechanisms for GBV incidents that provide confidence and can be trusted by survivors to enhance reporting of such incidences of GBV. Community Engagement and Involvement: Involve community leaders, religious leaders, and elders in discussions about GBV to promote gender equality, change social norms, and reinforce the message that violence against women and girls is unacceptable.
- Launch extensive public awareness campaigns to challenge harmful gender norms, report cases of GBV, raise awareness about the consequences of GBV, and promote positive behaviors and attitudes towards women and girls.
- Implement comprehensive sexuality education in schools and communities, educating young people about healthy relationships, consent, and reproductive rights to be able to make informed decisions about their own lives and well-being.
- Engage men and boys as allies in the fight against GBV, encouraging them to challenge harmful masculinity norms and behaviors. This will help minimize GBV because mostly they are the perpetrators. Strengthening Support for Survivors: Provide ongoing support and follow-up services for survivors of GBV mostly counselling services to aid their recovery and facilitate their reintegration into society.
- Provide ongoing support and follow-up services for survivors of GBV, mostly counseling services to aid their recovery and facilitate their reintegration into society.
- Provide avenues to seek free or subsidized services by survivors of GBV medical services and legal processes by survivors of GBV to enhance reporting of GBV cases, access to medical care, counseling, legal support, and other essential services.
- Encourage and support more research and innovations like SafeBangle to curb incidents of GBV.
- A comprehensive and inclusive approach is required. The efforts should involve government institutions, civil society organizations, community leaders, and individuals working together to address the root causes and provide support to survivors.
- Involve media in GBV prevention activities and for enhancing campaigns against GBV mostly on radio and TV.
MORE ABOUT THE STUDY
The core project team, included researchers at Makerere University School of Public Health (MakSPH), Medical College of Wisconsin (MCW) led by Prof. Julia Dickson-Gomez, SafeBangle Technologies, and Somero Uganda, a community-focused NGO, began the project by designing their research protocol and taking a CITI Program course on human subjects social/behavioral research. Team members also met with the Ministry of Gender, Labour, and Social Development (MGLSG) in support of the gender-based violence policy process, Ministry of Health and local government. They also established relationships with the Kampala Capital City Authority (KCCA) and Nakawa and Kawempe probation offices to support legal processes for the GBV survivors. SafeBangle Team also received an award from Defenders Protection Initiative.















Prof. David Guwatudde, Principal Investigator (centre), and Dr. Justine Bukenya with researchers and stakeholders at the ARISE-NUTRINT dissemination meeting in Iganga, 1 October 2026.
Adolescence is a consequential period for health, when diets, behaviours and other risks can form and persist into adulthood. In Mayuge District, new evidence from Makerere University School of Public Health is showing how some of these early vulnerabilities could contribute to the later risk of non-communicable diseases (NCDs), and what can change when interventions begin early.
The evidence comes from the ARISE-NUTRINT project, a three-year EU-funded study led by Prof. David Guwatudde and Dr. Justine Bukenya. The project examines health and behavioural risks among adolescents and young adults, with a particular focus on nutrition-related NCD risks, and tests interventions designed to improve nutrition fluency and diet quality.
The work comes against a substantial NCD burden in a country where 73.2% of the population is below 30. WHO estimates that NCDs accounted for 42.2% of deaths in Uganda in 2023, while the country’s latest national NCD risk-factor survey found significant risk factors persisting in the population, with little overall change from the previous survey in 2014. Together, the evidence strengthens the case for prevention much earlier in life.
“There is strong evidence from literature demonstrating that most behavioral NCD risk factors, including nutrition-related, are established during childhood, persisting into adulthood. This may lead to development of actual NCDs if such risks are not reversed early,” Prof. Guwatudde said.
The study, he explained, linked assessment of young people’s health risks with developing responses suited to their circumstances. Since enrolling 1,206 participants aged 10–24 in Mayuge District in March 2024, the team has conducted three annual rounds of data collection, with young people and local stakeholders also helping evaluate interventions to reduce the risks identified.

A problem that starts early
The findings, shared with community and district stakeholders in Iganga on October 1, 2026, show that some vulnerabilities were already evident at baseline. Nearly one in three participants had anaemia, 49% had low nutrition literacy, while about one in ten reported symptoms of anxiety and a similar proportion reported depressive symptoms.
Anaemia, a condition in which the blood does not have enough healthy red blood cells or haemoglobin to carry adequate oxygen around the body, was highest among the youngest participants. Overall, 375, or 31%, had anaemia, rising to 35.7 per cent among 10–14-year-olds, compared with 18.9% among those aged 15–19 and 10.6 per cent among young adults aged 20–24.
Nutrition presented another challenge. At baseline, 49% of participants had low nutrition literacy and 13% had poor overall diet quality. Low nutrition literacy was associated with more than four times the odds of poor diet quality.
Gaps also emerged in sexual and reproductive health knowledge and behaviour. About 14 per cent of participants did not know that HIV cannot be transmitted by sharing food with a person living with HIV, 10% believed a condom could be used more than once, and 13 per cent did not know pregnancy could occur during first sexual intercourse. Among 168 participants who reported having had sex, more than half reported using no method to prevent pregnancy during their first or most recent sexual intercourse.
Mental health findings added another dimension. Anxiety symptoms were reported by 10 per cent of participants, depressive symptoms by 9.5% and loneliness by 6.3 per cent. Among 534 participants aged 13–24 assessed for suicidal ideation, 1.9% reported suicidal thoughts.
Together, the baseline findings show that vulnerabilities extended beyond any single health issue. For nutrition, the study went further to examine what shaped everyday food choices and whether those influences could be changed.
Nutrition literacy goes beyond knowing which foods are healthy. It includes understanding nutrition information and applying it to everyday choices. The study found those choices were also shaped by parents, peers, food vendors, culture, prices, seasons, and what was available locally. Improving diets, therefore, required reaching beyond individual knowledge to the households and communities where food choices are made.
What early action changed
The baseline evidence informed the Adolescent Nutrition Fluency Intervention. Working with adolescents and young adults, caregivers, Community Health Workers (CHWs), district teams and other stakeholders, the project adapted nutrition messages to local foods, language and household realities. Ten trained CHWs delivered nine monthly household sessions covering balanced diets, physical activity, vitamins and minerals, meal planning and anaemia prevention.
The household approach reached young people in and out of school. The nutrition literacy, diet-quality and intervention analyses form part of the PhD research of Mr. Thomas Buyinza, supported through ARISE-NUTRINT. At endline, participants who received the sessions recorded higher nutrition literacy and overall diet-quality scores.
“The improvement in nutrition literacy and diet quality suggests that practical education, grounded in local foods and household realities, can support healthier choices among adolescents and young adults. In addition, involving parents and caregivers is important because they influence what families buy, prepare, and eat,” Dr. Bukenya said.
She stressed that nutrition education needed to be complemented by better access to affordable, nutritious foods. Dr. Bukenya also called for continued follow-up, including the use of nutrition and dietary data from DHIS2, to assess whether improvements were maintained and guide district planning.

Changes in other outcomes were mixed. Participants reporting no physical activity fell from 22.6% to 7.4%, while those active on four to seven days a week increased from 46% to 54.8%. But activity duration did not improve: those reporting more than 60 minutes a day declined from 28.2% to 21.1%. Underweight fell modestly from 6.2% to 5%, while overweight and obesity did not change significantly.
Anaemia recorded the largest change, falling from 31.1% before the intervention to 9.9% afterwards. During the intervention period, participants received weekly iron and folic acid supplementation and deworming alongside nutrition education on iron-rich foods, dietary diversity and practices that improve iron absorption.

Mayuge District’s Assistant District Health Officer, Ms. Elizabeth Kawaala, said the findings reflected problems recognised locally and highlighted the need for a response involving families and other stakeholders.
“There is a serious challenge that needs to be tackled with many stakeholders, with parents at the centre because these are children. We also learnt that many parents, I think, lack the skills to communicate with their adolescents,” she said.

She said the findings had been shared with colleagues and described integrating health education and sensitisation into services. She also called for departments to use the evidence when planning activities in their workplans.
Beyond Mayuge
Seen alongside Uganda’s 2023 STEPS survey, the Mayuge findings add an earlier-life dimension to the national evidence. Makerere University School of Public Health contributed to both studies, with Prof. Guwatudde contributing to the national STEPS survey and now leading ARISE-NUTRINT. While STEPS found significant NCD risk factors persisting among adults, ARISE-NUTRINT shows that some behaviours and vulnerabilities relevant to later NCD risk are already evident during adolescence and young adulthood. The Mayuge research goes further by testing what can change when interventions begin during this period.
The findings leave Mayuge with more than a measure of the problem. They show where vulnerabilities are emerging, what changed when interventions were introduced and where challenges remain. For ARISE-NUTRINT, the evidence now turns attention to which approaches can be sustained and how lessons from Mayuge can inform efforts to support healthier transitions from adolescence into adulthood.



Through a European Union (EU) funded initiative, Makerere University and Mulago Hospital are hosting a German oncology reconstruction specialist Professor Dr. Thiha AUNG. AUNG is a surgeon, trainer at the Deggendorf Institute of Technology (THD), and researcher on cancer from the Deggendorf Institute of Technology (DIT), Germany.
With his international expertise in oncology and medical management roles at his home institution, his visit is a valuable addition to Uganda’s capacity building efforts in medical advancement.
Prof. Aung who arrived in Uganda in late September 2026 and has since then conducted free identified patient specialised surgeries and training for locals. These are expected to span two weeks. For the period, his service intersects medical expertise and humanitarian efforts.
This is not Prof. Aung’s first time in the country; his first major visit was in 2023, when he performed life-changing free surgeries on early patients. He then made medical history in June 2024 when he arrived to perform Africa’s first-ever lymph node transplant at Mulago Hospital.
It was against this background that the Makerere Public Relations Office engaged him in an exclusive interview to share his philosophy on medical service, his experiences in oncology reconstruction, and his unwavering belief that passion and dedication rather than just resources are the true drivers of sustainable medical progress.
Transforming Lives Through Oncology Reconstruction
At the heart of his mission through the ERASMUS – Oncology/Lymphedema project, is the treatment of lymphedema, a condition often referred to as elephantiasis.
In Europe, such surgeries can cost between 80,000 and 100,000 euros, making them inaccessible to many.
Thankfully, Professor and his team, including some of his post graduate students like Anna Friedrich (B.Sc) and Sophia Waser (B.Sc., PA) from the Institute of Medical Science and Engineering, have once again brought this specialised care to Uganda pro bono.

He highlights the story of a teacher who, after receiving surgery, regained her quality of life and returned to the classroom. For him, the impact is exponential. “You change one life, but this person changes a lot in the community.”
This shift from individual surgery to the long-term wellbeing of the community, reinforces the local impact of these services.
Professor AUNG’s Personal Conviction
The professor confessed that inherently, he commands himself that beyond knowledge, true progress is driven by passion and will rather than resources.
He does not agree with those that think money and resources are the sole prerequisite for change in the medical world, stating, “you cannot change with money only.” Rather, he upholds the importance of personal decision and commitment.
When discussing the challenges of working in resource-limited settings, he maintains a simple, direct explanation “it’s always beyond the money.”
Ultimately, the Professor believes that if he can provide the spark, his students and patients can carry through with the same flame for significant change.
Motivation to Serve in Uganda
When asked about his inspiration for entering the field and now volunteering to work in Uganda, he explained that his primary goal was always to serve others. “That’s why I finished my medical school to help as many people as possible with my skills.”

He views his medical expertise not as a tool for the privileged, but as a universal resource., “People are all the same, their anatomy is the same. So, I can help all these people pretty well,” Prof AUNG remarked.
His approach is motivated by a pay it forward dogma where treating a single patient creates a broader societal benefit. He illustrates this through his work with patients who, after surgery, are able to return to their professions like the teacher earlier mentioned.
Tips for Medical Professionals working in Uganda
As a foundation for professional growth, the Professor advised medical professionals working in Uganda to prioritise genuine interest in their work because he believes it is “the most important…” for “if you are interested, you will go far in the profession.”
He further reinforced the human capacity point, noting, “no matter what kind of equipment you have… it all depends on the people operating them and the patient.”
Professor AUNG concluded by encouraging doctors to overcome resource fears through action, stating, “If you want to create impact or change, you do.”
Dr. AUNG is part of the Lymphoedema Warriors Association (LWAU) in Uganda. He describes it as a grassroots organisation and commends them for “leveling the grond”. He reiterated his commitment to work with the organisation in reviewing patient reports to determine the best course of treatment.
-

 General1 week ago
ADVERT: Mature Age Entry Scheme Examinations – 2027/2028
-

 Agriculture & Environment2 weeks ago
What two weeks with Farmers in Mwera, Mityana, taught Makerere’s PhD Students about Agricultural Innovation
-

 General1 week ago
MURBS Presents FY 2025/26 Performance with 15% Growth
-

 General1 week ago
CoNAS Staff & Students Sensitized on Gender Equality, Sexual Harassment Policies
-

 General1 week ago
Gender Sensitization Session to Strengthen Gender-Responsive Practices conducted at CoVAB