
Health
Researchers Design Community-led Behavioural Change Model to Control Rate of Type 2 Diabetes among Rural Population



















Uganda’s push for a dependable medicines supply is tested daily at the health facility, where patients expect to receive what was prescribed.
Meeting that expectation means keeping supplies in step with changing needs and sustaining services when funding arrangements change. Uganda has increased funding for essential medicines and health supplies through National Medical Stores and is supporting local pharmaceutical production, as outlined in the government’s FY2026/27 budget statement.
The evidence comes from a Makerere University School of Public Health (MakSPH) project, Safeguarding Uganda’s Health Supply Chain Amid the Global Health Funding Transition: Immediate Actions and Strategic Analytics for Resilience. The project responded to the 2025 suspension of USAID-supported distribution, which left medicines in storage, at risk of expiry, while facilities waited for deliveries.
Led by Prof. Rhoda Wanyenze and Assoc. Prof. Suzanne Kiwanuka, the nine-month project brought together MakSPH, the Ministry of Health and Joint Medical Store (JMS), with support from the Gates Foundation. It was launched on 6 November 2025 with the flag-off of emergency medicine distribution, and four days later MakSPH convened stakeholders to refine the research questions and align them with national priorities. The findings were presented on 3 November 2026 at a national dissemination and policy dialogue.

What reaches the patient
Assoc. Prof. Kiwanuka, the project’s co-principal investigator, led the last-mile assessment with Mr. Amuzah Nshabaruhanga, covering 70 public and private not-for-profit facilities across 15 districts. Of 632 patients interviewed, 591 had been prescribed medicines, and 208 of them, more than one in three, missed at least one prescribed medicine at the facility. Antibiotics and medicines for high blood pressure were among those missed. Of 346 patients requiring diagnostic services, 36 missed a required service.
“The ultimate measure of our supply chain performance should not only be whether commodities are available in the stores, but whether patients actually receive the medicines and the diagnostic services they need,” Assoc. Prof. Kiwanuka said.

Patients said they would buy missing medicines privately, making the ability to pay part of access to treatment. Regional referral hospitals recorded the lowest average annual stock-out rate among the facility levels assessed, at 11.2%, yet 53.5% of their surveyed patients who were prescribed medicines missed at least one. The stock-out rate tracked selected commodities during 2025; patient interviews captured prescription fulfilment during a visit.
Matching supplies with need
Part of the explanation lies in a mismatch between what facilities hold and what they need. A review of 2025 records for 29 tracer commodities found an overall stock-out rate of 15 per cent, measured as the share of days commodities were unavailable. On assessment day, only 13.2% of commodity stocks were at the recommended level: 17.4 per cent were unavailable, 31.7% understocked, and 37.8 per cent overstocked.
The assessment recorded 2,791 redistribution transactions in 2025. Health Centre IIIs and regional referral hospitals were net providers; Health Centre IVs and general hospitals were net recipients. Transfers required staff to locate stock, secure approvals, and arrange transport, often without a dedicated budget. They addressed imbalances linked to mismatched supply kits, restricted order adjustments, delivery delays, and changing demand, highlighting the need for better forecasting and allocation.
Financing dependable delivery

Getting medicines to the facilities that need them also requires reliable delivery funding. Ms. Brenda Nakimuli and Mr. Perez Ochanda’s financing analysis found that the gap between money committed and the estimated cost of essential medicines and health supplies narrowed from 21.7% in FY2022/23 to 1.8% in FY2025/26.
That improvement did not mean every facility had enough funding to order the medicines it needed. These allocations remained UGX99.3 billion below estimated need, while reproductive-health and nutrition supplies also faced shortfalls. Money committed, moreover, is not necessarily money released or spent. Funding for storage, delivery, stock reporting, supervision and staff was spread across budgets, though these costs continue after medicines are bought.
Dr. Catherine Birabwa and Dr. Beatrice Namirembe examined local pharmaceutical manufacturing as part of their assessment of selected supply-chain interventions. Manufacturers and other stakeholders described high operating costs, lengthy product clearance, reliance on foreign expertise, limited technology transfer, and competition from cheaper imports. Local production serves patients only if affordable, quality-assured medicines are procured and delivered where they are needed.
Making information useful
Funding alone does not keep shelves stocked; the system also needs reliable information. Ms. Purity Mukisa of JMS described how the emergency response combined distribution with ordering support, technical supervision, retrieval of expired commodities, and facility mapping. It reached 1,072 facilities and enabled distribution of residual commodities worth approximately US$4.2 million.

“If orders are not coming in, then people cannot have the items that they need. And also we will have expiries because we don’t even know whether the items are being utilised,” Ms. Mukisa said.
Stock reviews also flag products nearing expiry or supplies that could be moved elsewhere. Dr. Birabwa and Dr. Namirembe also examined digital systems, medicines governance and supportive supervision. Health workers described easier ordering, tracking and reporting, but disconnected platforms, inadequate training, unreliable connectivity and delayed technical support limited those gains.
Still, the last-mile assessment by Assoc. Prof. Kiwanuka and Mr. Nshabaruhanga identified difficulties in the electronic medical record system, including automatic stock deduction, batch and expiry management, reporting and communication with other systems. Inaccurate electronic balances can distort later orders. In some facilities, paper requisition tools were withdrawn before electronic processes were fully operational.

Joint Medical Store identified 423 facilities in its network without computers. At one Kampala facility, the team found that the staff member responsible for submitting orders relied on their daughter’s help. Orders did not come through when the daughter was away.
The interventions assessment linked functioning Medicines and Therapeutics Committees and supportive supervision with better ordering, stock management, and accountability. The committees guide medicine selection, prescribing, and monitoring; the Supervision, Performance Assessment and Recognition Strategy (SPARS) provides mentorship and assessment. Funding gaps, staff turnover, and transport constraints weakened both. Donor withdrawal disrupted SPARS, while fragmented implementation weakened the link between digital self-assessment and targeted supervision.
Sustaining the improvements
Each strand of research identifies specific priorities for action. The fiscal-space analysis proposes protecting funding for a minimum package covering distribution, storage, supervision, and stock reporting. The last-mile assessment calls for allocating supplies using consumption data and providing dependable funding for redistribution. The interventions assessment recommends linking medicines committees, digital self-assessment, and supportive supervision so that identified gaps lead to corrective action.
Dr. Charles Olaro, Director General of Health Services, said the research findings had already been presented to the Ministry’s top management. He called for follow-up to identify which recommendations could be put into practice to improve the health supply system.

Prof. Rhoda Wanyenze, MakSPH’s Dean and the project’s principal investigator, thanked the Ministry of Health and Joint Medical Store for a partnership she described as excellent. She called for continued collaboration to improve access to medicines and connect the School’s training with the practical demands of delivering essential services.
“As researchers and academics, we need to remain involved in building a resilient and sustainable system. We have a responsibility to nurture the next generation of health workers. The people who will sustain these systems go through our hands. Working together helps us better appreciate the real-world challenges we expose our students to, so that we can send out a better workforce to support the Ministry of Health and other actors in health,” she said.
The project began with medicines awaiting delivery. Its longer-term value will depend on whether institutions assign responsibility and sustain funding for the work that keeps facilities supplied. For patients, progress becomes tangible when prescribed medicines can be dispensed and required tests performed, without another journey or an additional purchase elsewhere to complete their care.

This week, world leaders, negotiators and researchers are gathered in Antalya, Türkiye, for COP31, the United Nations climate conference, seeking to turn years of climate commitments into action countries can finance and implement. Among them is Dr. John Bosco Isunju, a climate and health researcher at Makerere University School of Public Health, named among TIME’s 100 most influential climate leaders in 2024.
Dr. Isunju led the School’s technical support to the Ministry of Health for Uganda’s 2023 Climate Change Health Vulnerability and Adaptation Assessment (VAA) and the subsequent development of the Health National Adaptation Plan (H-NAP) 2025–2030. The assessment covered 716 health facilities across 43 districts, documenting vulnerabilities that helped shape the country’s priorities for protecting healthcare from climate hazards.

That experience speaks directly to the task before the 9–20 November summit. With “Dynamic and Resilient Health Systems” among the COP31 Presidency’s Action Agenda priorities, the conference is seeking practical solutions and financing to keep services functioning through climate shocks. Adaptation, the practical changes needed to cope with a changing climate, must ultimately reach the facilities where people seek care.
Protecting facilities from floods and drought also safeguards the public investment behind them, giving Uganda’s adaptation effort an economic significance alongside its importance to patients. In a 27 October 2026 statement ahead of COP31, UN Climate Change Executive Secretary Simon Stiell placed climate action within that wider calculation of public benefit.
“More governments are taking climate action right across their economies, to bank the vast benefits of clean energy and climate resilience,” he said. “Almost every major economy, and many medium-sized and smaller economies, now see climate action as a central driver of economic growth, jobs, and affordable and secure energy.”

On 21 October, nearly three weeks before the Antalya talks, the H-NAP was before Ugandan parliamentarians in Kampala. Convened by the Ministry of Health and Parliamentary Forum on Climate Change Uganda, with support from Regenerate Africa and the Clinton Health Access Initiative, the engagement examined the plan and Parliament’s role in securing funding, scrutinising implementation and ensuring accountability.
Presenting the VAA, Dr. Isunju explained that the team examined the hazards facing each area, the extent of exposure and the weaknesses that made services vulnerable. They also considered the communities the facilities served. A flood could turn an already difficult journey to treatment into one that patients and staff could no longer make, as seen in many parts of Uganda, including Kasese.
“Either health workers will not work, or communities will not be able to access care, or outreaches will not be possible because roads are cut off,” he told legislators.

Uganda’s H-NAP grew out of commitments made at COP26 in Glasgow in 2021 to assess health vulnerabilities and develop an adaptation response. The Ministry of Health commissioned the School to undertake the VAA in 2023, with Rockefeller Foundation funding supporting both the assessment and the plan’s development. Developed through stakeholder consultation, with WHO technical support and contributions from other partners, the plan was launched on 22 August 2024.
What the assessment found
The VAA found that drought and floods were disrupting the conditions needed to deliver care. Nearly half of the assessed facilities reported drought exposure, while about two in five reported floods. Among the 284 facilities reporting flood exposure, 141 (about half) said health professionals had been unable to arrive at or leave their workplaces, and 198 (about seven in ten) reported shortages of safe water. Because districts were selected for their history of hazards, these findings describe the assessed facilities and cannot be treated as national estimates.
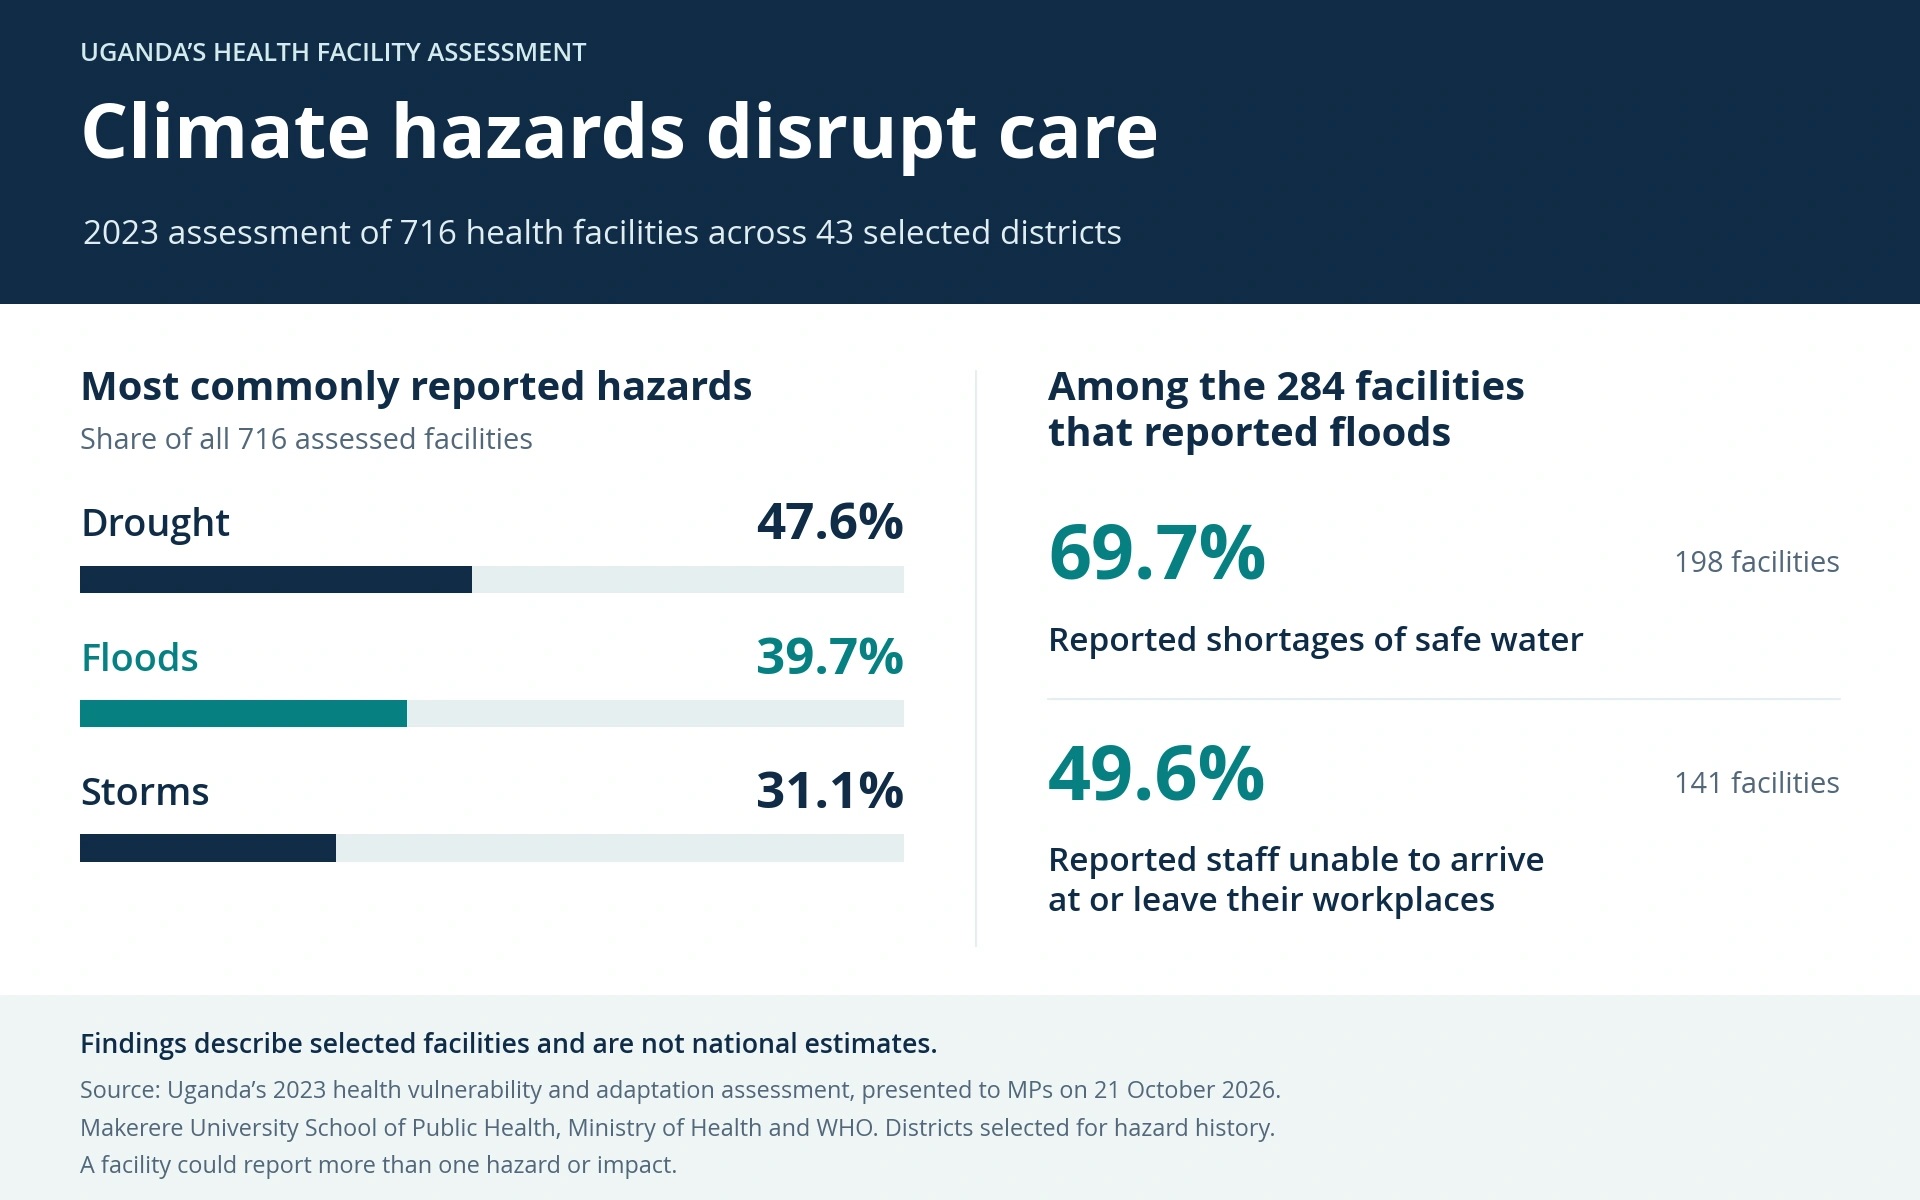
The H-NAP responds across ten components of the health system, including leadership, workforce training, risk monitoring and sustainable financing. Its proposed actions include revising infrastructure standards and using weather and disease information to warn of health risks earlier. Protecting care requires investment in buildings alongside the people and systems that make them function.
“A significant proportion of healthcare facilities lack water management and safety plans to address contamination risks,” the H-NAP states. “They lack water safety plans and contingency plans for monitoring and reducing contaminants as well as on-site water purification equipment.” Such gaps can leave facilities unable to maintain hygiene, clean equipment and provide treatment safely when water supplies fail or become contaminated.
The H-NAP already includes a budget, giving implementation a basis for resource mobilisation. The UN climate secretariat’s 2026 report on national adaptation plans across sectors identifies the difficulty of turning priorities into fundable projects. It recommends costing specific interventions and securing delivery partners, steps that can help advance Uganda’s health adaptation priorities.
At household level, climate pressures on livelihoods can leave families less able to get care or keep children in school, as community consultations showed.
“Their problems are interconnected. If climate, for example, affects their livelihoods, it directly impacts their health, because that means when they fall sick they can’t get care, and they can’t take their children to school, so things are all interconnected,” Dr. Isunju said.

The Ministry’s Focal Point for Climate Change and Health, Dr. Didacus Namanya, told MPs that resilience, the ability to withstand disruption and keep providing care, must inform how services are built and managed.
“So, our vision in the H-NAP is to have a responsive, adaptive, and resilient health system. Adaptive, we are talking about adaptation. These impacts will not stop; they will continue coming, but we must develop our adaptive capacity. The way we build our health facilities, the way we tackle the disease burden, we must be highly adaptive,” he said.
Dr. Namanya called for district-specific assessments, noting the different conditions in Nakasongola and Bududa, and described an ongoing review of infrastructure design standards. Dr. Isunju reported that guidelines for coordinating climate and health action across institutions were undergoing approval.
A partnership announced in October 2025 by the Rockefeller Foundation and the International Development Research Centre is helping the School and the Clinton Health Access Initiative, working with the Ministry of Health, build an investment case for H-NAP implementation. A separate Ministry of Health and Global Green Growth Institute initiative, begun in June 2026, is advancing climate-resilient water, sanitation and hygiene standards, investment plans for health facilities and the government’s capacity to deliver improvements.

Questions for Antalya
Legislators sought evidence of what implementation had delivered. Terego East MP Hon. Wilfred Babanga Erima asked how much of the plan had been implemented, how many facilities had been audited and refitted for climate resilience, and how funding was divided between domestic and donor sources. Hon. Shafiga Wanyenya, Vice Chairperson of Parliament’s Committee on Climate Change, proposed joint follow-up with the health committee and regular progress reviews.
“Our role is to ask the difficult questions and also identify implementation gaps, to advocate for the vulnerable communities and ensure that the national commitments translate into tangible improvements in the lives of our people,” Hon. Wanyenya said.

Those questions belong in Antalya too. The Yearbook of Global Climate Action 2026 identifies gaps in global data for assessing whether health systems are becoming more resilient, underlining the importance of tracking what adaptation efforts deliver for health.
The COP31 health programme links implementation of the Belém Health Action Plan with a financing framework intended to help turn health priorities into investable projects. Launched on 9 November, the Antalya Initiative for Health Resilience provides a platform for countries to share practical experience. The COP28 adaptation framework sets targets for climate-resilient health services by 2030 and progressively beyond, alongside national adaptation planning by 2030 and multi-hazard early-warning systems by 2027.
The H-NAP gives Uganda a practical agenda for that next stage. It calls for climate and health priorities to enter government budgets and for proposals capable of attracting finance. It also identifies academic partnerships as a route to research and capacity-building funds. Annual reviews would then assess progress and guide subsequent work.
As negotiations continue in Antalya, the next test is whether decisions there, and action at home, help keep care available, on the road to a health facility, and at the water point on which safe treatment depends.
-

 General2 weeks ago
NOTICE: Online Applications for Government Sponsorship for Programmes Offered at Public Universities & Other Tertiary Institutions 2027/2028 AY
-

 Agriculture & Environment2 weeks ago
Zambia readies to host the 22nd RUFORUM AGM in the Capital Lusaka
-

 General1 week ago
Makerere-Rotary Launch Student Food for Peace Initiative
-

 Research2 weeks ago
Your Research, Your Identity, Your Impact. Makerere Empowers Graduate Students to Go Global Through ORCID
-

 General2 weeks ago
RENU Communications Department Graduate Trainee Program: Two (2) Vacancies