On Tuesday May 26, 2020, Makerere University (Mak) Management converged to share findings from the study whose aim of was “to detail characteristics and treatment outcomes of the Coronavirus (COVID 19) pandemic patients in Uganda”. Coronavirus being a novel and rapidly changing pandemic, it was essential that early lessons are obtained and synthesised. These lessons directly feed into the clinical care guidelines and eventually contribute to the country’s interventions. With funding from the Government of Uganda through the Makerere University Research and Innovations Fund (Mak-RIF), this study was successfully executed.The multidisciplinary research team was coordinated through the Makerere University Lung Institute (MLI) http://mli.mak.ac.ug/. This study was led by Dr. Bruce Kirenga, Director MLI, and Prof. William Bazeyo, Acting Deputy Vice Chancellor (Finance and Administration)-Mak as Principal Investigators. Other investigators were from Entebbe Regional Referral Hospital, Johns Hopkins University, Baltimore, USA, Uganda Peoples Defence Forces, The AIDS Support Organisation (TASO), Mulago National Referral Hospital, the College of health Sciences and Ministry of Health, Uganda.
This study was conducted on the first group of COVID-19 patients (56) at Mulago National Referral hospital and Entebbe Regional Referral hospitals. Patient enrolment has continued but below we exultantly share preliminary findings.
· Age: the average age of the patients in Uganda was 33 years which is far lower than has is reported elsewhere. In Wuhan China, for example, the average age is 59 while in the New York USA it is as higher (63 years). Older the patient have higher risk of severe forms of disease and ultimately the poorer treatment outcomes.
· Patient Presentation: Among symptomatic COVID-19 patients, the most common symptoms were fever (21.4%), cough (19.6%), runny nose (16.1%), headache (12.5%), muscle aches (7.1%) and fatigue (7.1%). However, more than half of the patients did not have any of these symptoms at diagnosis. These patients were largely travellers returning from abroad or contacts of the confirmed/symptomatic patients above. Unlike our patients, 80% of hospitalised patients in the western world were symptomatic.
· Laboratory and imaging tests: Coronavirus has been reported to affect almost all body tissues. To understand the extent of damage, our research team performed a wide range of tests including complete blood count, kidney function tests, troponin, lactate dehydrogenase which identifies for signs of damage to a wide range of body tissues, and C reactive protein-CRP. We found that 10.6% of the patients had low white blood cells, 26.3% had low platelets, and 12.8% had evidence of liver damage, while the kidneys had no evidence of damage. 12.2% had evidence of systemic inflammation and 43% had evidence of nonspecific tissue damage. The electrical heart activity was also checked with the electrocardiograph (ECG). All patients had normal ECG with the exception of one who had a very slow heart (bradycardia). We checked lung damage with Chest X-rays (CXR) and computed Tomography scans (CT). Three patients had significant lung damage on CT and CXR; while one of them had low oxygen saturation.
· Comorbidity: About 25% of the initial patients (56) reported having other medical conditions in addition to COVID-19. Most of the conditions reported were the non-communicable diseases such as hypertension and diabetes which accounted for 11%. High blood pressure (higher than 140/90mmHg) was the most common comorbid disease recorded in up to 28% of the patients.
· Disease severity: At admission, only 2 patients met the classification of severe disease (patients with severe respiratory symptoms requiring oxygen therapy) while the rest had mild disease. Temperature and oxygen saturation were monitored three times a day. All the patients recovered without the need for admission to Intensive care unit (ICU) or ventilation. This is contrary to what has been observed elsewhere, where 5% of COVD-19 patients required ICU care.
· Treatment: To-date, there is no known cure for COVID-19. The current treatments are meant to alleviate symptoms while waiting for the body to mount an immune response to fight off the infection. The patients were able to recover on supportive care through managing the symptoms, treatment with antibiotics for those who had evidence of bacterial infection, hydroxychloroquine and vitamin C. In instances where the patients had comorbid conditions, proper management of these conditions was part of the treatment.
Conclusion: The initial group of COVID-19 patients diagnosed in the country presented with mild disease and exhibited a clinical course of disease that is quite different from what has been observed elsewhere. Imaging and laboratory tests are critical in management of this disease. Prompt identification of patients and initiation of treatment could help to prevent the development of severe forms of the disease. Frequent monitoring of the oxygen saturation is also critical for rapid patient identification and treatment. In light of the increasing number of cases in the country, these findings help in informing the national preparedness plan for COVID-19 (capacity building of health workers in clinical care for COVID-19, the required logistics, continuous research).
Recommendations
1. Expand testing for COVID-19 in view of the finding that almost half of those confirmed did not have the classical symptoms for COVID 19. Add rhinorrhoea to symptoms for case screening.
2. Efforts should be taken to make clinical, laboratory and imaging tests available at all COVID-19 treatment centres to support proper grading of disease severity. At a minimum, pulse oximetry should be routine in management of COVID patients.
3. Capacity to diagnose and treat non communicable comorbid conditions should be built across the country as part of COVID 19 response. Equipment for proper diagnosis of these diseases should be secured, installed and effectively used.
4. Strengthen monitoring, evaluation and learning as part COVID-19 care. This will allow continued learning of COVID-19 in general and the effectiveness of the different treatments of the disease.
5. Research should be supported including biomedical sciences research. This will allow growth of locally generated evidence to support the country’s COVID 19 response.
Acknowledgement
· The Government of the Republic of Uganda, Makerere University Research and Innovations Fund (Mak-RIF), Ministry of Health, Uganda, Uganda Virus Research Institute, Mulago National Referral Hospital, Entebbe Regional Referral Hospital.
· The study participants, all health workers engaged and Makerere University leadership.
This week, world leaders, negotiators and researchers are gathered in Antalya, Türkiye, for COP31, the United Nations climate conference, seeking to turn years of climate commitments into action countries can finance and implement. Among them is Dr. John Bosco Isunju, a climate and health researcher at Makerere University School of Public Health, named among TIME’s 100 most influential climate leaders in 2024.
Dr. Isunju led the School’s technical support to the Ministry of Health for Uganda’s 2023 Climate Change Health Vulnerability and Adaptation Assessment (VAA) and the subsequent development of the Health National Adaptation Plan (H-NAP) 2025–2030. The assessment covered 716 health facilities across 43 districts, documenting vulnerabilities that helped shape the country’s priorities for protecting healthcare from climate hazards.

Flood damage at Kilembe Mines Hospital in Kasese District. Damaged wards can disrupt treatment and limit access to care. Photo: H-NAP Team.
That experience speaks directly to the task before the 9–20 November summit. With “Dynamic and Resilient Health Systems” among the COP31 Presidency’s Action Agenda priorities, the conference is seeking practical solutions and financing to keep services functioning through climate shocks. Adaptation, the practical changes needed to cope with a changing climate, must ultimately reach the facilities where people seek care.
Protecting facilities from floods and drought also safeguards the public investment behind them, giving Uganda’s adaptation effort an economic significance alongside its importance to patients. In a 27 October 2026 statement ahead of COP31, UN Climate Change Executive Secretary Simon Stiell placed climate action within that wider calculation of public benefit.
“More governments are taking climate action right across their economies, to bank the vast benefits of clean energy and climate resilience,” he said. “Almost every major economy, and many medium-sized and smaller economies, now see climate action as a central driver of economic growth, jobs, and affordable and secure energy.”

UN climate chief Simon Stiell delivers opening remarks at COP31 in Antalya, Türkiye. Photo: UN Climate Change/Kiara Worth.
On 21 October, nearly three weeks before the Antalya talks, the H-NAP was before Ugandan parliamentarians in Kampala. Convened by the Ministry of Health and Parliamentary Forum on Climate Change Uganda, with support from Regenerate Africa and the Clinton Health Access Initiative, the engagement examined the plan and Parliament’s role in securing funding, scrutinising implementation and ensuring accountability.
Presenting the VAA, Dr. Isunju explained that the team examined the hazards facing each area, the extent of exposure and the weaknesses that made services vulnerable. They also considered the communities the facilities served. A flood could turn an already difficult journey to treatment into one that patients and staff could no longer make, as seen in many parts of Uganda, including Kasese.
“Either health workers will not work, or communities will not be able to access care, or outreaches will not be possible because roads are cut off,” he told legislators.

MPs at the orientation on implementing Uganda’s Health National Adaptation Plan, led by Makerere University School of Public Health, the Ministry of Health and partners in Kampala, 21 October 2026.
Uganda’s H-NAP grew out of commitments made at COP26 in Glasgow in 2021 to assess health vulnerabilities and develop an adaptation response. The Ministry of Health commissioned the School to undertake the VAA in 2023, with Rockefeller Foundation funding supporting both the assessment and the plan’s development. Developed through stakeholder consultation, with WHO technical support and contributions from other partners, the plan was launched on 22 August 2024.
What the assessment found
The VAA found that drought and floods were disrupting the conditions needed to deliver care. Nearly half of the assessed facilities reported drought exposure, while about two in five reported floods. Among the 284 facilities reporting flood exposure, 141 (about half) said health professionals had been unable to arrive at or leave their workplaces, and 198 (about seven in ten) reported shortages of safe water. Because districts were selected for their history of hazards, these findings describe the assessed facilities and cannot be treated as national estimates.
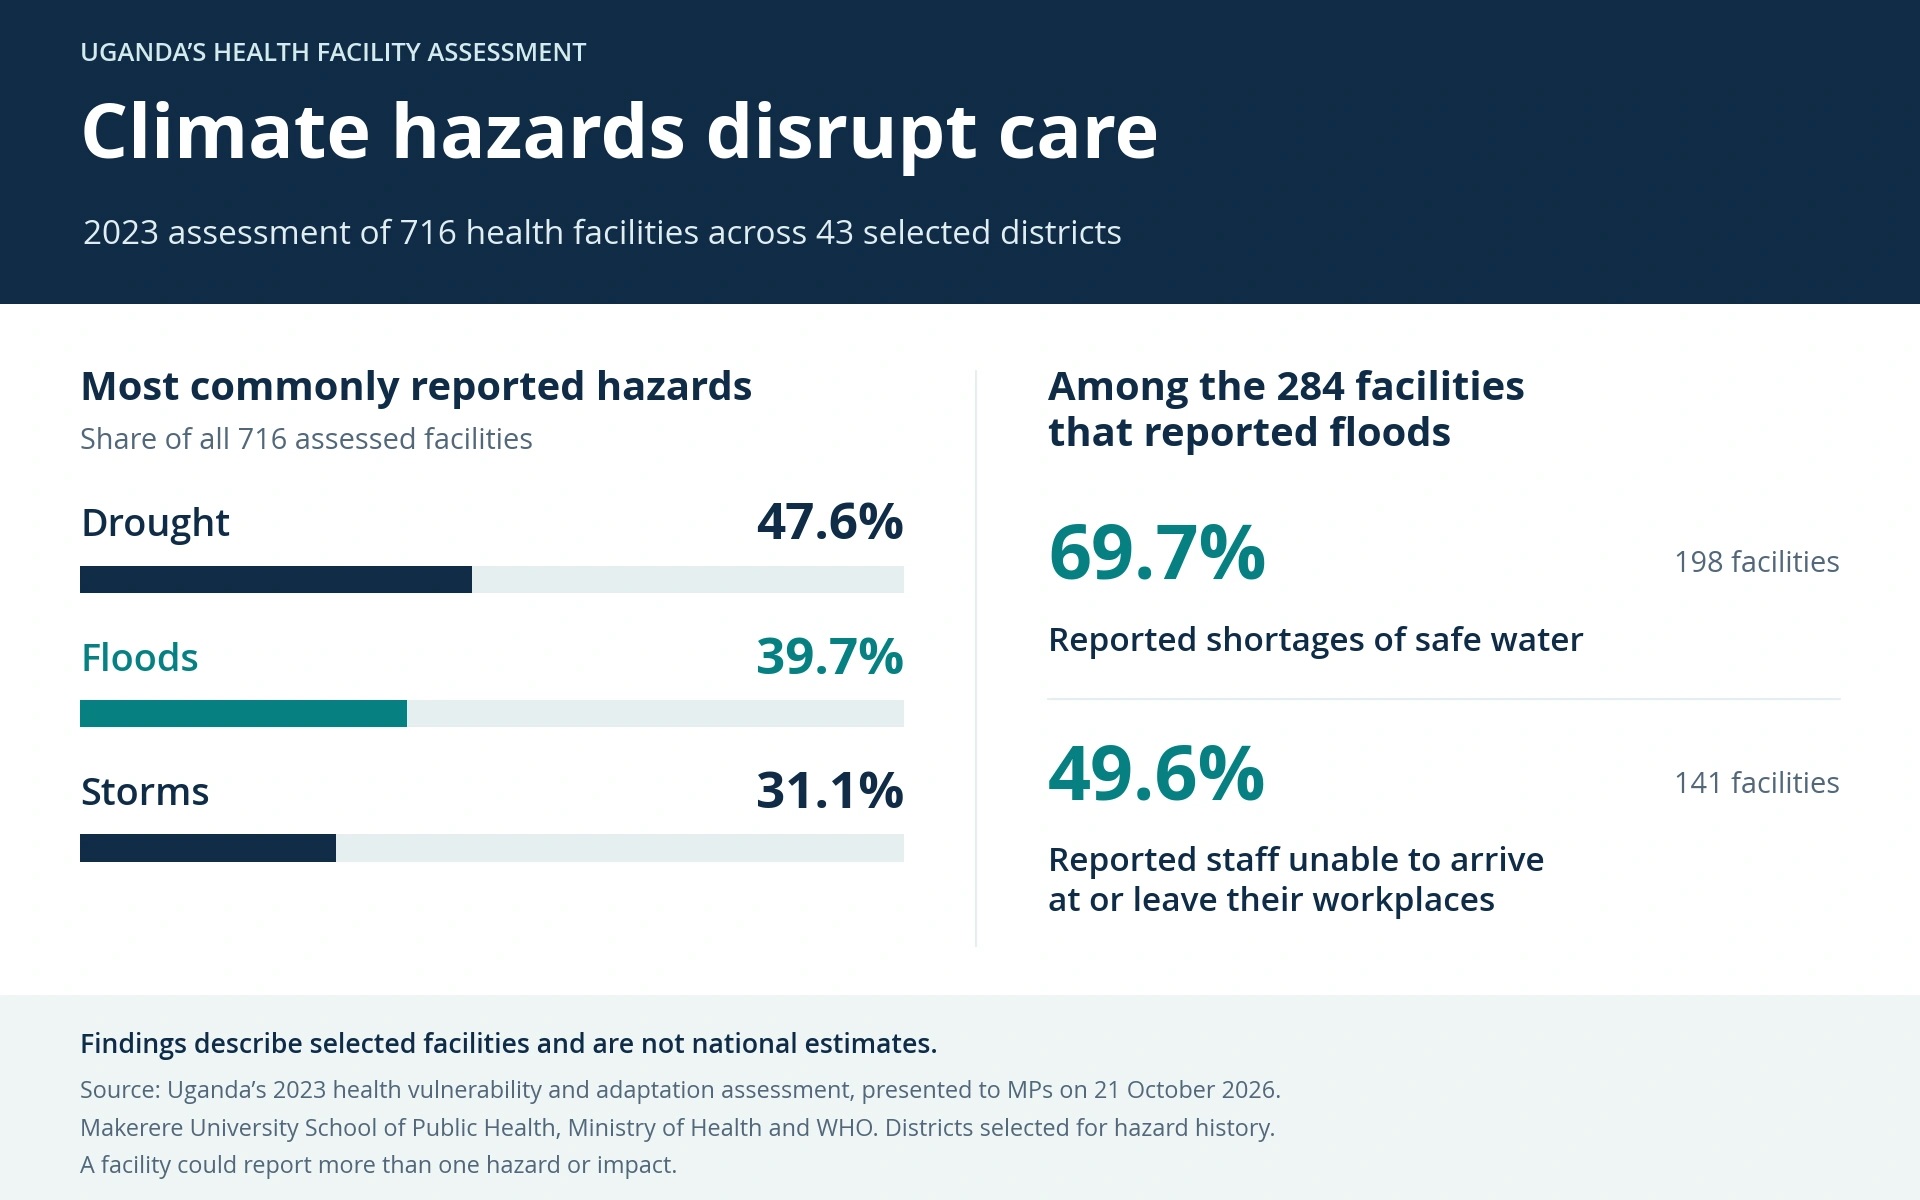
Findings from Uganda’s 2023 health vulnerability assessment helped shape its Health National Adaptation Plan 2025–2030.
The H-NAP responds across ten components of the health system, including leadership, workforce training, risk monitoring and sustainable financing. Its proposed actions include revising infrastructure standards and using weather and disease information to warn of health risks earlier. Protecting care requires investment in buildings alongside the people and systems that make them function.
“A significant proportion of healthcare facilities lack water management and safety plans to address contamination risks,” the H-NAP states. “They lack water safety plans and contingency plans for monitoring and reducing contaminants as well as on-site water purification equipment.” Such gaps can leave facilities unable to maintain hygiene, clean equipment and provide treatment safely when water supplies fail or become contaminated.
The H-NAP already includes a budget, giving implementation a basis for resource mobilisation. The UN climate secretariat’s 2026 report on national adaptation plans across sectors identifies the difficulty of turning priorities into fundable projects. It recommends costing specific interventions and securing delivery partners, steps that can help advance Uganda’s health adaptation priorities.
At household level, climate pressures on livelihoods can leave families less able to get care or keep children in school, as community consultations showed.
“Their problems are interconnected. If climate, for example, affects their livelihoods, it directly impacts their health, because that means when they fall sick they can’t get care, and they can’t take their children to school, so things are all interconnected,” Dr. Isunju said.

Dr. John Bosco Isunju briefs MPs on climate risks to Uganda’s health services in Kampala, 21 October 2026.
The Ministry’s Focal Point for Climate Change and Health, Dr. Didacus Namanya, told MPs that resilience, the ability to withstand disruption and keep providing care, must inform how services are built and managed.
“So, our vision in the H-NAP is to have a responsive, adaptive, and resilient health system. Adaptive, we are talking about adaptation. These impacts will not stop; they will continue coming, but we must develop our adaptive capacity. The way we build our health facilities, the way we tackle the disease burden, we must be highly adaptive,” he said.
Dr. Namanya called for district-specific assessments, noting the different conditions in Nakasongola and Bududa, and described an ongoing review of infrastructure design standards. Dr. Isunju reported that guidelines for coordinating climate and health action across institutions were undergoing approval.
A partnership announced in October 2025 by the Rockefeller Foundation and the International Development Research Centre is helping the School and the Clinton Health Access Initiative, working with the Ministry of Health, build an investment case for H-NAP implementation. A separate Ministry of Health and Global Green Growth Institute initiative, begun in June 2026, is advancing climate-resilient water, sanitation and hygiene standards, investment plans for health facilities and the government’s capacity to deliver improvements.

Rt. Hon. Lukia Isanga Nakadama signs a display copy of Uganda’s Health National Adaptation Plan at its launch in Kampala, 22 August 2024.
Questions for Antalya
Legislators sought evidence of what implementation had delivered. Terego East MP Hon. Wilfred Babanga Erima asked how much of the plan had been implemented, how many facilities had been audited and refitted for climate resilience, and how funding was divided between domestic and donor sources. Hon. Shafiga Wanyenya, Vice Chairperson of Parliament’s Committee on Climate Change, proposed joint follow-up with the health committee and regular progress reviews.
“Our role is to ask the difficult questions and also identify implementation gaps, to advocate for the vulnerable communities and ensure that the national commitments translate into tangible improvements in the lives of our people,” Hon. Wanyenya said.

Hon. Shafiga Wanyenya, Vice Chairperson of Parliament’s Climate Change Committee, calls for oversight of Uganda’s health adaptation plan in Kampala, 21 October 2026.
Those questions belong in Antalya too. The Yearbook of Global Climate Action 2026 identifies gaps in global data for assessing whether health systems are becoming more resilient, underlining the importance of tracking what adaptation efforts deliver for health.
The COP31 health programme links implementation of the Belém Health Action Plan with a financing framework intended to help turn health priorities into investable projects. Launched on 9 November, the Antalya Initiative for Health Resilience provides a platform for countries to share practical experience. The COP28 adaptation framework sets targets for climate-resilient health services by 2030 and progressively beyond, alongside national adaptation planning by 2030 and multi-hazard early-warning systems by 2027.
The H-NAP gives Uganda a practical agenda for that next stage. It calls for climate and health priorities to enter government budgets and for proposals capable of attracting finance. It also identifies academic partnerships as a route to research and capacity-building funds. Annual reviews would then assess progress and guide subsequent work.
As negotiations continue in Antalya, the next test is whether decisions there, and action at home, help keep care available, on the road to a health facility, and at the water point on which safe treatment depends.
Makerere University’s Professor Peter Waiswa has been appointed to the World Health Organization (WHO) Technical Working Group of Experts tasked with developing the Essential Child Health Services (ECHS) framework.
The appointment, communicated in an official letter dated October 21, 2026, and signed by Dr. Pascale Allotey, Director of WHO’s Department of Sexual, Reproductive, Maternal, Child, Adolescent and Ageing Health, runs until December 31, 2027.
The technical working group will support WHO in defining a core package of essential health services for newborns, older children and adolescents, alongside practical approaches for delivering these services effectively and equitably to improve their health and well-being.
As a member of the working group, Prof. Waiswa will contribute scientific and technical expertise to the development of the framework. His responsibilities will include participating in technical consultations, reviewing draft documents, providing written feedback and contributing to consensus-building on key technical issues.
The group is expected to hold approximately five online meetings between November 2026 and mid-2027. Members will serve in their individual capacities as independent experts rather than as representatives of their respective governments or institutions.
The appointment builds on Prof. Waiswa’s longstanding service and contributions to WHO. He previously served for seven years on WHO’s Strategic and Technical Advisory Group of Experts (STAGE) on Maternal, Newborn, Child and Adolescent Health and Nutrition, with his tenure concluding in June 2026.
Makerere University proudly celebrates the recognition of Mr. Mordecai Tayebwa, Senior Grants Manager, Makerere University Lung Institute and Ms. Bonny Tusiime, Grants and Contracts Officer, Makerere University College of Health of Sciences (MakCHS) as recipients of the prestigious Future of the Field Award of Society of Research Administrators International (SRAI), an international recognition that Honors emerging leaders making outstanding contributions to the advancement of research administration. This year’s ‘Future of the Field’ honorees were formally recognized at SRAI’s Annual Meeting held in Honolulu, Hawaii, USA in October, 2026.
The Future of the Field Award recognizes professionals who demonstrate exceptional leadership, innovation, and commitment to strengthening research management and administration. The award celebrates individuals whose work is shaping the future of the profession by improving research support systems, fostering collaboration, and advancing excellence in research administration.
At Makerere University, Mr. Tayebwa and Ms. Tusiime have played key roles in strengthening grants and contracts management, supporting researchers throughout the grant lifecycle, promoting compliance with sponsor requirements, and contributing to the development of sustainable research management systems. Their efforts have enhanced institutional capacity to attract, manage, and administer competitive research funding while ensuring accountability and excellence. Commenting on the recognition, the award recipients expressed their gratitude for the opportunity to contribute to the growth of research administration. “This recognition reflects not only our individual efforts but also the collaborative environment at MakCHS and Makerere University. It inspires us to continue strengthening research administration and supporting researchers in generating impactful scientific discoveries that improve lives.” They said.
The achievement highlights the growing international recognition of research administration professionals in Africa and underscores Makerere University and MakCHS’s general commitment to building strong research support systems that enable world-class research. This also reflects the institution’s investment in professional development and its dedication to advancing research excellence through effective grants management.
Commenting on the award, Dara C. Little, President, (SRAI) said “In a field as dynamic and rapidly evolving as research administration, the need for visionary,adaptable leaders have never been greater,” . “SRAI’s Future of the Field recipients represent the next generation of changemakers – those who will not only navigate complexity but shape the future of our profession. To embrace change, is to lead your innovation, resilience, and leadership are exactly what this moment demands. Rise to the opportunity and you will do great things!”
Makerere University congratulates Mr. Mordecai Tayebwa and Ms. Bonny Tusiime on this significant achievement and wishes them continued success as they contribute to shaping the future of research administration both regionally and globally








