
Health
Holding the System Together During COVID-19: Steven Kabwama’s Research on Care Continuity


In March 2020, Uganda slowed to a near standstill. Roads emptied. Clinics fell quiet. Fear moved faster than information. Many perceived COVID-19 as a virus to avoid. Others saw it as a barrier that stood between a mother and antenatal care, a child and routine immunization, and a patient and life-saving HIV medication. What followed was not only a public health emergency but also a test of whether health systems could keep doing the ordinary work of care while responding to the extraordinary.
In early December 2025, a question first asked with urgency during a global crisis resurfaced in a quieter, more reflective moment. On December 2, a single bound copy of Steven Kabwama’s doctoral thesis was fastened to a wooden board dubbed ‘The Wall of Fame‘ at Karolinska Institutet. The ritual, known as spikning, is modest in appearance but weighty in meaning: a thesis is made public, opened to scrutiny, and years of private intellectual labour are released into the world. For Kabwama, it marked the moment when research forged in the pressure of a global emergency became part of the public record, no longer his alone but open to collective examination.

The tradition stretches back centuries, often traced to Martin Luther’s public posting of his theses in the 15th century. But in Stockholm, on a winter afternoon, history gave way to something more immediate. Kabwama stood briefly by the wooden board with a hammer and fixed his work in place. The moment was less about ceremony than readiness. The research was complete. The questions were now open.

Three days later, on Friday, December 5, 2025, Kabwama publicly defended the thesis in a hybrid ceremony at Wretlindsalen in Solna, joined, both in person and online, by colleagues from Uganda, Sweden, and beyond. By then, the work, which examines how health systems sustain essential services during crises, had already begun to circulate, quietly shaping conversations about preparedness, continuity, and care.

What that bound document contained, however, had been forged years earlier, inside outbreaks, lockdowns, data sets, and long nights spent asking how health systems hold together when everything else is falling apart.
Steven Ndugwa Kabwama remembers the beginning not as a single crisis, but as a series of decisions, some made urgently, others too late. As an epidemiologist by training, Kabwama, who had spent years responding to outbreaks through Uganda’s Field Epidemiology Fellowship Program, clearly understood that outbreaks had patterns; they arrived, demanded attention, and eventually receded.
COVID-19 was different.
“It became clear very early on,” he recalls, “that the urgency of the response was going to affect everything else: malaria, immunization, maternal health, HIV. And yet, very little had been written about how systems are supposed to hold both at the same time.”
That realization would shape the next chapter of his life and, eventually, his PhD.
From Outbreak Response to System Questions
Kabwama’s academic journey did not begin in epidemiology. In 2006, he enrolled for a Bachelor’s degree in Food Science and Technology at Makerere University, a programme traditionally geared toward food processing, quality assurance, and industrial production. It is a discipline that prepares graduates for careers in manufacturing plants, laboratories, and supply chains, work that often unfolds far from clinics, outbreaks, and emergency response rooms.
Yet even then, his interests leaned beyond production lines and quality controls. He was drawn to how systems affect people’s health long before illness appears and how nutrition, safety, access, and policy intersect. That early grounding in systems thinking would later resurface in unexpected ways.
He went on to earn a Master of Science in Public Health from the University of Southern Denmark in 2013, supported by a Danish State Scholarship. It was there that population-level analysis sharpened his interest in data, surveillance, and health equity. But it was the Advanced Field Epidemiology Fellowship, jointly run by Makerere University School of Public Health (MakSPH), Uganda’s Ministry of Health, and the U.S. Centers for Disease Control and Prevention, that placed him directly inside emergencies, where evidence, decisions, and lives converge.
As a Fellow, his work stood out. He later received the Outstanding Fellow Award from the Uganda Public Health Fellowship Program (Field Epidemiology Track, Cohort 2015), recognition of his contributions to outbreak response, national non-communicable disease analyses, and policy work, including Uganda’s Alcohol Control Policy. “You respond, you stabilize, you move on,” he says. “But I kept asking myself—what happens to everything else while we’re responding?”

The arrival of COVID-19 made it impossible to delay these questions.
A Crisis Within the Crisis
As countries rushed to contain the virus, restrictions came swiftly: lockdowns, curfews, and travel bans. From a disease-control perspective, the logic was familiar and defensible. In outbreak management, 21 days is a standard epidemiological window, often used to break chains of transmission in infectious diseases. But during COVID-19 in Uganda, the phrase “therefore…another 21 days of lockdown” took on a different meaning altogether: The repeated phrase in presidential addresses stretched from a technical containment tool into a lived reality that reshaped access to care, livelihoods, and movement. From a health-system perspective, the consequences were profound.
Kabwama joined a multi-country research effort spanning Uganda, Nigeria, the Democratic Republic of Congo, Senegal, and Ghana, examining how countries attempted to maintain essential health services while responding to COVID-19. This work was spearheaded by Dr. Rhoda Wanyenze, a Professor of Disease Control, Researcher, Public Health Expert, and Dean of the School of Public Health at Makerere University. She was then a member of the COVID-19 Scientific Advisory Committee to the Ministry of Health.
Kabwama volunteered to lead the objective of documenting these experiences, an area he quickly realized was underexplored.
“Criticism is always easier in hindsight,” he reflects. “But generally, the considerations about how restrictions would affect access to essential health services were made after the fact.”
His doctoral research, later defended at Karolinska Institutet, set out to answer a deceptively simple question: How can health systems minimize disruptions to essential services during public health emergencies while emerging stronger afterward?

What the Data Revealed
Kabwama examined how health service use changed before and during the pandemic by using a mix of interrupted time-series analysis, document reviews, key informant interviews, and focus group discussions.
The findings were sobering.
Facility deliveries and outpatient visits dropped sharply during lockdown periods. Routine childhood immunizations declined, and DPT3 doses fell by more than 4 percent, with similar reductions across polio vaccines. Movement restrictions, fear of infection, and overwhelmed facilities combined to keep patients away.
But the story did not end there.
Where systems were adapted by integrating services, leveraging community health workers, removing user fees, modifying logistics, and establishing coordination mechanisms for continuity of care, the declines softened. In some cases, the adaptations strengthened systems beyond their pre-pandemic state.
“These were not perfect solutions,” Kabwama notes. “But they showed us what flexibility, leadership, and trust can do under pressure.”

The Human Cost—and the Human Shield
Behind every data point were health workers navigating impossible conditions. Many worked without adequate protective gear. Others faced delayed allowances, long hours, and constant risk.
Kabwama asserts that health workers risk their lives in their work. “If we expect services to continue, then protecting their physical and mental well-being is not optional.”
His research consistently returned to one conclusion: that service continuity depends on people. Policies can guide. Infrastructure can support. But without motivated, protected health workers and trusted community intermediaries, systems falter.
Uganda’s community health workers, he observed, became a backbone of resilience. They traced contacts, delivered information, encouraged women to attend antenatal care, and helped sustain immunization demand when facilities felt distant or dangerous.
“In our context,” he says, “they were critical. That’s a lesson worth holding onto.”
Learning Across Borders
Conducting his PhD through a collaborative programme between Karolinska Institutet and Makerere University School of Public Health exposed Kabwama to how different systems responded under pressure.
At Karolinska’s Department of Global Public Health, students from around the world shared experiences shaped by culture, trust, and governance. One story stayed with him: Sri Lanka’s military, highly trusted by the public, played a key role in vaccine rollout.
“It taught me that resilience looks different everywhere,” he says. “What matters is understanding what each system already has and how trust operates within it.”
His supervision team, spanning Sweden and Uganda, including Prof. Tobias Alfvén, Prof. Rhoda K. Wanyenze, Dr. John Ssenkusu, Prof. Helena Lindgren, and Dr. Neda Razaz, reflected that same cross-system thinking.
Wanyenze describes Kabwama as “focused, committed, and remarkably productive.” She notes that he led two major workstreams across the five participating countries, helping generate critical evidence on health systems resilience and trust during infectious disease emergencies. “He made an enormous contribution to the research,” she says, “and he continues to do excellent work in this area.”
The Quiet Challenge of Doing Research in a Pandemic
Methodologically, the pandemic forced adaptation. Interviews moved to phones and Zoom. Access was negotiated carefully. Yet Kabwama sees the technology not as a limitation but as a strength.
“We captured experiences while they were still fresh,” he explains. “Before details were forgotten, before narratives were smoothed over.”
That immediacy gave his work an unusual clarity, documenting decisions as they unfolded, not as they were later remembered.
But beyond COVID-19, Kabwama’s thesis does not treat it as an anomaly. Rather, it presents COVID-19 as a stress test, exposing pre-existing weaknesses and potential strengths.
His central argument is that the ability to maintain essential health services during emergencies depends on baseline capacity.
“Now is the time,” he says, “to invest in health workers, in infrastructure, in guidelines for service continuity. This should be done now, not when the next crisis arises.
That conviction extends to learning itself. After-Action Reviews are conducted, lessons are noted, but too often, they fade.
“We need to be deliberate about learning,” he insists. “About documenting what worked and making sure those gains are not lost once the emergency ends.”
Work That Continues
Today, Kabwama is a Research Associate at Makerere University School of Public Health, a Monitoring, Evaluation and Learning Specialist with the Uganda Public Health Fellowship Program, and a member of WHO initiatives on trust and pandemic preparedness. He leads mortality surveillance in Uganda’s island districts, supports national NCD analyses, and continues to advise on emergency preparedness across Africa.

He remains, by his description, an optimist.
“There are people who think we are worse off now than before COVID-19,” he says. “In some ways, that’s true. But there are also many ways in which we are better prepared.”
Vaccines, data systems, community engagement, and global awareness have all shifted. The challenge is ensuring that momentum does not fade.
Dr. Steven Ndugwa Kabwama joins fellows in the MakSPH PhD forum who concluded their doctoral journeys in 2025. And the work of his research and scholarship does not promise certainty but offers something more useful: evidence that systems can bend without breaking—if they are prepared to learn, invest, and protect the people who hold them together.














This week, world leaders, negotiators and researchers are gathered in Antalya, Türkiye, for COP31, the United Nations climate conference, seeking to turn years of climate commitments into action countries can finance and implement. Among them is Dr. John Bosco Isunju, a climate and health researcher at Makerere University School of Public Health, named among TIME’s 100 most influential climate leaders in 2024.
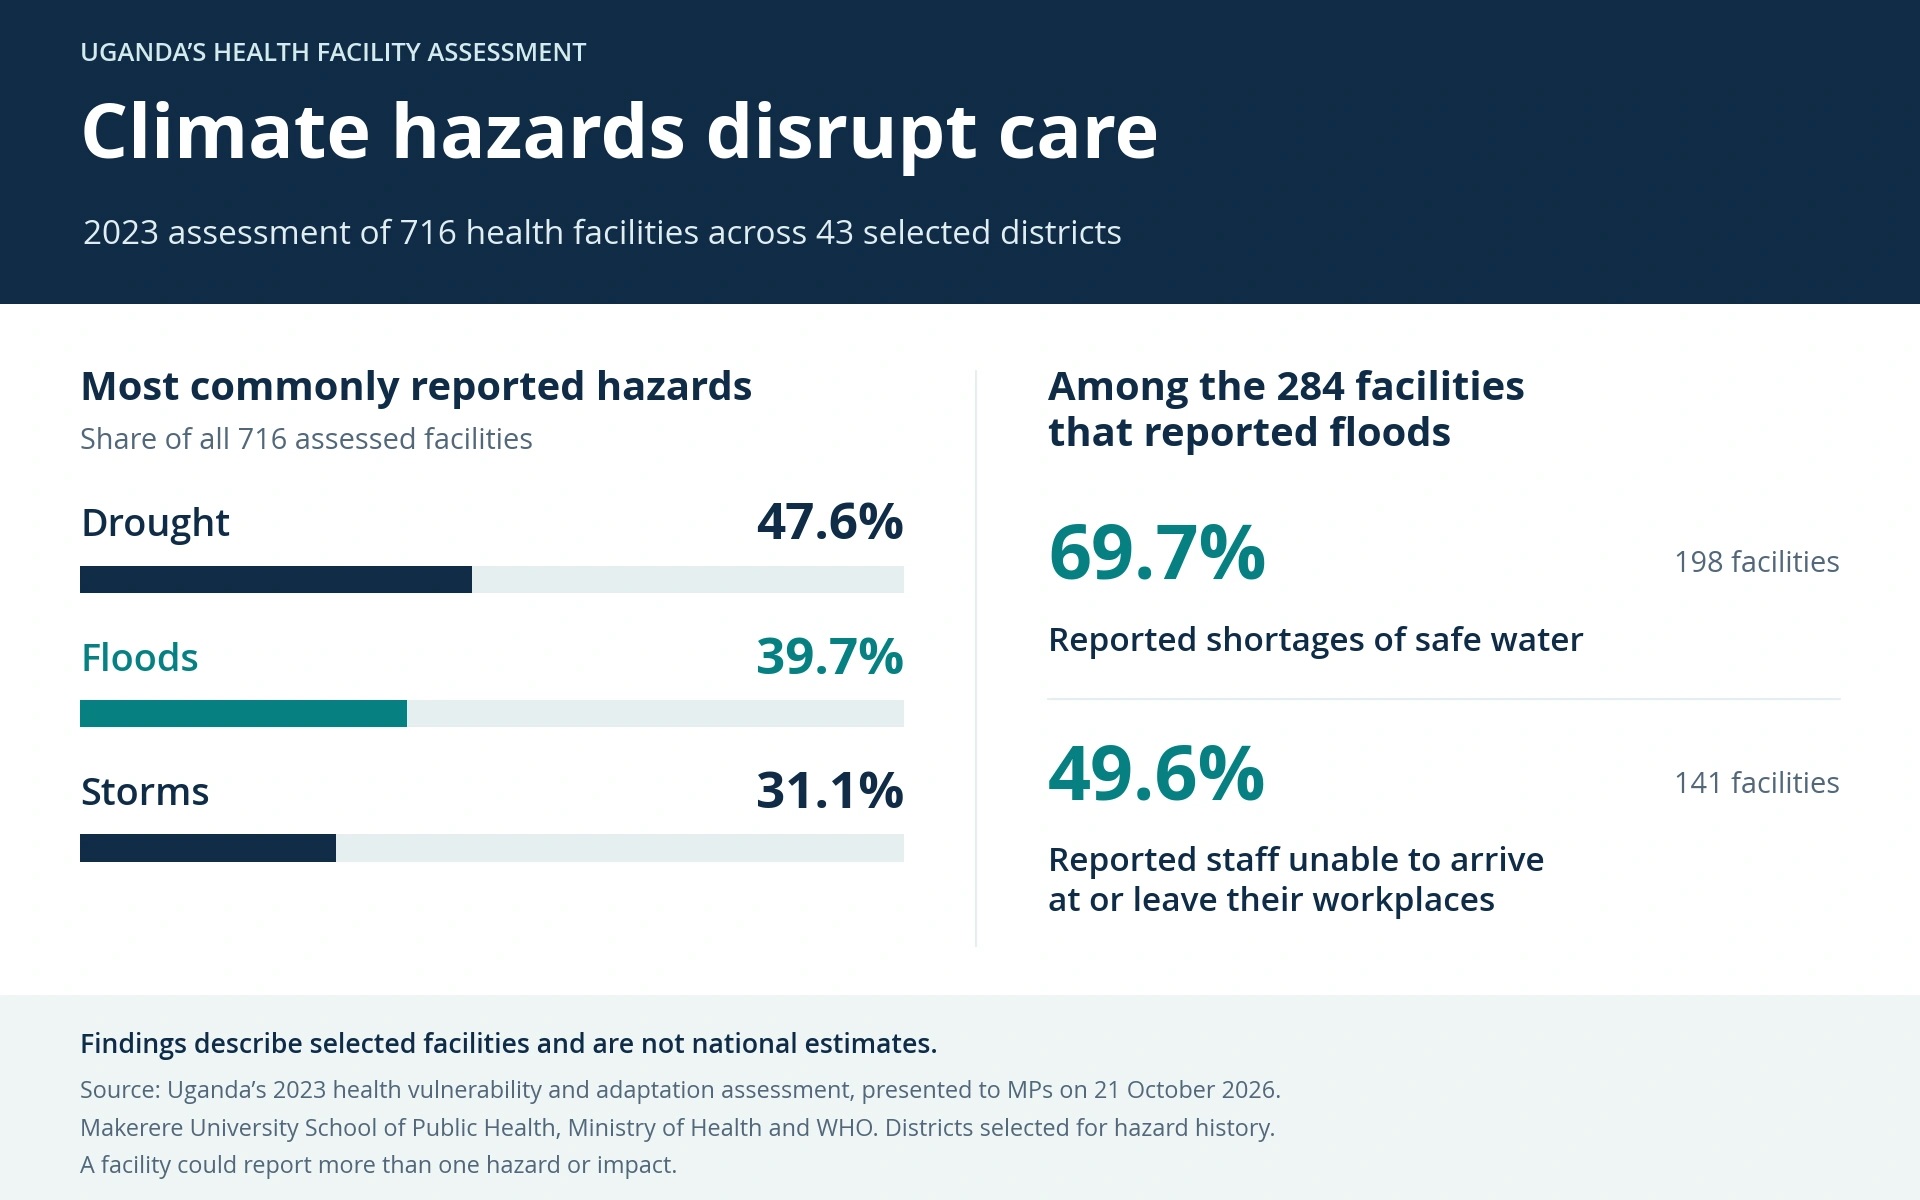
Dr. Isunju led the School’s technical support to the Ministry of Health for Uganda’s 2023 Climate Change Health Vulnerability and Adaptation Assessment (VAA) and the subsequent development of the Health National Adaptation Plan (H-NAP) 2025–2030. The assessment covered 716 health facilities across 43 districts, documenting vulnerabilities that helped shape the country’s priorities for protecting healthcare from climate hazards.

That experience speaks directly to the task before the 9–20 November summit. With “Dynamic and Resilient Health Systems” among the COP31 Presidency’s Action Agenda priorities, the conference is seeking practical solutions and financing to keep services functioning through climate shocks. Adaptation, the practical changes needed to cope with a changing climate, must ultimately reach the facilities where people seek care.
Protecting facilities from floods and drought also safeguards the public investment behind them, giving Uganda’s adaptation effort an economic significance alongside its importance to patients. In a 27 October 2026 statement ahead of COP31, UN Climate Change Executive Secretary Simon Stiell placed climate action within that wider calculation of public benefit.
“More governments are taking climate action right across their economies, to bank the vast benefits of clean energy and climate resilience,” he said. “Almost every major economy, and many medium-sized and smaller economies, now see climate action as a central driver of economic growth, jobs, and affordable and secure energy.”

On 21 October, nearly three weeks before the Antalya talks, the H-NAP was before Ugandan parliamentarians in Kampala. Convened by the Ministry of Health and Parliamentary Forum on Climate Change Uganda, with support from Regenerate Africa and the Clinton Health Access Initiative, the engagement examined the plan and Parliament’s role in securing funding, scrutinising implementation and ensuring accountability.
Presenting the VAA, Dr. Isunju explained that the team examined the hazards facing each area, the extent of exposure and the weaknesses that made services vulnerable. They also considered the communities the facilities served. A flood could turn an already difficult journey to treatment into one that patients and staff could no longer make, as seen in many parts of Uganda, including Kasese.
“Either health workers will not work, or communities will not be able to access care, or outreaches will not be possible because roads are cut off,” he told legislators.

Uganda’s H-NAP grew out of commitments made at COP26 in Glasgow in 2021 to assess health vulnerabilities and develop an adaptation response. The Ministry of Health commissioned the School to undertake the VAA in 2023, with Rockefeller Foundation funding supporting both the assessment and the plan’s development. Developed through stakeholder consultation, with WHO technical support and contributions from other partners, the plan was launched on 22 August 2024.
What the assessment found
The VAA found that drought and floods were disrupting the conditions needed to deliver care. Nearly half of the assessed facilities reported drought exposure, while about two in five reported floods. Among the 284 facilities reporting flood exposure, 141 (about half) said health professionals had been unable to arrive at or leave their workplaces, and 198 (about seven in ten) reported shortages of safe water. Because districts were selected for their history of hazards, these findings describe the assessed facilities and cannot be treated as national estimates.
The H-NAP responds across ten components of the health system, including leadership, workforce training, risk monitoring and sustainable financing. Its proposed actions include revising infrastructure standards and using weather and disease information to warn of health risks earlier. Protecting care requires investment in buildings alongside the people and systems that make them function.
“A significant proportion of healthcare facilities lack water management and safety plans to address contamination risks,” the H-NAP states. “They lack water safety plans and contingency plans for monitoring and reducing contaminants as well as on-site water purification equipment.” Such gaps can leave facilities unable to maintain hygiene, clean equipment and provide treatment safely when water supplies fail or become contaminated.
The H-NAP already includes a budget, giving implementation a basis for resource mobilisation. The UN climate secretariat’s 2026 report on national adaptation plans across sectors identifies the difficulty of turning priorities into fundable projects. It recommends costing specific interventions and securing delivery partners, steps that can help advance Uganda’s health adaptation priorities.
At household level, climate pressures on livelihoods can leave families less able to get care or keep children in school, as community consultations showed.
“Their problems are interconnected. If climate, for example, affects their livelihoods, it directly impacts their health, because that means when they fall sick they can’t get care, and they can’t take their children to school, so things are all interconnected,” Dr. Isunju said.

The Ministry’s Focal Point for Climate Change and Health, Dr. Didacus Namanya, told MPs that resilience, the ability to withstand disruption and keep providing care, must inform how services are built and managed.
“So, our vision in the H-NAP is to have a responsive, adaptive, and resilient health system. Adaptive, we are talking about adaptation. These impacts will not stop; they will continue coming, but we must develop our adaptive capacity. The way we build our health facilities, the way we tackle the disease burden, we must be highly adaptive,” he said.
Dr. Namanya called for district-specific assessments, noting the different conditions in Nakasongola and Bududa, and described an ongoing review of infrastructure design standards. Dr. Isunju reported that guidelines for coordinating climate and health action across institutions were undergoing approval.
A partnership announced in October 2025 by the Rockefeller Foundation and the International Development Research Centre is helping the School and the Clinton Health Access Initiative, working with the Ministry of Health, build an investment case for H-NAP implementation. A separate Ministry of Health and Global Green Growth Institute initiative, begun in June 2026, is advancing climate-resilient water, sanitation and hygiene standards, investment plans for health facilities and the government’s capacity to deliver improvements.

Questions for Antalya
Legislators sought evidence of what implementation had delivered. Terego East MP Hon. Wilfred Babanga Erima asked how much of the plan had been implemented, how many facilities had been audited and refitted for climate resilience, and how funding was divided between domestic and donor sources. Hon. Shafiga Wanyenya, Vice Chairperson of Parliament’s Committee on Climate Change, proposed joint follow-up with the health committee and regular progress reviews.
“Our role is to ask the difficult questions and also identify implementation gaps, to advocate for the vulnerable communities and ensure that the national commitments translate into tangible improvements in the lives of our people,” Hon. Wanyenya said.

Those questions belong in Antalya too. The Yearbook of Global Climate Action 2026 identifies gaps in global data for assessing whether health systems are becoming more resilient, underlining the importance of tracking what adaptation efforts deliver for health.
The COP31 health programme links implementation of the Belém Health Action Plan with a financing framework intended to help turn health priorities into investable projects. Launched on 9 November, the Antalya Initiative for Health Resilience provides a platform for countries to share practical experience. The COP28 adaptation framework sets targets for climate-resilient health services by 2030 and progressively beyond, alongside national adaptation planning by 2030 and multi-hazard early-warning systems by 2027.
The H-NAP gives Uganda a practical agenda for that next stage. It calls for climate and health priorities to enter government budgets and for proposals capable of attracting finance. It also identifies academic partnerships as a route to research and capacity-building funds. Annual reviews would then assess progress and guide subsequent work.
As negotiations continue in Antalya, the next test is whether decisions there, and action at home, help keep care available, on the road to a health facility, and at the water point on which safe treatment depends.
Health
Makerere University’s Prof. Peter Waiswa Appointed to WHO Technical Working Group on Essential Child Health Services


Health
Mak Staff Receive Prestigious International “Future of the Field” Recognition in Global Research Administration Class of 2026.


-

 General1 week ago
NOTICE: Online Applications for Government Sponsorship for Programmes Offered at Public Universities & Other Tertiary Institutions 2027/2028 AY
-

 General2 weeks ago
Makerere Marks 2026 International Day of Persons with Disability – Lord Mayor Balimwezo Delivers Keynote
-

 Health2 weeks ago
Mayuge Study Finds NCD Risks Emerging in Adolescence, and Shows Early Action Can Help
-

 Agriculture & Environment1 week ago
Zambia readies to host the 22nd RUFORUM AGM in the Capital Lusaka
-

 General1 week ago
Makerere-Rotary Launch Student Food for Peace Initiative