
Health
Dr. Samalie Namukose and the Quiet Work of Making Nutrition Count


Between Tuesday, February 24 and Friday, February 27, 2026, Freedom Square at Makerere University will fill with a familiar choreography of anticipation. The air will fill with the rustle of academic gowns, the nervous laughter of graduands, and the careful positioning of proud families searching for familiar faces in a sea of crimson, green, and black. It is a moment of ceremony, yes, but also of reckoning.
Up close, the doctoral gowns feel heavier than they look. The deep crimson fabric, warm and deliberate, settles on the shoulders. Green panels edged in gold are gently pressed against the chest. Wide sleeves gently brush against clasped hands, soft bonnets rest low on foreheads, and tassels remain motionless. Beneath the regalia are steady breaths, quickened heartbeats, and bodies carrying the quiet fatigue of years spent balancing work, study, and life. These are garments worn not only for display but also for endurance, stitched to nights without sleep, to questions carried long before they were answered.
At this four-day Makerere University’s 76th Graduation Ceremony, 185 doctoral degrees will be conferred. Each PhD will represent years of unanswered questions, interrupted sleep, financial strain, and relentless intellectual persistence. Among them will be Dr. Samalie Namukose, a woman whose academic journey was never separate from the health system she serves, only threaded through it.
For more than two decades, Samalie Namukose has worked inside Uganda’s Ministry of Health, rising steadily from Nutritionist to Assistant Commissioner for Health Services/Nutrition. She has helped write policy, coordinate national programs, supervise districts, respond to emergencies, and advocate for mothers and infants whose voices rarely travel beyond clinic walls. Her PhD did not pull her away from that world but plunged her deeper into it.

The Question That Would Not Let Go
Dr. Namukose’s doctoral journey began not in a library, but in a pattern she kept seeing and could no longer ignore.
Uganda’s nutrition policies are robust. They speak clearly about the importance of maternal and infant nutrition, especially in the first 1,000 days of life. Yet in health facilities across the country, nutrition services often appeared fragmented, present in principle, and inconsistent in practice. Mothers attending antenatal or postnatal care were weighed, yes, but not always counselled. Infants were measured, but follow-up was irregular. Nutrition existed, but it was not always integrated.
“I kept asking myself,” she recalls, “not whether nutrition interventions exist, but how well they are embedded in routine care, and what prevents health workers from delivering them consistently.”
That question shaped her PhD research at Makerere University’s School of Public Health, where she examined the integration of Nutrition Assessment, Counselling, and Support (NACS) into routine health services in the Tororo and Butaleja districts in Eastern Uganda.
At its core, NACS integration is deceptively simple: assess nutritional status at every health point, provide tailored counseling, and link clients to support within the same system and beyond. But in practice, it tests the very backbone of health systems: workforce capacity, financing, governance, supervision, and community linkages.
“When NACS is well integrated, health facilities can identify nutrition risks early, prevent deterioration, and provide timely support rather than responding only when malnutrition becomes severe,” she says.
Inside Resource-Constrained Health Facilities
What Dr. Namukose found was not a clear story of failure or success, but something in between. Many health facilities were offering basic nutrition education and assessments, and health workers were clearly trying their best. However, long patient queues, limited time, and a shortage of basic tools and job aids often hindered counseling and follow-up. Food demonstrations were rare. Growth monitoring was inconsistent. Efforts to improve quality occurred only sporadically.
In facilities without trained nutritionists, nurses, and midwives, already stretched thin, took on nutrition work alongside many other duties, leaving little room to support mothers and children in a steady, continuous way.
And yet, her findings revealed something deeply hopeful: “facilities with knowledgeable, motivated, and supported health workers delivered better nutrition services, even within the same constraints.” To Dr. Namukose, this showed that leadership, mentorship, and attitude mattered. Where nutrition was treated not as an extra task but as essential care, outcomes began to improve.
One of the strongest findings from Dr. Namukose’s research was that even when nutrition services were only partly integrated, they still made a visible difference. Mothers gained weight more steadily during pregnancy and in the early months of breastfeeding. Babies were born heavier and grew better in their first months of life. Across health facilities with more fully integrated nutrition services, children consistently showed healthier growth patterns.

These were not just numbers on a page; babies started life stronger, and mothers were better supported to care for them.
“To me,” she explains, “the improvements in maternal weight gain reflected the value of regular assessment and context-specific counseling. For infants, the better growth outcomes showed that a package of nutrition interventions, delivered consistently, can make a real difference during the most critical window of life.”
It was clear evidence that nutrition integration works effectively, though gradually and significantly.
The Fragility of Progress
Dr. Namukose’s research also exposed how fragile these gains remain. Weaknesses in financing and governance emerged as the greatest threats to sustainability. Nutrition services often depended on unpredictable partner funding rather than routine government budgets. Essential supplies, anthropometric tools, job aids, and therapeutic foods were frequently unavailable or externally dependent.
Her study captured glaring governance gaps that compounded the problem. For instance, nutrition was not always clearly positioned within accountability structures, and this, according to Dr. Namukose, often led to limited supervision and weak performance monitoring. Many districts lacked dedicated nutritionists altogether.
She notes that community follow-up was essential for sustaining behaviour change after clinic visits, especially for those who suffered most. Village Health Teams and care groups struggled without supervision, feedback mechanisms, or resources.
“Most nutrition-related behaviours, such as maternal diet, infant and young child feeding, and care practices, are shaped and sustained within households and communities,” says Dr. Namukose.
She contends that nutrition integration cannot rely on projects but must be embedded in systems.

A PhD Written in the Margins of Life
Conducting this research while holding a senior national leadership role in the Ministry of Health was, by her own admission, one of the hardest things she has ever done.
Dr. Namukose did not request study leave. Partly self-sponsored, she worked full days at the Ministry of Health, then wrote at night, often between midnight and 4:00 am, and again in the early mornings, on Saturdays, and on borrowed hours of Sunday.
“There were days when I sacrificed sleep completely,” she says quietly.
National emergencies such as COVID-19, Ebola, and MPOX repeatedly interrupted her doctoral journey, drawing her back into crisis response. To her, returning to her PhD after each interruption felt like re-entering a conversation mid-sentence, struggling to find the thread.
At one point, she simultaneously prepared for a Top Management Committee presentation, attended a doctoral committee meeting, and sat for Health Service Commission promotional interviews.
“The pressure from the supervisors kept me on my toes. The PhD forum was another motivating factor, consistently sharing updates, books, courses, encouragement, and invitations to PhD defenses. Peer support was tremendous. Without a supportive family, you can’t make it,” she remarks.
A Career That Prepared the Ground
Dr. Namukose’s PhD sits atop a formidable professional foundation. She holds Bachelor’s and Master’s degrees in Agriculture from Makerere University, a Postgraduate Diploma in Food and Nutrition Security from Wageningen University in the Netherlands, and a Postgraduate Diploma in Business Administration from Makerere University Business School. She has undergone extensive training in nutrition leadership, research methods, health systems, and quality improvement across Africa, Europe, and Asia.
Within the Ministry of Health, she has served as a Public Health Nutritionist, Senior Nutritionist, Principal Nutritionist, and now Assistant Commissioner, coordinating national nutrition interventions, designing training modules, mobilising resources, and overseeing district implementation.
She has played key roles in multi-million-dollar initiatives, from HIV-Free Survival programmes to Integrated Child Health Days, public food procurement policy, and the scale-up of Multiple Micronutrient Supplements (MMS) for pregnant women.
Her research has been published in leading peer-reviewed journals, including PLOS ONE and BMC Health, Population and Nutrition, ensuring that her findings speak both to policy and global evidence.
On a mission to keep research from gathering dust
Now a Doctor of Philosophy, Dr. Namukose has determined that her work will not sit quietly on a shelf. Her findings have already informed Uganda’s Health Sector Nutrition Strategic Plan, strengthening the case for financing, governance reform, and recruitment of skilled nutrition cadres. She continues to champion platforms, such as national nutrition symposia, that bring student research into policy dialogue and implementation spaces.
“Very often, excellent student research is left on the shelves. I plan to allocate some days during these symposia to nutrition students to showcase best practices and innovations,” she says.
Adding that, “I urge mothers and their infants to actively engage in self-care, growth-promotion, and monitoring activities to improve their own health and that of their children.”
Central to her recommendations is a call to embed nutrition services within routine health and community systems, with sustained government leadership, financing, and competent human resources.
Integration, she insists, is not achieved by guidelines alone, but through continuous engagement with frontline health workers and communities.
As graduation day approaches, Dr. Namukose’s thoughts turn outward. To frontline health workers delivering nutrition services under pressure, her message is one of respect and reassurance. Even with limited resources, the assessments they conduct, the counselling they provide, and the care they offer can change outcomes.
“Endeavor to participate in training programmes whenever available to bridge gaps in nutrition knowledge and skills, including on-the-job and rotational training to support cost-effective and efficient nutrition service delivery,” she asks.
To mothers and caregivers, she urges active engagement in self-care, growth monitoring, and nutrition programmes, especially those strengthened through digital innovation.
And to policymakers, her research offers both evidence and urgency that nutrition integration is no longer optional but foundational to maternal and child health.

When Dr. Samalie Namukose walks across the stage at Freedom Square, followed by applause, the true weight of that moment lies in health facilities where nutrition is no longer an afterthought. In mothers whose pregnancies are better supported. In infants whose growth curves bend upward, quietly, decisively.
Among the 185 PhDs conferred at Makerere University’s 76th graduation, the School of Public Health Communications Office shares her story, which is a reminder that the most transformative scholarship is not always loud. It builds patiently, between policy meetings and midnight writing, between emergencies and examiners’ comments, until it transforms systems and lives from within.












This week, world leaders, negotiators and researchers are gathered in Antalya, Türkiye, for COP31, the United Nations climate conference, seeking to turn years of climate commitments into action countries can finance and implement. Among them is Dr. John Bosco Isunju, a climate and health researcher at Makerere University School of Public Health, named among TIME’s 100 most influential climate leaders in 2024.
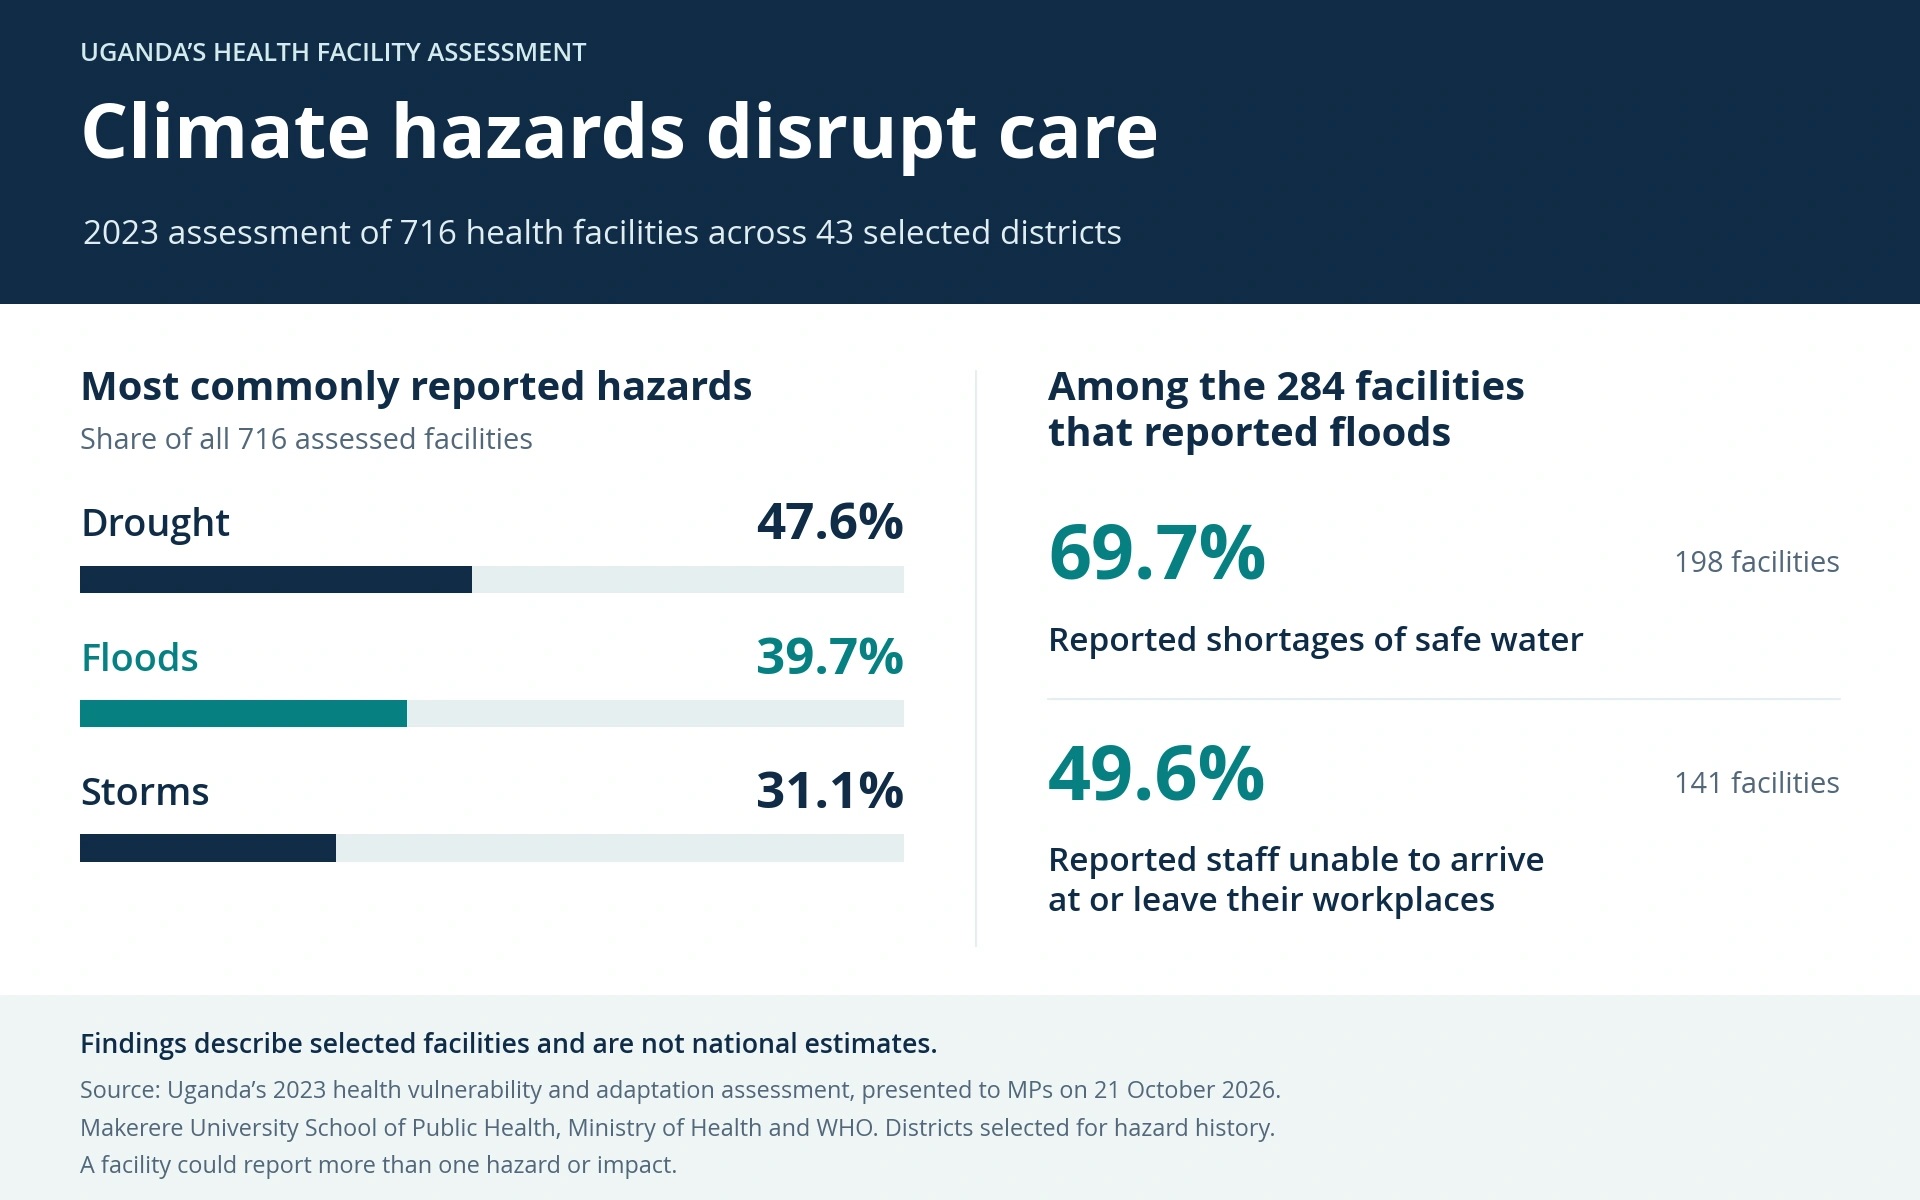
Dr. Isunju led the School’s technical support to the Ministry of Health for Uganda’s 2023 Climate Change Health Vulnerability and Adaptation Assessment (VAA) and the subsequent development of the Health National Adaptation Plan (H-NAP) 2025–2030. The assessment covered 716 health facilities across 43 districts, documenting vulnerabilities that helped shape the country’s priorities for protecting healthcare from climate hazards.

That experience speaks directly to the task before the 9–20 November summit. With “Dynamic and Resilient Health Systems” among the COP31 Presidency’s Action Agenda priorities, the conference is seeking practical solutions and financing to keep services functioning through climate shocks. Adaptation, the practical changes needed to cope with a changing climate, must ultimately reach the facilities where people seek care.
Protecting facilities from floods and drought also safeguards the public investment behind them, giving Uganda’s adaptation effort an economic significance alongside its importance to patients. In a 27 October 2026 statement ahead of COP31, UN Climate Change Executive Secretary Simon Stiell placed climate action within that wider calculation of public benefit.
“More governments are taking climate action right across their economies, to bank the vast benefits of clean energy and climate resilience,” he said. “Almost every major economy, and many medium-sized and smaller economies, now see climate action as a central driver of economic growth, jobs, and affordable and secure energy.”

On 21 October, nearly three weeks before the Antalya talks, the H-NAP was before Ugandan parliamentarians in Kampala. Convened by the Ministry of Health and Parliamentary Forum on Climate Change Uganda, with support from Regenerate Africa and the Clinton Health Access Initiative, the engagement examined the plan and Parliament’s role in securing funding, scrutinising implementation and ensuring accountability.
Presenting the VAA, Dr. Isunju explained that the team examined the hazards facing each area, the extent of exposure and the weaknesses that made services vulnerable. They also considered the communities the facilities served. A flood could turn an already difficult journey to treatment into one that patients and staff could no longer make, as seen in many parts of Uganda, including Kasese.
“Either health workers will not work, or communities will not be able to access care, or outreaches will not be possible because roads are cut off,” he told legislators.

Uganda’s H-NAP grew out of commitments made at COP26 in Glasgow in 2021 to assess health vulnerabilities and develop an adaptation response. The Ministry of Health commissioned the School to undertake the VAA in 2023, with Rockefeller Foundation funding supporting both the assessment and the plan’s development. Developed through stakeholder consultation, with WHO technical support and contributions from other partners, the plan was launched on 22 August 2024.
What the assessment found
The VAA found that drought and floods were disrupting the conditions needed to deliver care. Nearly half of the assessed facilities reported drought exposure, while about two in five reported floods. Among the 284 facilities reporting flood exposure, 141 (about half) said health professionals had been unable to arrive at or leave their workplaces, and 198 (about seven in ten) reported shortages of safe water. Because districts were selected for their history of hazards, these findings describe the assessed facilities and cannot be treated as national estimates.
The H-NAP responds across ten components of the health system, including leadership, workforce training, risk monitoring and sustainable financing. Its proposed actions include revising infrastructure standards and using weather and disease information to warn of health risks earlier. Protecting care requires investment in buildings alongside the people and systems that make them function.
“A significant proportion of healthcare facilities lack water management and safety plans to address contamination risks,” the H-NAP states. “They lack water safety plans and contingency plans for monitoring and reducing contaminants as well as on-site water purification equipment.” Such gaps can leave facilities unable to maintain hygiene, clean equipment and provide treatment safely when water supplies fail or become contaminated.
The H-NAP already includes a budget, giving implementation a basis for resource mobilisation. The UN climate secretariat’s 2026 report on national adaptation plans across sectors identifies the difficulty of turning priorities into fundable projects. It recommends costing specific interventions and securing delivery partners, steps that can help advance Uganda’s health adaptation priorities.
At household level, climate pressures on livelihoods can leave families less able to get care or keep children in school, as community consultations showed.
“Their problems are interconnected. If climate, for example, affects their livelihoods, it directly impacts their health, because that means when they fall sick they can’t get care, and they can’t take their children to school, so things are all interconnected,” Dr. Isunju said.

The Ministry’s Focal Point for Climate Change and Health, Dr. Didacus Namanya, told MPs that resilience, the ability to withstand disruption and keep providing care, must inform how services are built and managed.
“So, our vision in the H-NAP is to have a responsive, adaptive, and resilient health system. Adaptive, we are talking about adaptation. These impacts will not stop; they will continue coming, but we must develop our adaptive capacity. The way we build our health facilities, the way we tackle the disease burden, we must be highly adaptive,” he said.
Dr. Namanya called for district-specific assessments, noting the different conditions in Nakasongola and Bududa, and described an ongoing review of infrastructure design standards. Dr. Isunju reported that guidelines for coordinating climate and health action across institutions were undergoing approval.
A partnership announced in October 2025 by the Rockefeller Foundation and the International Development Research Centre is helping the School and the Clinton Health Access Initiative, working with the Ministry of Health, build an investment case for H-NAP implementation. A separate Ministry of Health and Global Green Growth Institute initiative, begun in June 2026, is advancing climate-resilient water, sanitation and hygiene standards, investment plans for health facilities and the government’s capacity to deliver improvements.

Questions for Antalya
Legislators sought evidence of what implementation had delivered. Terego East MP Hon. Wilfred Babanga Erima asked how much of the plan had been implemented, how many facilities had been audited and refitted for climate resilience, and how funding was divided between domestic and donor sources. Hon. Shafiga Wanyenya, Vice Chairperson of Parliament’s Committee on Climate Change, proposed joint follow-up with the health committee and regular progress reviews.
“Our role is to ask the difficult questions and also identify implementation gaps, to advocate for the vulnerable communities and ensure that the national commitments translate into tangible improvements in the lives of our people,” Hon. Wanyenya said.

Those questions belong in Antalya too. The Yearbook of Global Climate Action 2026 identifies gaps in global data for assessing whether health systems are becoming more resilient, underlining the importance of tracking what adaptation efforts deliver for health.
The COP31 health programme links implementation of the Belém Health Action Plan with a financing framework intended to help turn health priorities into investable projects. Launched on 9 November, the Antalya Initiative for Health Resilience provides a platform for countries to share practical experience. The COP28 adaptation framework sets targets for climate-resilient health services by 2030 and progressively beyond, alongside national adaptation planning by 2030 and multi-hazard early-warning systems by 2027.
The H-NAP gives Uganda a practical agenda for that next stage. It calls for climate and health priorities to enter government budgets and for proposals capable of attracting finance. It also identifies academic partnerships as a route to research and capacity-building funds. Annual reviews would then assess progress and guide subsequent work.
As negotiations continue in Antalya, the next test is whether decisions there, and action at home, help keep care available, on the road to a health facility, and at the water point on which safe treatment depends.
Health
Makerere University’s Prof. Peter Waiswa Appointed to WHO Technical Working Group on Essential Child Health Services


Health
Mak Staff Receive Prestigious International “Future of the Field” Recognition in Global Research Administration Class of 2026.


-

 General1 week ago
NOTICE: Online Applications for Government Sponsorship for Programmes Offered at Public Universities & Other Tertiary Institutions 2027/2028 AY
-

 General2 weeks ago
Makerere Marks 2026 International Day of Persons with Disability – Lord Mayor Balimwezo Delivers Keynote
-

 Health2 weeks ago
Mayuge Study Finds NCD Risks Emerging in Adolescence, and Shows Early Action Can Help
-

 Agriculture & Environment1 week ago
Zambia readies to host the 22nd RUFORUM AGM in the Capital Lusaka
-

 General1 week ago
Makerere-Rotary Launch Student Food for Peace Initiative