
Health
Harriet Aber’s Research Uncovers Uganda’s Hidden Crisis of Child Substance Use


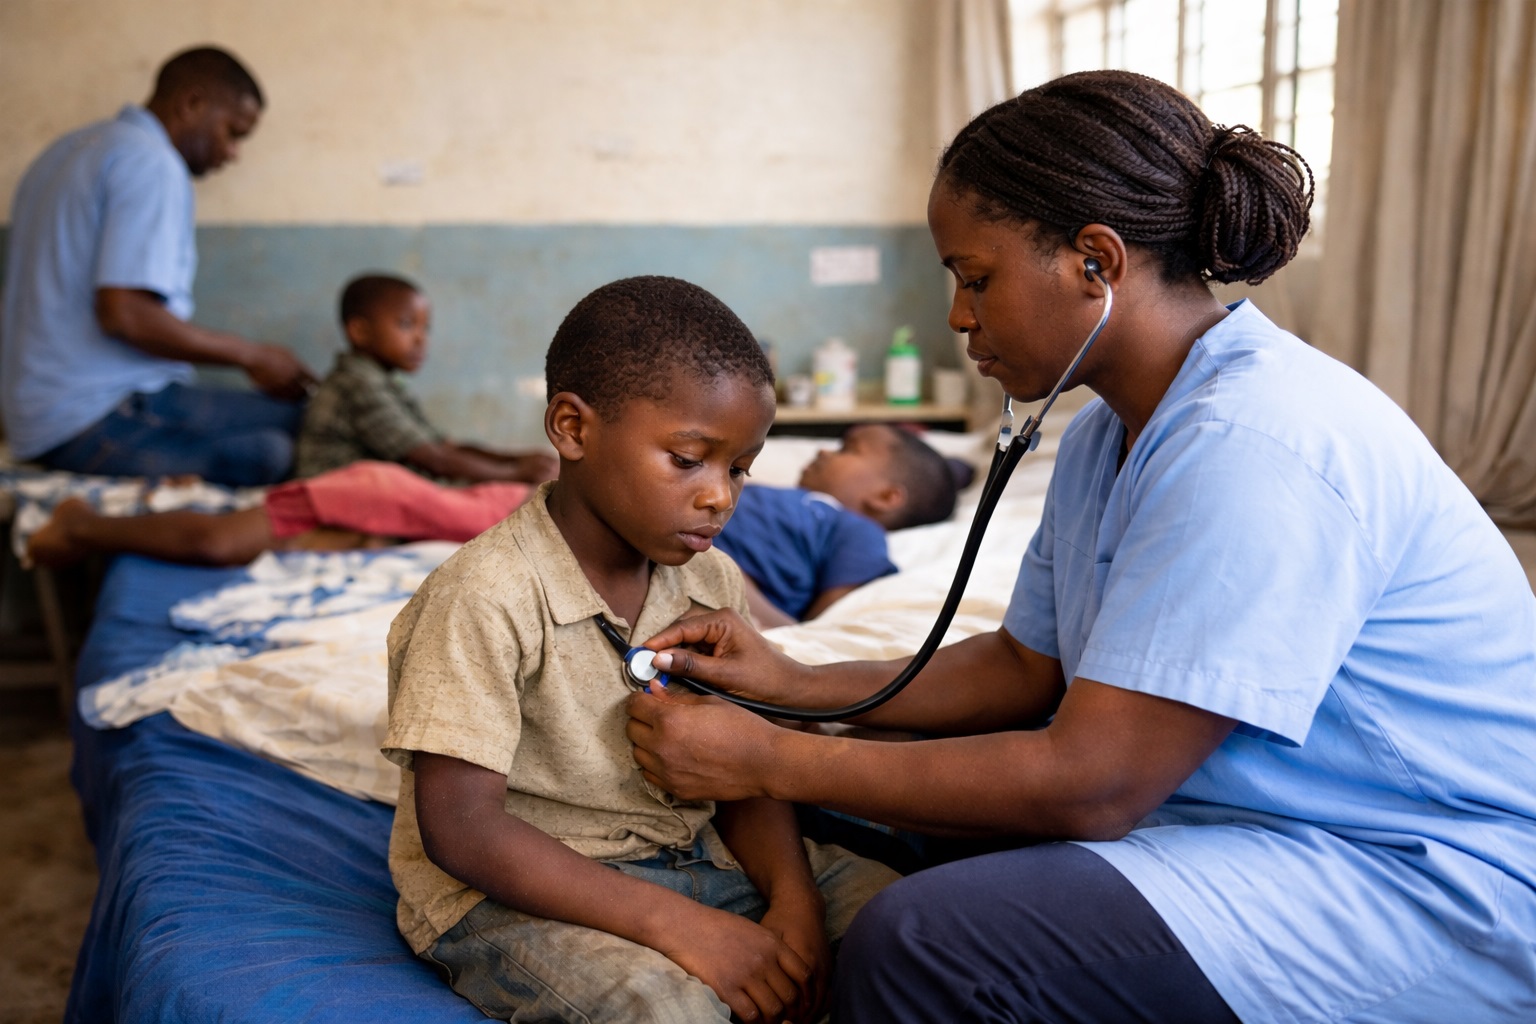
In Uganda, children arrive at health facilities every day with fever, cough, injuries or routine illnesses. What health workers rarely recognise is that some of these children are already living with alcohol or other substance use disorders, conditions that complicate diagnosis, delay treatment, and quietly undermine children’s health, development, and long-term wellbeing.
This hidden reality was uncovered by Dr. Harriet Aber Odonga during her doctoral research at Makerere University School of Public Health (MakSPH). Her PhD study, titled “Substance Use among Children in Mbale, Uganda: Health System Landscape and Support Structures,” examined how Uganda’s health system detects and responds to substance use among children aged six to 17 years.
The findings revealed a problem far more widespread than many health workers and caregivers assumed. Nearly one in four children attending health facilities showed signs of alcohol or other substance use problems, with alcohol the most common substance. In the study, a child was classified as having a “probable” substance use disorder when responses to a standard screening questionnaire indicated harmful or dependent patterns of use requiring further clinical assessment.

The discovery adds urgency to an already serious public health challenge. Globally, alcohol and other substance use is responsible for one in five deaths and contributes to more than 200 disease and injury conditions, according to WHO. Across Africa, alcohol alone accounts for 6.4 per cent of all deaths and 4.7 per cent of disability-adjusted life years. In Uganda, alcohol use disorder affects roughly 7.1 per cent of the population and contributes to about 7% of all deaths, while research among young people shows that alcohol exposure often begins early in life.
Despite these risks, most policy and research attention has historically focused on adults and older adolescents. Much less is known about children who begin experimenting with alcohol and other substances earlier in their childhood, a gap Aber set out to examine by studying how Uganda’s health system identifies and responds to substance use among children.
A research question begins
Aber’s interest in the subject began unexpectedly. “I remember seeing a notice calling for PhD students to research child alcohol use,” Dr. Aber recounted. “The phrase struck me immediately. I could not believe that children were drinking alcohol. That moment sparked my curiosity, so I began reviewing the literature on the subject in Uganda. During that search, I came across a study documenting alcohol use among children as young as five years old. That finding was deeply unsettling and raised many questions for me.”
With a longstanding interest in child health, Aber saw the research as an opportunity to investigate a problem that had received little systematic attention. What began as disbelief developed into a doctoral investigation examining how Uganda’s health system identifies and responds to substance use among children. She began her doctoral studies in 2021 at MakSPH under the supervision of Dr. Juliet N. Babirye, Prof. Fred Nuwaha, and Prof. Ingunn Marie S. Engebretsen from the University of Bergen, Norway. She defended her thesis on October 25, 2025, before graduating during Makerere University’s 76th graduation ceremony on February 25, 2026.

Investigating the health system response
Aber’s study examined four key questions. It measured how common substance use disorders are among children visiting health facilities. It assessed whether health facilities are equipped to screen and manage these cases. It evaluated whether screening tools are acceptable to children, caregivers, and health workers. It also examined how families seek help when children begin using substances.
To answer these questions, the research used a mixed-methods design combining quantitative surveys and qualitative interviews. Aber collected data from 834 children attending health facilities in Mbale District, assessed 54 health facilities in the district to determine their readiness to screen and manage substance use disorders, and interviewed health workers, caregivers, and children to understand experiences of care and barriers to seeking help. Additional surveys involving 602 children and 355 caregivers examined help-seeking patterns and support structures.
Quantitative data were analysed to estimate prevalence and identify associated risk factors, while qualitative interviews provided insight into how families, communities and health workers respond when children begin using substances.
What the research found

Data collected between 2023 and 2024 across health facilities in Mbale District in Eastern Uganda showed that substance use among children was far more common than many health workers and caregivers assumed. Alcohol use disorder emerged as the most prevalent form of substance use disorder among children in the study. The analysis also showed that children were significantly more likely to use substances if they were exposed to peer or sibling use, lived in lower-income households, or experienced strained relationships with caregivers.
The research also revealed major health system gaps. Only 19 of the 54 health facilities assessed, representing 35 per cent, met the minimum readiness criteria required to screen, diagnose or manage substance use disorders. Many facilities lacked trained staff, standardised screening guidelines, and clear referral pathways for specialised care.
Aber explained that substance use often goes undetected because it is rarely the primary reason children visit health facilities. “Substance use is hidden,” she asserted, reflecting on evidence from her doctoral study. “While health workers are treating other illnesses, some children coming to these facilities are already struggling with alcohol or other substances.”
She added that early substance use can have lasting consequences for children’s development. “Risk was higher among children exposed to peer or sibling substance use, lower household income, lower caregiver education, and strained child-caregiver relationships. The public should be concerned because early substance use affects brain development, mental health, education completion, and long-term well-being.”
Families often navigate the problem alone

Her research also examined how families and communities respond when children begin using substances. She found formal help-seeking to be rare. Many caregivers relied on informal networks, including relatives, teachers, religious leaders, and local authorities. Health services were seldom the first point of support.
Meanwhile, punitive responses such as discipline or punishment were sometimes used by caregivers attempting to stop the behaviour of substance use among children, but these responses rarely addressed the broader social and family pressures influencing the vice.

One encouraging finding emerged from her study’s assessment of early detection tools. Aber evaluated the use of the CRAFFT screening tool, a short set of structured questions used by health workers to identify whether a child may be using alcohol or other substances. Children, caregivers, and health workers generally found the questions from the tool easy to understand and acceptable to use. In the study, over 85 per cent of children reported the questions were easy to answer, and nearly nine in ten caregivers were comfortable with the screening process.
These findings, however, suggest that routine early detection could be integrated into primary healthcare within the communities. “If policymakers were to act on one finding from my research, I would prioritise integrating routine, age-appropriate substance use screening into primary healthcare,” Aber argued. “With proper training and referral systems, health workers can identify early risk and support children before the problem escalates.”
Training across nutrition, public health and health systems
Aber’s approach to the problem reflects a research journey shaped by training across multiple areas of child and public health. She first studied Food Science and Technology at Kyambogo University, graduating in 2011, before specialising in Nutrition during her Master of Public Health at Makerere University, graduating in 2015, before embarking on her doctoral training in Public Health at the School, completing in 2025 to graduate at Makerere University 76th Congregation.

Before beginning her PhD, she worked on nutrition research and later coordinated studies examining climate risks, anticipatory humanitarian action and community health systems. This background shaped how she approached substance use among children, not as an isolated behavioural problem but as an issue influenced by broader health and social conditions.
“I do not see child substance use as a problem with a single cause,” she noted. “It is influenced by biological, psychological, social, and system-level factors. My nutrition training helped me appreciate how substance use intersects with broader child health concerns such as mental health, family stress, and even food insecurity.” These pressures are visible in her research site in Mbale, where environmental shocks, economic hardship, and family instability persistently shape daily life. Recurrent landslides and livelihood disruptions place strain on households, and adolescents facing stress or instability may turn to substances as a coping mechanism, she holds.
From evidence to solutions
Completing her PhD has now shifted Aber’s perspective from documenting problems to identifying solutions for social impact. “Completing my PhD shifted my perspective from simply generating evidence to actively providing solutions,” she observed. “Child health challenges such as substance use, nutrition, and climate-related risks are interconnected. As a researcher, I have become more systems-focused, and as an advocate, I feel a stronger responsibility to ensure evidence informs policies that improve children’s wellbeing.”

For Aber, that responsibility extends to the families whose experiences informed the research. Parents, teachers, and health workers often notice behavioural changes first, even when they feel unprepared to respond. Listening without judgment, recognising warning signs, and linking children to appropriate support can make a significant difference, she noted, especially in a context where formal services remain limited.
Her research ultimately sends a clear message for Uganda’s health system. Children affected by substance use are already present in communities and health facilities. Detecting the problem earlier, strengthening screening systems, and equipping frontline health workers with appropriate tools could significantly improve outcomes for vulnerable children.
Behind the research journey stood a wide network of support, including MakSPH supervisors and doctoral committee, the TREAT consortium, the MakSPH PhD forum, the Health Development Centre secretariat, study participants, research assistants, family and friends, and funding support from the Government of Uganda through the Makerere University Research and Innovations Fund (MAKRIF) and the Norwegian Research Council, all of whom she remains grateful.
Aber’s research ultimately points to a critical gap in Uganda’s health system. Children affected by substance use are already present but remain largely invisible. Without routine screening, trained health workers, and clear referral systems, opportunities for early intervention are often missed. Addressing this gap, as indicated by her study, goes beyond clinical care. It requires strengthening how the health system recognises and responds to emerging risks that affect children’s long-term health and development.














Uganda’s latest national HIV survey reveals lower viral suppression among adolescents and young adults living with HIV than among older adults, even as the country records substantial improvements in controlling the virus. The findings come from Uganda Population-Based HIV Impact Assessment (UPHIA 2025), a national household survey examining HIV prevalence and whether people living with the virus know their status, receive treatment, and achieve viral suppression.
Releasing the preliminary UPHIA 2025 findings at the Uganda Media Centre on 1 October 2026, Minister of Health Hon. Dr. Chris Baryomunsi called for earlier prevention and testing, particularly among adolescent girls and young women, alongside support for treatment adherence. “We must reach out to the young people, ensure that they have information, they test, take treatment, and adhere to the treatment guidance,” he urged.
Hon. Baryomunsi recalled how fear had discouraged testing during his university years: “I remember when we were at university, we went for testing at the university hospital. We sat there for three hours. Some of us left without even testing because it was scary.” Today, he explained, “even if you test HIV positive, you can be initiated on treatment, and you live normally like the rest of those who don’t have HIV.”

UPHIA 2025 was locally led under the Ministry of Health’s overall leadership, with Makerere University School of Public Health serving as the prime implementer, a role ICAP at Columbia University held in the previous two surveys. The Uganda Bureau of Statistics led sampling, while the Uganda Virus Research Institute and National Health Laboratory and Diagnostic Services led laboratory operations. Regional referral hospitals and local governments supported implementation, and the U.S. government provided US$10 million through PEPFAR, along with technical assistance from the U.S. CDC.
UPHIA collected data from July to September 2025 among people aged 15 and above, including those outside routine treatment services. Of 6,283 eligible households, 94.4% completed interviews. Researchers interviewed 13,801 people and tested 13,477 for HIV.
Testing followed Uganda’s national algorithm, with laboratory confirmation of positive samples, viral-load measurement, and checks for antiretroviral medicines to establish treatment use. Researchers weighted the estimates to account for the sampling design. Participants received counselling and results, and those who tested positive were referred for treatment.
Hon. Baryomunsi thanked participants and their families for welcoming survey staff and contributing their time, information and samples, without which the national evidence would not have been available.

National progress and the youth gap
The survey estimated HIV prevalence, which means the proportion of people living with HIV, at 5.9% among those aged 15 and above, corresponding to about 1.496 million people in this age group nationwide. Prevalence was 7.3% among women and 4.1% among men, ranging from 1.3% in Karamoja to 8% in the South Western region.
Among people aged 15 and above living with HIV, 86% had achieved viral suppression, meaning a low amount of HIV in the blood, measured in UPHIA as fewer than 1,000 copies per millilitre. Suppression stood at 69.3% among adolescents and young adults aged 15–24 living with HIV, compared with 89.9% among those aged 50 and above. These estimates cover people living with HIV regardless of whether they know their status or receive treatment.

HIV prevalence among people aged 15–24 was 1.5%, including 2% among young women and 1% among young men. Among young women, prevalence was 1.3% at ages 15–19 and 2.8% at ages 20–24. These differences support attention to earlier prevention and testing, although they do not establish when infections occurred.
The highest prevalence estimates occurred among middle-aged adults: 15.7% among women aged 40–44 and 11.7% among men aged 45–49. Lower suppression among young people therefore requires attention alongside the higher HIV prevalence among middle-aged adults. Comparing the same age group across both surveys, viral suppression among people aged 15–64 increased from 74.9% in 2020–21 to 86.1% in 2025, while HIV prevalence remained at 5.9%.

Diagnosis and the path to 2030
The treatment results identify diagnosis as the main national gap. Among people aged 15 and above living with HIV, 85.3% knew their status. Of those aware, 99.1% were receiving treatment; among those receiving treatment, 96.5% had achieved suppression.
The 95-95-95 targets aimed for 95% of people living with HIV to know their status, 95% of those diagnosed to receive treatment, and 95% of those receiving treatment to achieve viral suppression by 2025. Among people aged 15 and above, Uganda exceeded the treatment and suppression targets, while diagnosis remained below target. UNAIDS’s Global AIDS Strategy 2026–2031 retains these targets towards ending AIDS as a public health threat by 2030.
According to WHO, viral suppression protects health and helps prevent HIV transmission. Uncontrolled HIV weakens the immune system, increasing the risk of serious illness. With continued treatment as prescribed, sexual transmission risk is negligible when HIV remains suppressed but detectable, and zero when undetectable. The Uganda AIDS Commission estimated over 34,000 new HIV infections in 2025, underscoring the importance of early diagnosis, timely treatment, and sustained suppression alongside other prevention measures.

The demographic stakes are substantial. People aged 15–24 constituted 21.2% of Uganda’s population in the 2024 census. The country’s Fourth National Development Plan, covering 2025–2030, prioritises a healthy, knowledgeable, skilled and productive population and reducing HIV through primary health care. Protecting young people’s health, therefore, supports their participation in education, work, and national development; UPHIA helps identify where services need greater attention.
Turning evidence into action
The study’s conclusions identify three priorities: sustain treatment outcomes, find people unaware of their status, and improve suppression among younger people. Permanent Secretary Dr. Diana Atwine connected the findings to the Ministry’s planning.
“We do believe that these results are a true reflection of what is happening in our country as far as the HIV status is concerned, and we do believe that it will give us a very clear direction and the roadmap that we are going to take in the next five years to target and to get our targets achieved.”

Acting on these priorities requires funding for services and research. Hon. Baryomunsi outlined plans to target resources where needs are greatest, strengthen district services and align partner support with government priorities. Responding to journalists’ questions, he noted the government’s intention to increase domestic funding for the HIV response, including research.
“The HIV/AIDS response, including research and surveys such as this one, has largely been funded by partners in the past. The government of Uganda is committed to allocating more resources from our domestic budget to support the response and research,” he noted.
For the first time in the UPHIA series, the survey assessed selected noncommunicable disease indicators among people aged 15 and above: 15.5% had elevated blood pressure, 24.8% were overweight or obese, and 0.9% had raised random blood glucose. These screening findings align with the Ministry’s integration agenda and Hon. Baryomunsi’s call to bring HIV and chronic care services together to address people’s wider health needs.
Speaking at the release of the preliminary results, U.S. Embassy Chargé d’Affaires Mikael (Mika) Cleverley described UPHIA 2025 as the first Population-Based HIV Impact Assessment worldwide fully led and implemented by the country itself.

“The study was led by Ugandan scientists, Ugandan managers, Ugandan public servants, Ugandan field teams, from design to data collection to analysis. And this is what two decades of focused strategic U.S. foreign investments in the public health sector was meant to produce, is to reinforce Ugandan leadership and Ugandan-led efforts.”
At the survey launch on 29 May 2025, MakSPH Dean Prof. Rhoda Wanyenze highlighted the partnership’s contribution: “The partnership between Makerere University and CDC has not only helped build national capacity in surveillance and epidemiology, but has also strengthened our ability to lead high-quality, large-scale national surveys.”

The Dean added: “After two decades of joint work, we are proud that UPHIA is now a fully Ugandan-led effort. This is critical to the sustainability of the skills and knowledge generation to inform our local response.”
UPHIA 2025 shows how far Uganda’s HIV response has advanced and where gaps remain. As the country works towards ending AIDS as a public health threat by 2030, reaching young people with testing, treatment, and continued care will be essential to extending those gains.

Read the full UPHIA 2025 summary results here:



Uganda has released the preliminary findings of the 2025 Uganda Population-Based HIV Impact Assessment (UPHIA 2025), a national household survey that provides a current picture of the country’s HIV response and selected non-communicable disease indicators.
At the Uganda Media Centre today, 1 October 2026, the Minister of Health, Hon. Dr Chris Baryomunsi, released the preliminary results and said the evidence would guide policy, resource allocation and service improvement, with particular attention to people and communities with the greatest gaps. He urged Ugandans to know their HIV status, use prevention services and, when diagnosed, start treatment promptly and adhere to it.
Among adults aged 15 years and above, HIV prevalence was 5.9 percent, including 7.3 percent among women and 4.1 percent among men. Among adults aged 15–64, prevalence was also 5.9 percent, unchanged from 2020/21. Across the country, prevalence ranged from 1.3 percent in Karamoja to 8.0 percent in the South Western region. Of adults living with HIV, 85.3 percent knew their status; 99.1 percent of those aware were on treatment; and 96.5 percent of those on treatment had achieved viral load suppression. HIV-status awareness remains the central gap in the 95-95-95 cascade.
The survey also measured selected non-communicable disease indicators for the first time. Elevated blood pressure affected 15.5 percent of adults, while 24.8 percent had overweight or obesity and 0.9 percent had raised blood glucose.
Conducted from July to September 2025, UPHIA 2025 was the first population-based HIV impact assessment to be fully country-led. The Ministry of Health provided overall leadership, while Makerere University School of Public Health served as the prime implementing organisation, working with UVRI, UBOS, regional referral hospitals and local governments. PEPFAR funded the survey through the U.S. CDC.
Watch the UPHIA 2025 preliminary results launch:
https://www.youtube.com/live/QfHFBaJ-L-w
Read the UPHIA 2025 summary results:
https://drive.google.com/file/d/1nElGNwgcAcZyAo9CLCQKRpO2jJgyxjSc/view?usp=drive_link
-

 General2 weeks ago
Call for Applications: RLRH Graduate Traineeship Programme
-

 General6 days ago
Statement on Concerns Circulating Regarding a Member of Academic Staff
-

 Research2 weeks ago
Call for Makerere Staff PhD Completion Grant Applications, 2026-27
-

 Engineering, Art & Tech2 weeks ago
Public Art Talk Sparks Dialogue on Contemporary Art Practices at MTSIFA
-
 General1 week ago
Makerere Marathon 2026 – Running to Equip the Disability Support Center