
Health
82% Stressed: Uncovering the Hidden Mental Health Burden Among Kampala’s Taxi Drivers


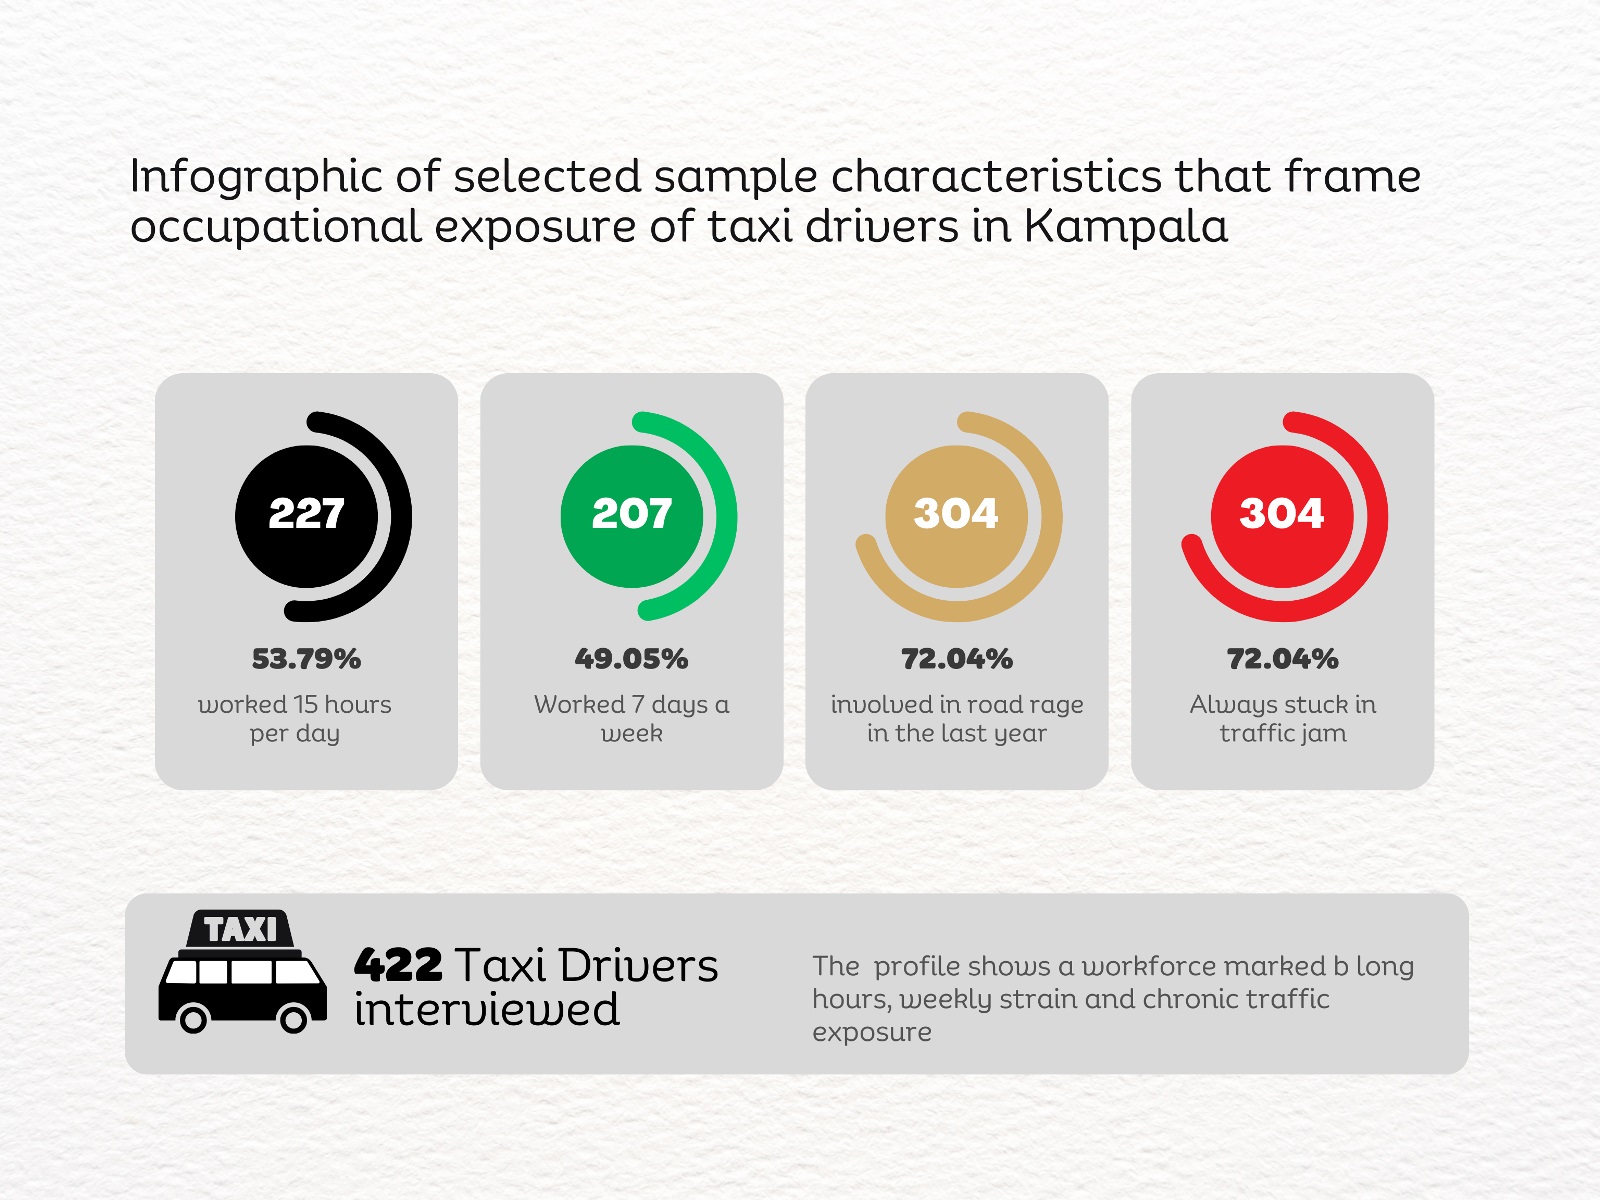
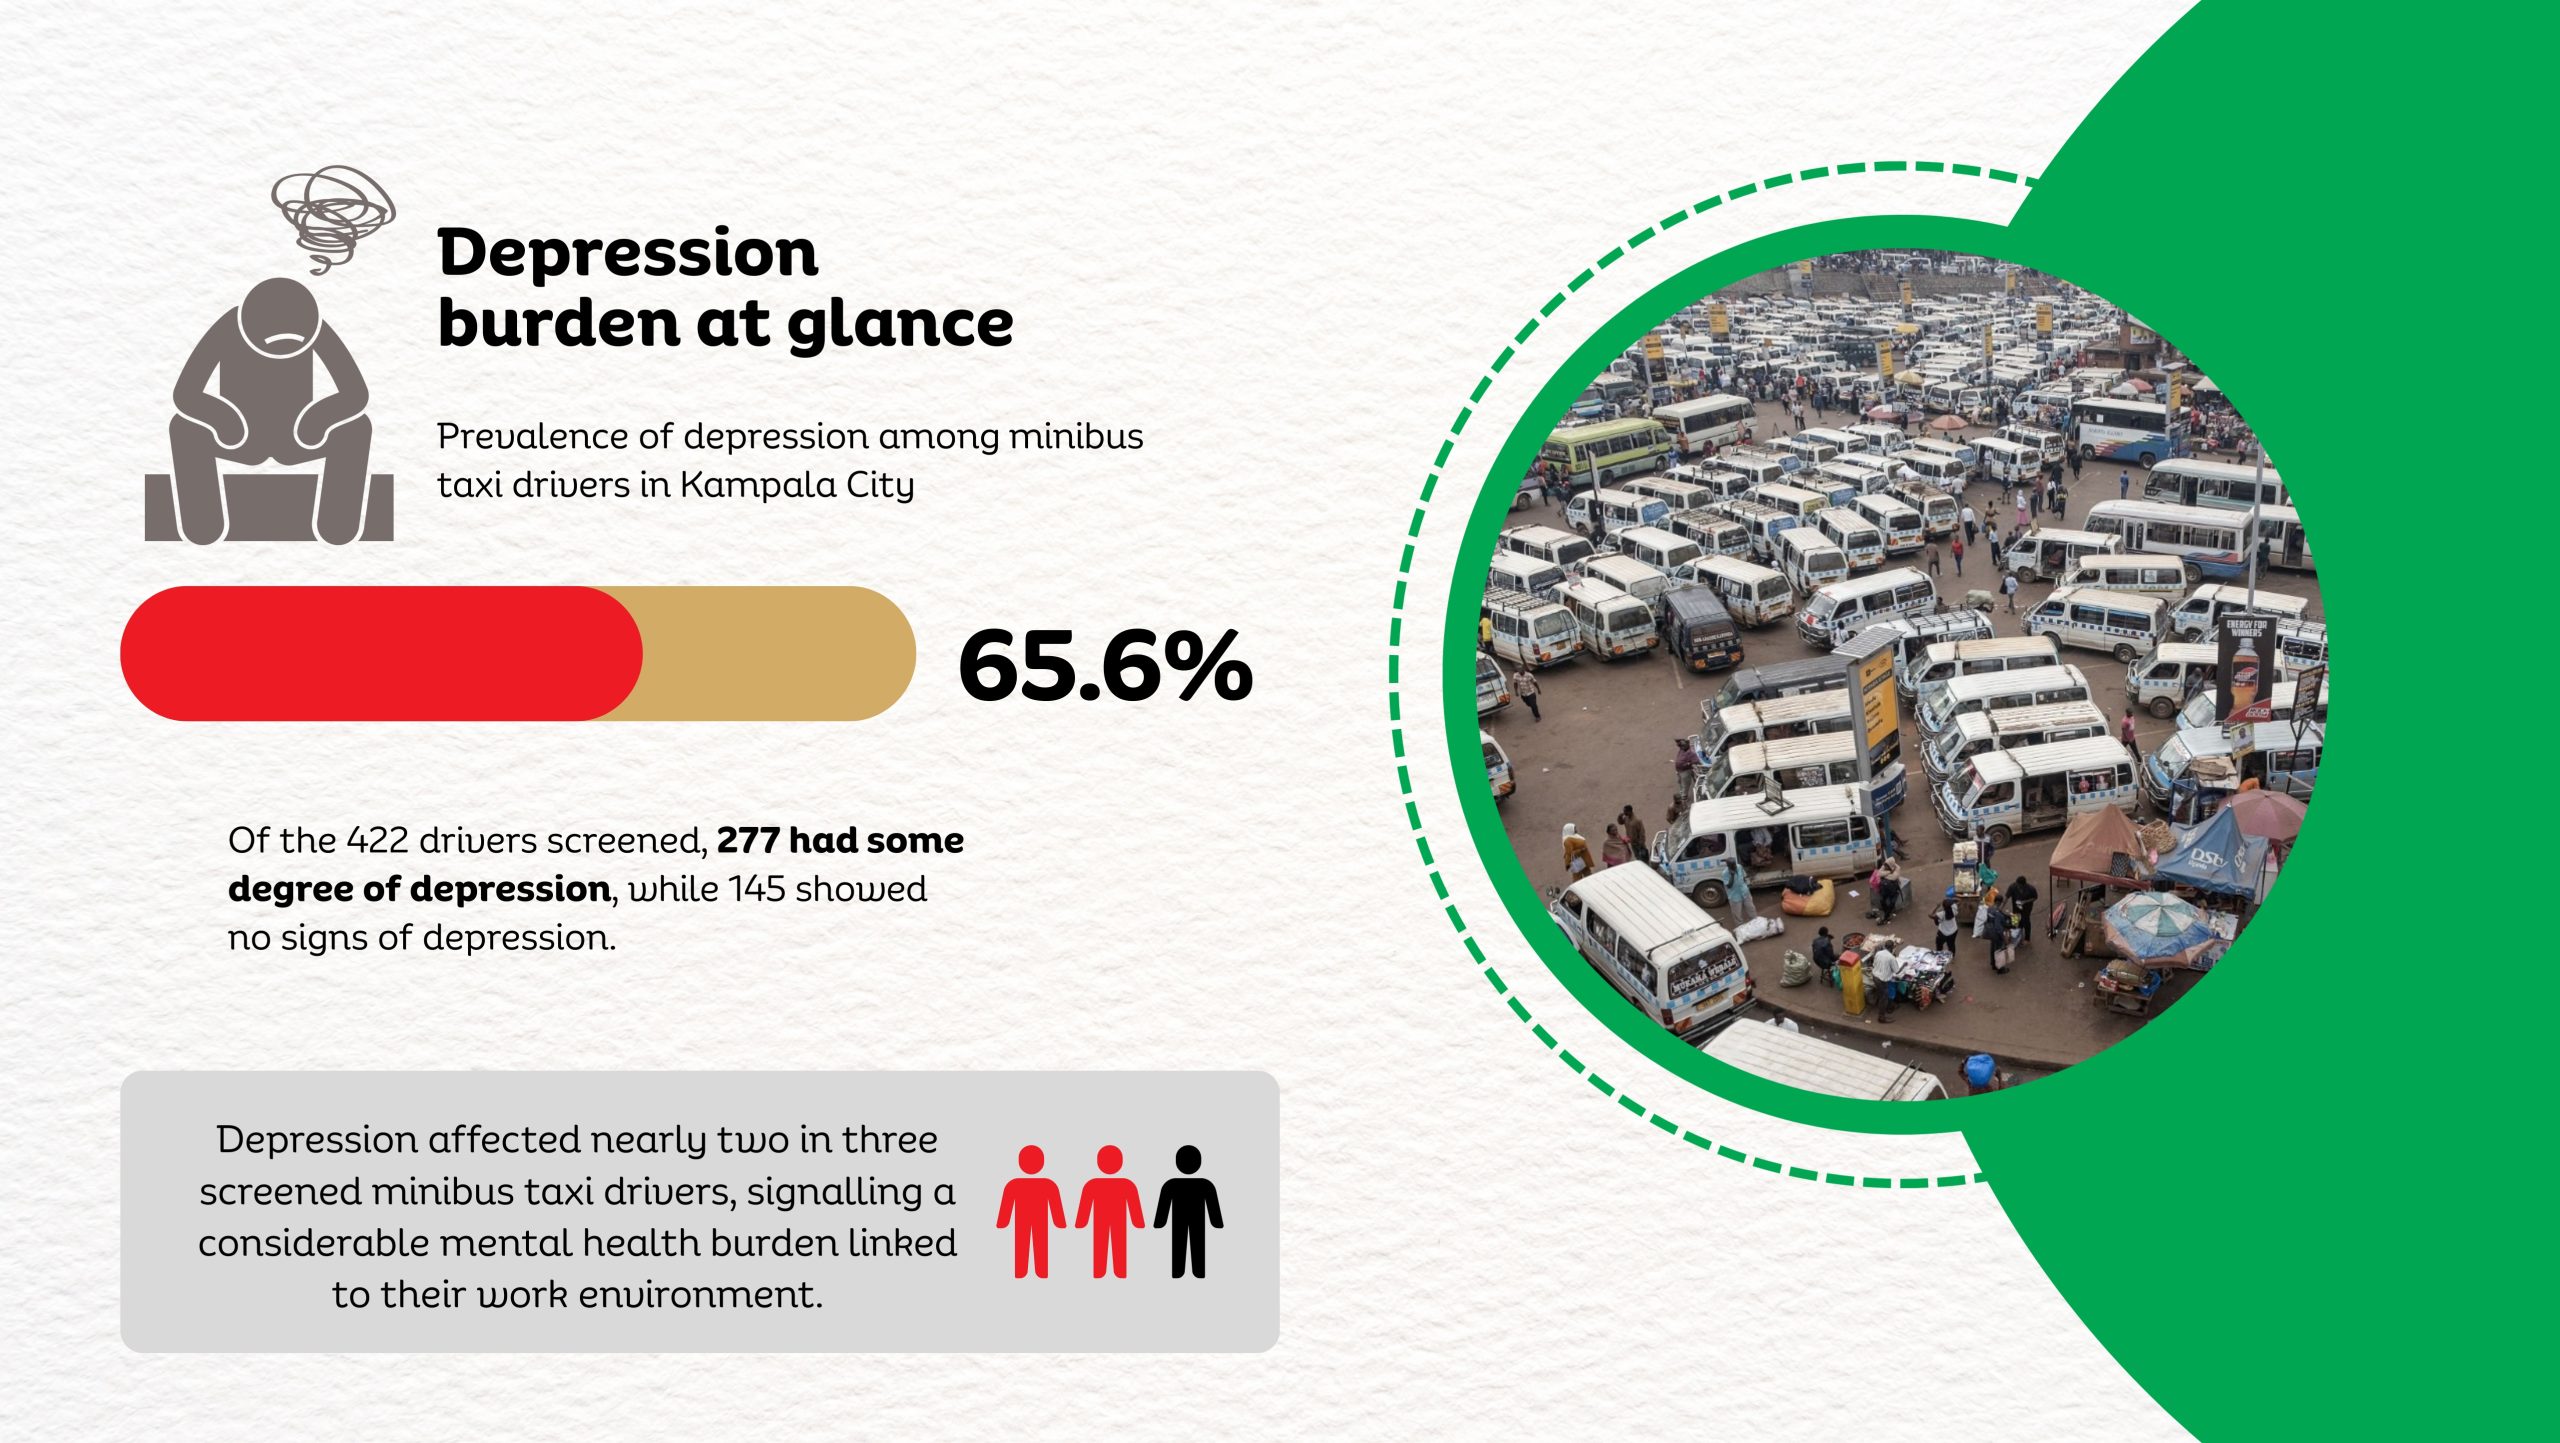
A new study by Dr. Linda Kyomuhendo Jovia, a medical doctor and graduate of the Master of Public Health programme at Makerere University School of Public Health, has found high levels of psychological distress among minibus taxi drivers operating in Kampala’s major taxi parks. In a cross-sectional survey of 422 drivers across Old, New, Kisenyi, Usafi, Namirembe, Nakawa, and Nateete parks, nearly two-thirds screened positive for symptoms of depression (65.6%), while anxiety affected more than 70%, and stress an estimated 82%. The findings point to a largely overlooked occupational health concern within the city’s informal transport sector, where long working hours, economic pressure, poor sleep, and prior road accidents were associated with higher levels of mental strain.
Before sunrise settles over Kampala, Old Taxi Park is already awake. White minibuses marked with the blue stripe of Uganda’s public service taxis sit jammed bumper to bumper, their noses pointed toward narrow exits that will soon release them into the city’s traffic. Dust clings to the windows. Torn seats peek through sliding doors. Diesel hangs low in the air. Conductors slap the metal sides of vans and shout destinations into the morning.
“Kireka! Banda! Bweyogerere!” The calls overlap until they become a steady roar.
Passengers squeeze through narrow corridors between vehicles where there was never meant to be walking space. Hawkers weave through the crowd with trays of roasted maize and boiled eggs. Somewhere, a small radio crackles. Nearby, two conductors argue over whose turn it is to load passengers. This scene is how Kampala wakes, in diesel fumes, shouted destinations, and the quiet urgency of people trying to earn a living before the traffic tightens its grip on the day.
Handwritten route boards fixed to the taxis signal their destinations: Masaka “A” Stage, Kaguta Road, Nakawa, Namirembe, Ntinda, Gayaza, Nansana, and Entebbe, guiding passengers through the organised chaos of the park. Behind every steering wheel sits someone doing the arithmetic of survival. Drivers wake before dawn to secure a place in the queue. For many, sleep is short, interrupted, and rarely restorative. The day stretches across long hours of traffic, uncertain earnings, rent, school fees, and taxi levies, including annual payments of about UGX 720,000. Passengers today mean dinner tonight. Yet inside the noise of the taxi parks, another story has remained largely invisible.
Across Uganda, an estimated 400,000 taxis move millions of passengers every day, forming the backbone of the country’s informal transport system. But almost nothing is known about the psychological toll on the drivers who keep it running.
That gap is what drew Dr. Kyomuhendo into Kampala’s taxi parks. What she uncovered were levels of depression, anxiety, and stress far higher than many had imagined.
A Medical Doctor Turning Toward Public Health
Born on 23 July 1994 to Mr. Muhigwa Lawrence and Ms. Kataito Jacqueline, Dr. Kyomuhendo grew up in Hoima District in western Uganda. Her early education took her from St. Christina Nursery School to Budo Junior School before she continued to Trinity College Nabbingo and later Mount Saint Mary’s College Namagunga for Advanced Level, where she studied Biology, Chemistry, and Mathematics.
In 2014, she earned a government scholarship through the Public Universities Joint Admissions Board and enrolled for a Bachelor of Medicine and Bachelor of Surgery at Busitema University, graduating in 2019.
During her medical internship at Masaka Regional Referral Hospital, she began noticing a troubling pattern in the cases arriving at the wards: road traffic injuries, complications of chronic diseases, severe malaria in children, and obstetric emergencies that might have been prevented with earlier intervention. Many of the crises doctors were treating, she realized, had begun long before patients reached the hospital. “They were symptoms of deeper problems,” she recalls.
Public health offered a way to investigate those underlying causes. In 2022, she enrolled in the Master of Public Health Distance programme at Makerere University School of Public Health, where students are trained to examine health problems not only at the bedside but across entire populations. Guided by Associate Professor Lynn Atuyambe, a respected scholar in Community Health and Behavioural Sciences at MakSPH, and Dr Juliet Kiguli, Senior Lecturer and public health anthropologist, the student’s work benefited from strong academic stewardship.

Uganda’s road transport system is dominated by motorcycles and 14-seater minibus taxis. About 15,000 operate in the Kampala Metropolitan Area alone.
These drivers navigate congested roads, pollution, erratic traffic patterns, and long working hours. Their workday often begins before dawn and stretches deep into the evening.
“They are important in Uganda’s transport industry,” Kyomuhendo said. “Yet they seem to be overlooked in our society.”
While commuting through Kampala during her studies, she began to notice the lives of taxi drivers. Arguments between passengers and conductors were common. When tensions rose, someone would eventually mutter the same question in Luganda.
“Oba abasajja ba takisi baabaki?” loosely to mean, ‘What is wrong with taxi men?’
The question lingered, and in June 2024, social media campaigns marking Men’s Mental Health Awareness Month pushed her to think about the issue differently. What if the behaviour many passengers dismissed as impatience or aggression was linked to something deeper? To her, taxi drivers seemed an unlikely but revealing group to study.
“They carry the responsibility for passengers’ lives every day,” she says. “Yet very little attention is paid to their own well-being.”

For instance, Kampala City Authority (KCCA) documents that between 2019 and 2024, geolocated crash data reveal a dangerous road environment in which Kampala’s taxi drivers operate daily. A total of 1,878 vulnerable road users, including pedestrians, motorcyclists, and cyclists, were killed in crashes involving motor vehicles, with buses and minibuses linked to 281 deaths, most of them pedestrians (147) and motorcycle occupants (131). Fatalities were heavily concentrated along major corridors such as Jinja Road, Kibuye–Natete Road, Bombo Road, and Ggaba Road, while for pedestrians, the most dangerous segments included Gayaza Roundabout (Kalerwe) and Kyebando Police Post along the Northern Bypass and Entebbe Road, where fatality densities reached 27–28 deaths per kilometer. These patterns highlight the high-risk traffic environments in which taxi drivers work, specifically busy arterial roads and bypass intersections where pedestrians, boda bodas, and public transport vehicles compete for space. These conditions contribute to the broader pressures that shape drivers’ safety, well-being, and mental health.
Research in the taxi parks
Her dissertation set out to answer two questions: how common are depression, anxiety, and stress among taxi drivers in Kampala, and what factors contribute to them? The study surveyed 422 male drivers across seven major taxi parks: Old, New, Kisenyi, Usafi, Namirembe, Nakawa, and Nateete, using a multistage sampling approach designed to ensure representation across the city’s transport hubs.
Participants completed structured interviews on socio-demographic, occupational, lifestyle, use of habit-forming substances, medical, and environmental factors. Mental well-being was assessed using the Depression Anxiety Stress Scale (DASS-21), a widely used screening tool in mental health research.
The data were analysed using statistical models that allowed Kyomuhendo to examine how occupational conditions, lifestyle factors, and health status interacted to shape mental well-being.
The study reflected the epidemiological training embedded in MakSPH’s Master of Public Health programmes, where students are encouraged to investigate real-world health challenges through evidence-based research.
Conducting interviews inside the taxi parks meant stepping into one of the most unpredictable environments in the city. “The atmosphere was survival for the fittest,” Kyomuhendo recalls.
Stories behind the statistics
The fieldwork brought moments that stayed with her long after the questionnaires were completed. One driver laughed when asked how he coped with stress. “I don’t drink or smoke,” he said, suggesting that multiple relationships were his way of managing the emotional strain of the job.
The answer was not in the questionnaire, and they both laughed. Yet the moment captured something deeper about life in the taxi parks: humour often hides exhaustion.
Another driver told her he had spent years buying herbal medicine for a hernia that never healed. Every month, he spent close to 100,000 shillings, hoping the treatment would eventually work. She advised him to seek hospital care, a conversation that stayed with her.
“Sometimes people spend far more trying to manage a problem than it would cost to treat it properly,” she explains.
When the data were analysed, nearly two-thirds of the drivers screened positive for symptoms of depression. More than 70 percent had symptoms of anxiety, and over 80 percent reported levels of stress. The psychological burden was far heavier than most people had assumed.
Several factors stood out. Drivers who had experienced road accidents in the previous year were significantly more likely to report depression. Chronic medical conditions and a family history of mental illness also increased the risk.
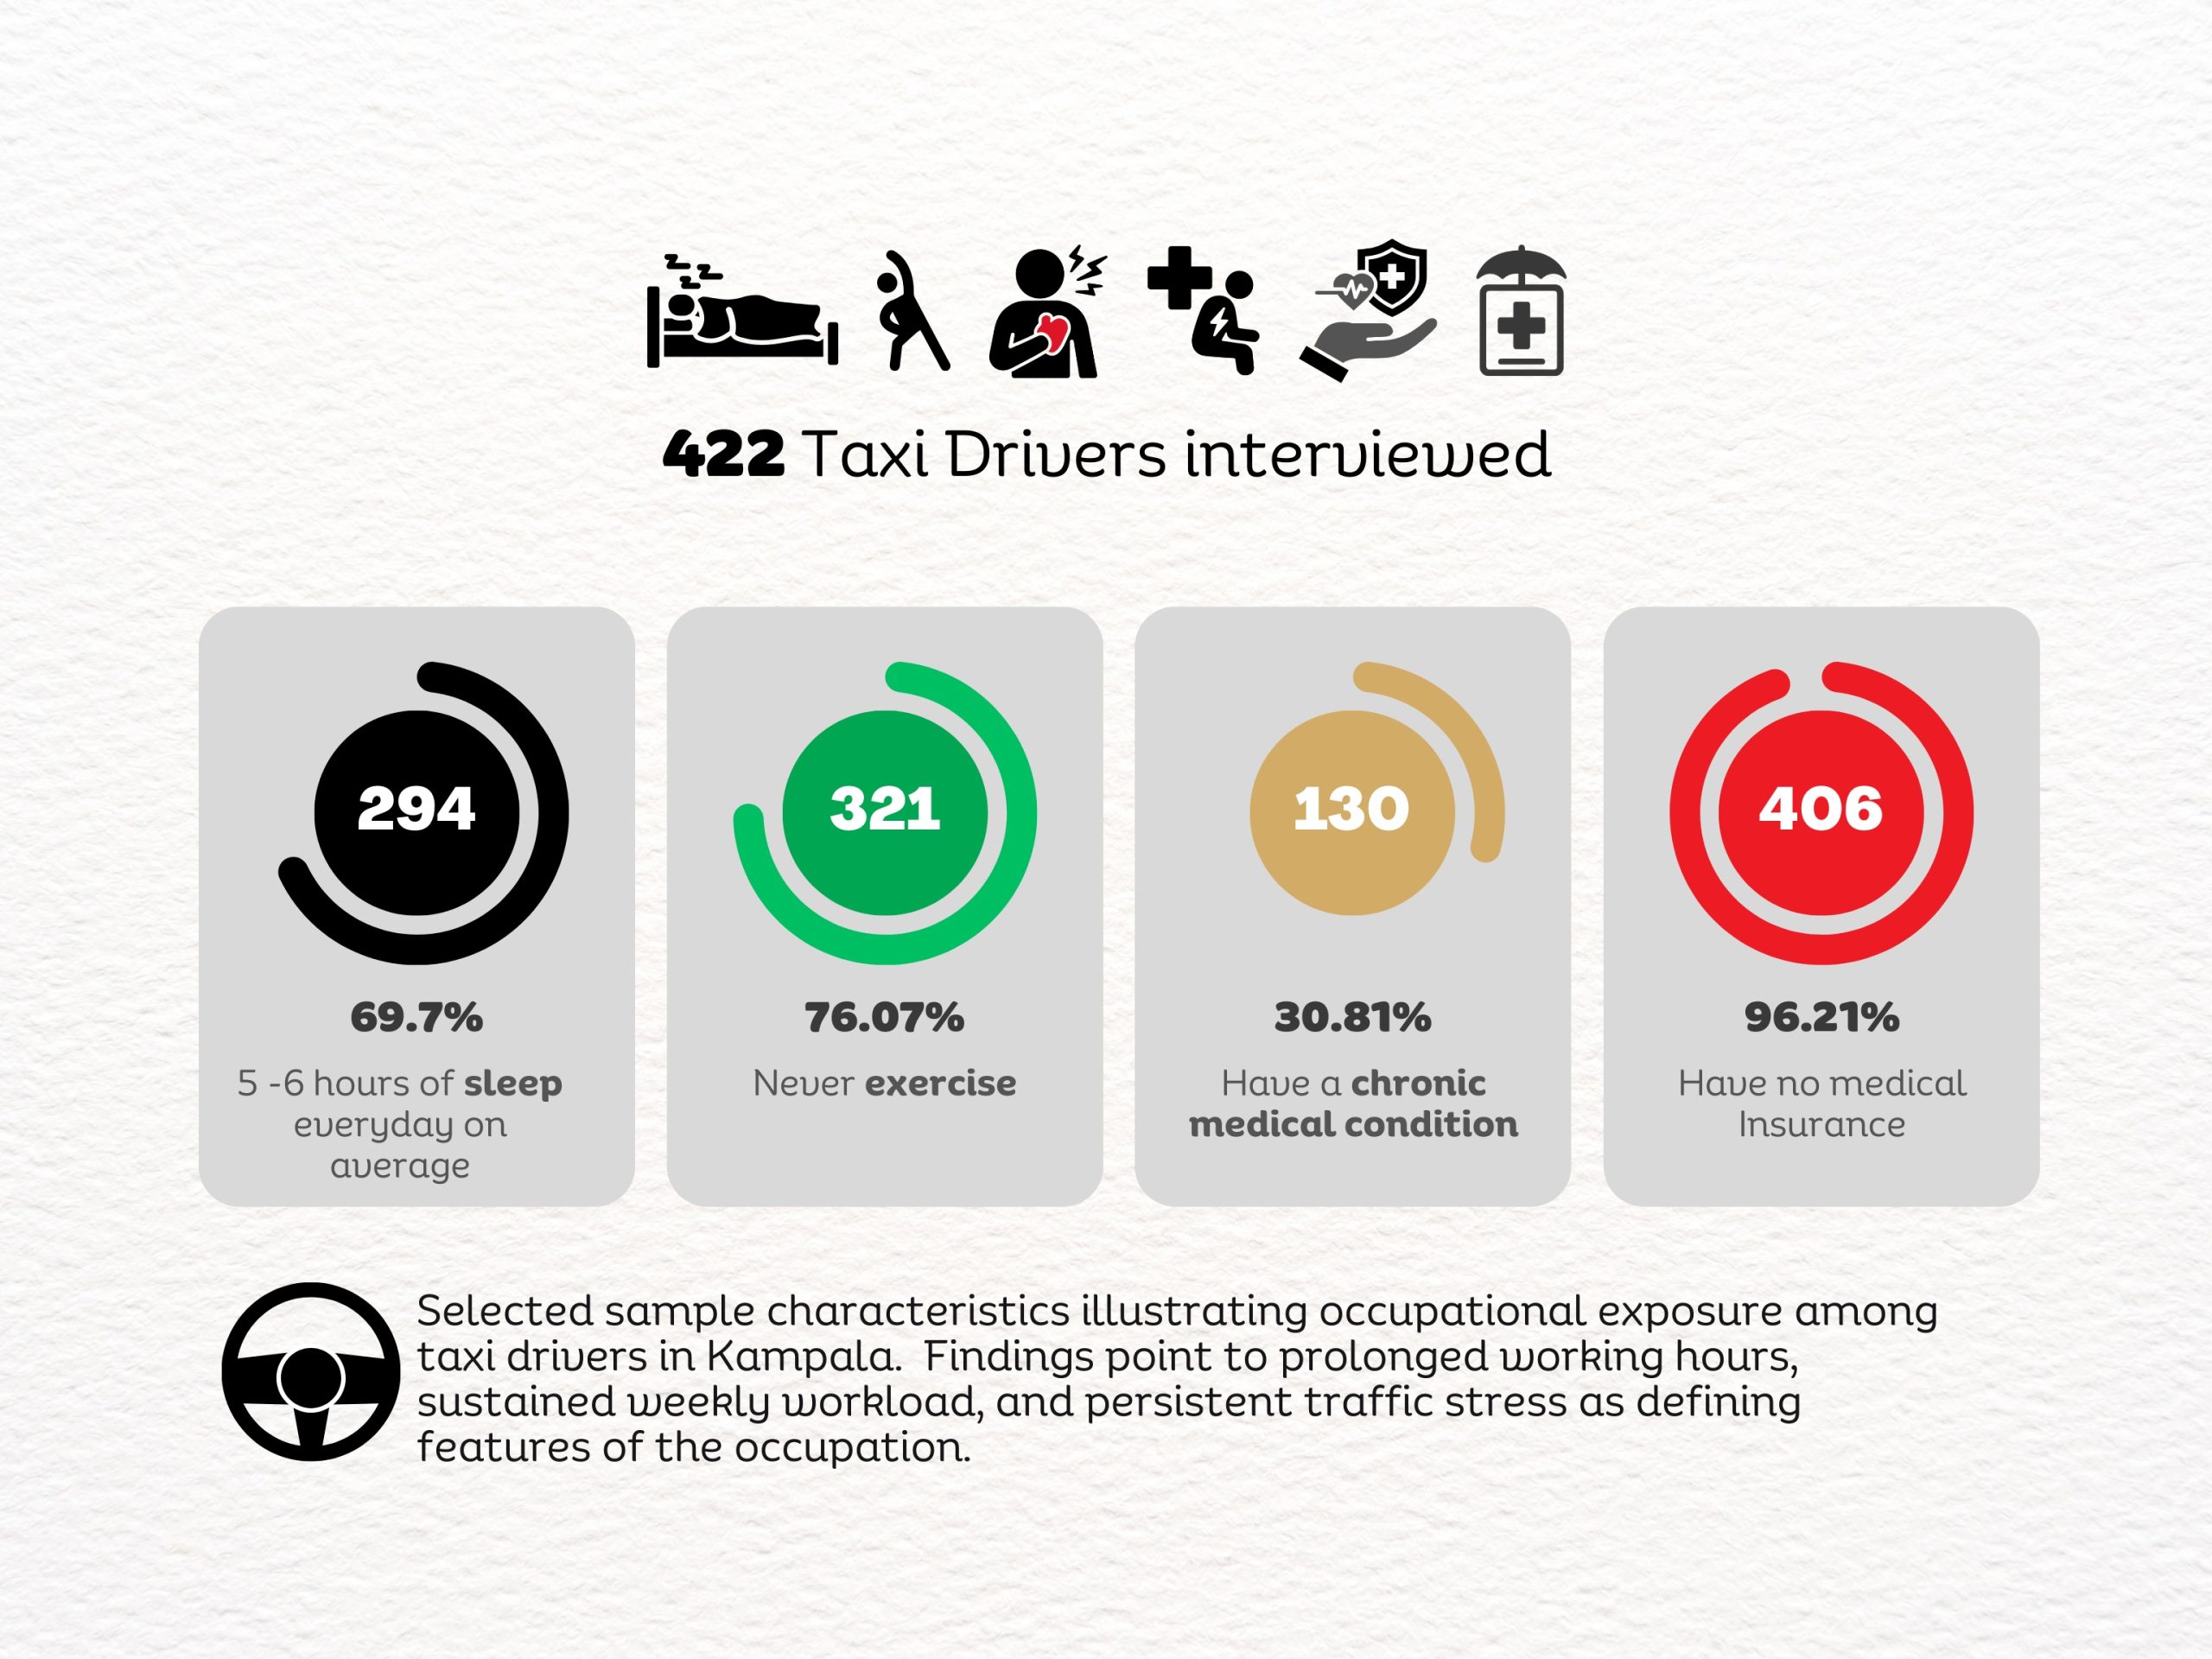
Sleep deprivation emerged as one of the most important predictors. Drivers who consistently slept fewer than seven hours per night were far more likely to report anxiety and stress. Also, economic security mattered. Drivers who owned their vehicles were substantially less likely to experience anxiety compared to those who rented taxis or paid daily remittance fees to vehicle owners. In other words, psychological distress followed the same lines as economic pressure.
More than a transport problem, and the silence around men’s mental health
The implications extend beyond the drivers themselves, she observed. Mental health affects concentration, reaction time, and decision-making. All abilities that are critical for safe driving in a city known for congestion, unpredictable traffic, and frequent road hazards, including flooding, among others.
“If drivers are anxious or sleep-deprived,” Kyomuhendo explains, “there is a risk they may struggle to follow traffic rules or respond quickly to hazards.”
In a transport system that carries millions of passengers daily, the well-being of drivers becomes a matter of public safety. The findings suggest that mental health among taxi drivers should be treated as both an occupational health issue and a transport policy concern.
During interviews, Kyomuhendo noticed another pattern. Few drivers openly described themselves as depressed or anxious. Instead, stress appeared through jokes, casual references to alcohol or relationships, or long pauses followed by silence.
Men’s mental health remains a difficult subject in many communities. “Men’s mental health is a serious public health issue that should not be ignored,” she says.
Breaking the stigma will require awareness campaigns, stronger occupational protections, and greater attention from both health authorities and transport regulators, she proposes.
A different way of seeing the city?
This research also changed how Kyomuhendo sees Kampala. Where passengers notice congestion or impatience, she now sees the pressures shaping the people behind the wheel. “It made me appreciate the men who show up every day and work hard despite their struggles,” she says.
One driver confided in her about the pressures of the job. “People will not help you unless they know the problems you are facing,” he said.
The city and its drivers
By late afternoon, the taxi parks are as crowded as they were in the morning. Conductors still shout destinations into the traffic. Engines idle in long rows of white vans waiting for passengers. Drivers lean against steering wheels, hoping the next arrival will finally fill the vehicle.
The city keeps moving because they do. Most passengers step into these taxis thinking only about where they are going—work, home, school, or the market. Few stop to consider the pressures carried by the people behind the wheel.
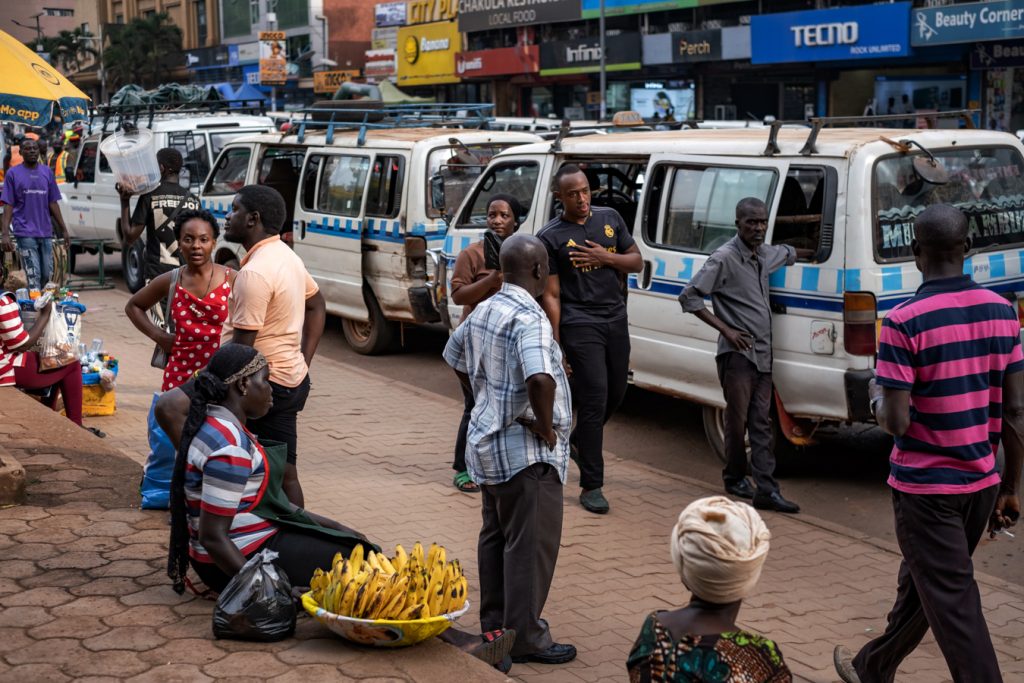
Yet Kyomuhendo’s research suggests that beneath the noise of the taxi parks and those car hoots on the streets lies something far quieter and far less visible: a level of stress, anxiety, and depression that touches not only the drivers themselves but also the safety of the passengers they carry and the communities they serve.
Each morning, the vans will still line up bumper-to-bumper. Conductors will still shout destinations into the traffic. Kampala will still climb inside and move.
If nearly half a million taxis keep Uganda moving every day, who is protecting the minds of the people behind the wheel?














Makerere University’s School of Public Health (MakSPH) showcased research, training and international partnerships supported through European Union funding during the EU Uganda Research and Study Fair 2026 held at Makerere University.
The fair brought together students, researchers, academics, government representatives and development partners to explore opportunities in education, research, innovation and international collaboration, while celebrating 50 years of partnership between Uganda and the European Union.
Through its exhibition, MakSPH highlighted research and capacity building initiatives addressing public health challenges including infectious diseases, non communicable diseases, health systems, climate change and pandemic preparedness.
18 EU funded projects supported at MakSPH
Prof. Rhoda Wanyenze, Dean of Students, School of Public Health, said the School has benefited from 18 EU funded projects over the past five years, supporting research and training across several areas of public health.

She said the projects have contributed to the training of PhD researchers and the development of research addressing infectious diseases and prevention, non communicable diseases, health systems, climate change and health.
Prof. Wanyenze also highlighted a new five year programme which started in 2021 that is aiming at strengthening capacity for research on pandemic preparedness and response, including outbreaks such as Ebola.

Another programme being undertaken with the Ministry of Health and Karolinska Institute focuses on improving maternal health while also addressing adolescent pregnancy and the health of mothers and children.
She described partnerships as critical to advancing science and innovation, noting that collaboration allows researchers in Africa and Europe to share knowledge and strengthen the impact of research on communities.
Research partnerships strengthen innovation
Prof. Robert Wamala, Director of the Directorate of Research, Innovation and Partnerships at Makerere University, said the exhibition provided an opportunity to showcase EU funded projects across the University.
He noted that the School of Public Health alone has more than 18 such projects, while other colleges also have several EU supported initiatives.

One of the projects showcased was PREPARE TID, a partnership aimed at developing rapid diagnostic technologies for emerging and re emerging infectious diseases.
Prof. Julius Okuni, Associate Professor of Veterinary Pathobiology and Molecular Diagnostics at Makerere University, said the project brings together universities, industries and other organisations from Africa and Europe.
The project is working to develop technologies that can quickly identify pathogens responsible for outbreaks such as Ebola, Rift Valley fever and Crimean Congo haemorrhagic fever.
According to Prof. Okuni, Makerere is involved in field and laboratory work to test and refine the technologies before they can be delivered to end users.
Fair provides platform for research visibility
For researchers at MakSPH, the fair also provided an opportunity to increase the visibility of ongoing research and create new connections with researchers, policymakers and potential funders.
Dr. Raymond Tweheyo, Honorary Lecturer and Senior Research Fellow in the Department of Health Policy, Planning and Management, said such exhibitions allow researchers to share their work and identify others working on related challenges.

He cited the CONNECT for Health project, which focuses on transforming non-communicable disease care in Uganda through collaboration with partners across several countries.
Dr. Tweheyo said exhibitions can help researchers connect with policymakers, civil society organisations and other partners who can contribute to translating research into practical solutions.
Assoc. Prof. Angelina Kakooza Mwesigye, Associate Professor and Child Neurologist at Makerere University College of Health Sciences, also emphasised the importance of exposing young people to international research opportunities.
She said the long standing Uganda Europe partnership provides opportunities for the next generation of researchers to learn, build networks and prepare for future research collaborations.
The School of Public Health’s participation highlighted the role of international partnerships in strengthening research capacity, supporting innovation and developing evidence based responses to Uganda’s public health challenges.


Uganda has strengthened its ability to respond rapidly to Ebola and Marburg outbreaks once cases are confirmed, but delays in frontline detection, health worker exposure, emergency financing bottlenecks and incomplete implementation of lessons from previous outbreaks continue to undermine preparedness, a study has found.
The findings were presented today, October 6, 2026, during a country validation workshop convened by the Meeting Targets and Maintaining Epidemic Control (EPiC) project, to examine lessons from Uganda’s response to filovirus disease outbreaks. The study was undertaken by Makerere University School of Public Health and FHI 360.
Presented by Dr. Steven Kabwama, the synthesis examined Uganda’s experience with recurrent Ebola virus disease (EVD) and Marburg virus disease (MVD) outbreaks between 2000 and 2026, drawing particularly on After-Action Reviews from the 2017 Marburg outbreak and the 2019, 2022 and 2025 Ebola outbreaks. The work seeks to consolidate recurring strengths, weaknesses, innovations and lessons that had previously been documented separately.

Uganda has recorded 12 filovirus outbreaks over the 26-year period, including nine Ebola and three Marburg outbreaks, according to the research team. Among the four outbreaks examined closely were the 2017 Marburg outbreak in Kween and Kapchorwa, the cross-border Ebola outbreak in Kasese in 2019, the multi-district Sudan Ebola virus outbreak in 2022, and the 2025 outbreak whose index case was a health worker.
Strong systems after confirmation
Across the outbreaks reviewed, the synthesis found that Uganda has developed significant capacity to mobilise after laboratory confirmation. National and district task forces and technical response structures are activated quickly, supported by strong laboratory capacity, established coordination mechanisms and increasingly sophisticated surveillance systems.
The country has also built laboratory capacity around the Uganda Virus Research Institute, mobile laboratories, genomic sequencing, sample referral systems and the Results Dispatch System. Digital surveillance tools, Village Health Teams, survivor champions and established national and district coordination structures have further strengthened response capacity.
Detection remains a weak point
However, the findings point to a critical problem before confirmation: recognising a possible outbreak early enough.
For outbreaks originating within Uganda, the synthesis found that the period between a patient’s first presentation and confirmation ranged from nine to 27 days. This the study found is linked to low clinical suspicion and weaknesses in screening. Other recurring challenges included delayed access to emergency financing, infections among health workers, disruptions to essential health services, community mistrust and stigma, and limited follow-through on recommendations from previous After-Action Reviews.
Opening the workshop, the Dean, Prof. Rhoda Wanyenze, said understanding these delays requires going beyond identifying broad weaknesses to examining where response systems fail in practice.
“We can identify a broad challenge such as delayed detection from the literature, but your experience on the ground can help us understand the specific factors that create that challenge,” Prof. Wanyenze said while addressing district health officials from across the country.

“When we begin looking for solutions, we need to be able to target the actual problems rather than simply identifying broad challenges.”
The workshop brought together partners and colleagues from districts, including people directly involved in outbreak response, to validate the synthesis against frontline experience. Prof. Wanyenze noted that published literature, scientific papers and response reports cannot capture every operational reality, making practitioner experience essential to understanding where delays occur and what interventions have worked. Remarks validation workshop
Turning outbreak experience into continuous readiness
Among the priority actions proposed are stronger screening and alert systems for earlier detection; ring-fenced emergency financing and more reliable responder payment systems; routine infection prevention and control training; stronger occupational protection for health workers; continued investment in laboratories and genomic sequencing; and preparedness extending beyond districts traditionally considered outbreak hotspots. The study also recommends stronger community engagement and a formal mechanism to track and finance implementation of recommendations from After-Action Reviews.

Dr. Andrew Acero, Director of the EPiC project at FHI 360’s Uganda Office said the central challenge is ensuring that experience accumulated during successive outbreaks translates into lasting institutional capacity.
“The real value lies in ensuring that what we learn changes what we do. Our findings should inform policy, shape guidelines and training, strengthen systems and ultimately improve practice.”
He noted that preparedness cannot begin only after an emergency has been declared, but must be built through sustained relationships, systems and capacity before outbreaks occur. Remarks validation workshop
The EPiC project is led by FHI 360 with core partners including Right to Care, Palladium and Population Services International.


Uganda’s latest national HIV survey reveals lower viral suppression among adolescents and young adults living with HIV than among older adults, even as the country records substantial improvements in controlling the virus. The findings come from Uganda Population-Based HIV Impact Assessment (UPHIA 2025), a national household survey examining HIV prevalence and whether people living with the virus know their status, receive treatment, and achieve viral suppression.
Releasing the preliminary UPHIA 2025 findings at the Uganda Media Centre on 1 October 2026, Minister of Health Hon. Dr. Chris Baryomunsi called for earlier prevention and testing, particularly among adolescent girls and young women, alongside support for treatment adherence. “We must reach out to the young people, ensure that they have information, they test, take treatment, and adhere to the treatment guidance,” he urged.
Hon. Baryomunsi recalled how fear had discouraged testing during his university years: “I remember when we were at university, we went for testing at the university hospital. We sat there for three hours. Some of us left without even testing because it was scary.” Today, he explained, “even if you test HIV positive, you can be initiated on treatment, and you live normally like the rest of those who don’t have HIV.”

UPHIA 2025 was locally led under the Ministry of Health’s overall leadership, with Makerere University School of Public Health serving as the prime implementer, a role ICAP at Columbia University held in the previous two surveys. The Uganda Bureau of Statistics led sampling, while the Uganda Virus Research Institute and National Health Laboratory and Diagnostic Services led laboratory operations. Regional referral hospitals and local governments supported implementation, and the U.S. government provided US$10 million through PEPFAR, along with technical assistance from the U.S. CDC.
UPHIA collected data from July to September 2025 among people aged 15 and above, including those outside routine treatment services. Of 6,283 eligible households, 94.4% completed interviews. Researchers interviewed 13,801 people and tested 13,477 for HIV.
Testing followed Uganda’s national algorithm, with laboratory confirmation of positive samples, viral-load measurement, and checks for antiretroviral medicines to establish treatment use. Researchers weighted the estimates to account for the sampling design. Participants received counselling and results, and those who tested positive were referred for treatment.
Hon. Baryomunsi thanked participants and their families for welcoming survey staff and contributing their time, information and samples, without which the national evidence would not have been available.

National progress and the youth gap
The survey estimated HIV prevalence, which means the proportion of people living with HIV, at 5.9% among those aged 15 and above, corresponding to about 1.496 million people in this age group nationwide. Prevalence was 7.3% among women and 4.1% among men, ranging from 1.3% in Karamoja to 8% in the South Western region.
Among people aged 15 and above living with HIV, 86% had achieved viral suppression, meaning a low amount of HIV in the blood, measured in UPHIA as fewer than 1,000 copies per millilitre. Suppression stood at 69.3% among adolescents and young adults aged 15–24 living with HIV, compared with 89.9% among those aged 50 and above. These estimates cover people living with HIV regardless of whether they know their status or receive treatment.

HIV prevalence among people aged 15–24 was 1.5%, including 2% among young women and 1% among young men. Among young women, prevalence was 1.3% at ages 15–19 and 2.8% at ages 20–24. These differences support attention to earlier prevention and testing, although they do not establish when infections occurred.
The highest prevalence estimates occurred among middle-aged adults: 15.7% among women aged 40–44 and 11.7% among men aged 45–49. Lower suppression among young people therefore requires attention alongside the higher HIV prevalence among middle-aged adults. Comparing the same age group across both surveys, viral suppression among people aged 15–64 increased from 74.9% in 2020–21 to 86.1% in 2025, while HIV prevalence remained at 5.9%.

Diagnosis and the path to 2030
The treatment results identify diagnosis as the main national gap. Among people aged 15 and above living with HIV, 85.3% knew their status. Of those aware, 99.1% were receiving treatment; among those receiving treatment, 96.5% had achieved suppression.
The 95-95-95 targets aimed for 95% of people living with HIV to know their status, 95% of those diagnosed to receive treatment, and 95% of those receiving treatment to achieve viral suppression by 2025. Among people aged 15 and above, Uganda exceeded the treatment and suppression targets, while diagnosis remained below target. UNAIDS’s Global AIDS Strategy 2026–2031 retains these targets towards ending AIDS as a public health threat by 2030.
According to WHO, viral suppression protects health and helps prevent HIV transmission. Uncontrolled HIV weakens the immune system, increasing the risk of serious illness. With continued treatment as prescribed, sexual transmission risk is negligible when HIV remains suppressed but detectable, and zero when undetectable. The Uganda AIDS Commission estimated over 34,000 new HIV infections in 2025, underscoring the importance of early diagnosis, timely treatment, and sustained suppression alongside other prevention measures.

The demographic stakes are substantial. People aged 15–24 constituted 21.2% of Uganda’s population in the 2024 census. The country’s Fourth National Development Plan, covering 2025–2030, prioritises a healthy, knowledgeable, skilled and productive population and reducing HIV through primary health care. Protecting young people’s health, therefore, supports their participation in education, work, and national development; UPHIA helps identify where services need greater attention.
Turning evidence into action
The study’s conclusions identify three priorities: sustain treatment outcomes, find people unaware of their status, and improve suppression among younger people. Permanent Secretary Dr. Diana Atwine connected the findings to the Ministry’s planning.
“We do believe that these results are a true reflection of what is happening in our country as far as the HIV status is concerned, and we do believe that it will give us a very clear direction and the roadmap that we are going to take in the next five years to target and to get our targets achieved.”

Acting on these priorities requires funding for services and research. Hon. Baryomunsi outlined plans to target resources where needs are greatest, strengthen district services and align partner support with government priorities. Responding to journalists’ questions, he noted the government’s intention to increase domestic funding for the HIV response, including research.
“The HIV/AIDS response, including research and surveys such as this one, has largely been funded by partners in the past. The government of Uganda is committed to allocating more resources from our domestic budget to support the response and research,” he noted.
For the first time in the UPHIA series, the survey assessed selected noncommunicable disease indicators among people aged 15 and above: 15.5% had elevated blood pressure, 24.8% were overweight or obese, and 0.9% had raised random blood glucose. These screening findings align with the Ministry’s integration agenda and Hon. Baryomunsi’s call to bring HIV and chronic care services together to address people’s wider health needs.
Speaking at the release of the preliminary results, U.S. Embassy Chargé d’Affaires Mikael (Mika) Cleverley described UPHIA 2025 as the first Population-Based HIV Impact Assessment worldwide fully led and implemented by the country itself.

“The study was led by Ugandan scientists, Ugandan managers, Ugandan public servants, Ugandan field teams, from design to data collection to analysis. And this is what two decades of focused strategic U.S. foreign investments in the public health sector was meant to produce, is to reinforce Ugandan leadership and Ugandan-led efforts.”
At the survey launch on 29 May 2025, MakSPH Dean Prof. Rhoda Wanyenze highlighted the partnership’s contribution: “The partnership between Makerere University and CDC has not only helped build national capacity in surveillance and epidemiology, but has also strengthened our ability to lead high-quality, large-scale national surveys.”

The Dean added: “After two decades of joint work, we are proud that UPHIA is now a fully Ugandan-led effort. This is critical to the sustainability of the skills and knowledge generation to inform our local response.”
UPHIA 2025 shows how far Uganda’s HIV response has advanced and where gaps remain. As the country works towards ending AIDS as a public health threat by 2030, reaching young people with testing, treatment, and continued care will be essential to extending those gains.

Read the full UPHIA 2025 summary results here:
-

 General1 week ago
Statement on Concerns Circulating Regarding a Member of Academic Staff
-

 General1 week ago
Press Statement: Incident Involving Death of a Student at Makerere University
-
 General2 weeks ago
Makerere Marathon 2026 – Running to Equip the Disability Support Center
-

 General1 week ago
Beyond Map Size: Africa’s Agency Should Not Be Funded by Other People
-

 General2 weeks ago
JNLC Leadership Symposium Equips Young Leaders for Responsible and Transformative Leadership