Health
What works, what doesn’t work? Researchers uncover the effect of supporting districts to operationalise digital payments for vaccination campaign workers
Published
1 year agoon
By
Mak Editor
By Joseph Odoi
A motivated and satisfied health workforce is critical for the success of mass vaccination campaigns against diseases like polio. High-quality vaccination campaigns can interrupt disease transmission, especially during and after periods of disrupted health services, such as those caused by the COVID-19 pandemic.
In sub-Saharan Africa, most vaccination campaign healthcare workers (VCHWs) have historically been paid in cash. Cash payments are often plagued by delays in funds disbursement, leakages, theft risks, and limited financial transparency. These challenges can negatively affect vaccination coverage and worker satisfaction.
To address these challenges, many countries are transitioning to digital payment systems, which are perceived as faster, more convenient, traceable, reliable, and easy to implement. Digital financial systems are already being rolled out in countries including Côte d’Ivoire, Ghana, Mali, Congo, and the Democratic Republic of the Congo. Uganda, with a projected population of nearly 41.6 million, had over 30 million registered mobile money customers using e-cash in 2019.
While early rollouts of digital payments have been largely successful, their full impact on vaccination campaign workers had not been systematically evaluated.
From 2021 to 2024, Makerere University (Uganda) and the University of Dakar (Senegal), with support from the Gates Foundation and technical partners including the Solina Group, WHO AFRO, and the Ministries of Health and Finance in both embarked on an important journey of research under the Digital Health Payment Initiatives and Research (DHPI-R) Project in 28 countries in Sub Saharan Africa
To explore the experiences and lessons of polio vaccination campaign healthcare workers (VCHWs), both male and female, during the 2022 oral poliovirus vaccination campaign in Uganda, researchers led by Prof. Peter Waiswa (principal investigator), together with Margaret McConnell, Juliet Aweko, Daniel Donald Mukuye, Charles Opio, Maggie Ssekitto Ashaba, Andrew Bakainaga, and Elizabeth Ekirapa-Kiracho, with support from the Gates Foundation, conducted a study titled “The Effect of Supporting Districts to Operationalise Digital Payments for Vaccination Campaign Workers: A Cluster Randomised Controlled Trial During the 2022 Polio Vaccination Campaign in Uganda.”
This study examined whether supporting districts to implement electronic cash (e-cash) payments, instead of cash, increased e-cash usage and improved vaccine campaign healthcare workers’ (VCHWs) motivation and satisfaction during an oral poliovirus vaccination campaign in 2022 in Uganda.
The mixed method study now published in BMJ Global Health, September 2025 was conducted in 54 districts in Uganda that had set up the government e-cash payment platform by May 2022. It involved healthcare workers supporting the polio vaccination campaign, regardless of direct vaccine contact. This included nurses, clinicians (vaccinators), mobilisers, community health workers (village health team members), recorders, local council representatives, and supervisors. The unit of randomisation was the district, while the unit of enrolment and data collection was the individual worker.
Method and Setting
As part of this study , In November 2022, a total of 54 districts and 2,665 vaccination campaign healthcare workers (VCHWs) were enrolled in the study and randomly assigned to two groups. Intervention districts received training on using the government e-cash platform, including managing user roles, uploading beneficiary data, and generating payment reports.
The control districts received the standard support given to districts during mass vaccination campaigns from the MoH, MoFPED, WHO and other development partners. This support included group training on implementation of payments, provision of vaccination materials and financial aid.
The study collected data on how VCHWs were paid, their motivation, and their satisfaction with the payment method. Overall, 765 VCHWs in intervention districts and 589 in control districts received e-cash payments.
Findings
Mode of payment for the vaccination campaign healthcare workers
Overall, approximately half of the campaign workers, 50.8% (1354/2665) were paid digitally (e- cash), either using mobile money or via the bank (online supple mental table 2). Payment by e- cash was higher among females, 53.9% (656/1215) compared with males, 48.1% (698/1450) and was lowest among campaign workers aged 30–39 years, 48.7% (368/765). E- cash payment was higher in the intervention arm at 57.5% (765/1,330) in comparison to the control arm at 44.1% (589/1,335).
Satisfaction with payment received during the campaign
Only 36.5% (705/1930) of the VCHWs were satisfied with the payment received during the campaign, with satisfaction being slightly higher in the intervention arm, 37.9% (353/931) compared with the control arm 35.2% (352/999) and among females 37.9% (351/925) compared with males 35.2% (354/1005). Satisfaction was lowest among the married workers, 35.7% (575/1611) compared with the other categories.
Timing and completeness of payments
Nearly, all VCHWs were paid after the campaign, 97.6% (1884/1930), with no significant difference between the intervention (98.1%, 913/931) and the control (97.2%, 971/999) arms
Delayed/non- payment was highest among those with no formal education, 34% (17/50) and among community mobilisers, 30.7% (392/1071). The majority (70.6%, 1362/1930) of the VCHWs stated that the payment received met or even exceeded their payment expectation.
Participants also stated that e-cash was convenient, transparent, time-saving, and cost-saving, as it reduced travel and waiting times and minimized informal deductions.
Despite these benefits and support to districts to operationalize digital payments , there was no significant difference in workers’ motivation or satisfaction between the intervention and control groups. The researchers attributed this partly due to challenges associated with both cash and digital payment modes.
Challenges experienced in effecting payments at the district level
Also a number of challenges were uncovered in this study . Challenges with e-cash payments included unanticipated withdrawal charges, unreliable internet networks, and lengthy processes for validating mobile telephone numbers. For example, payments were delayed or not processed when VCHWs’ names did not match the registration details held by telecommunication companies, or when workers did not have phones registered in their names.
One key informant had this to say on challenges around e-cash payments
‘’ There was a general complaint of charges. Remember when they are dispersing funds, they stick to the budget exactly. They are not looking at the charges. And when you are also paying you have to allocate minus the charges. You get the point. So the people would be expecting let’s take an example of 150 000/= and then they get 149 something. So, they would ask, ‘Why are we getting less money?’ So we labored to explain to them that the bank is charging a certain fee to facilitate the e- cash. (KII_West_EPI FP) There were also challenges associated with an unreliable internet network that was necessary to facilitate log ins for approval of payments
On Challenges experienced in effecting payments at the district level ,Key informant interviews with district leaders involved in the payment process identified several bottlenecks during the payment process of the campaign healthcare workers. One of the major e- cash payment challenges was a lengthy process of validating mobile telephone numbers. ensuring that the VCHW’s names matched the registered mobile account names attached to the telephone number provided by the VCHW for receipt of funds.
‘’Unsuccessful validation occurred when the VCHW’s names did not match the registration details held by the telecommunication companies. Payments for such individuals were delayed or not effected at all. Because some of them do not even have the phones, but they are very good at doing the work…Or if they have, then the phone is not registered in their names. We were supposed to bring that database of the community as well and feed them into the system. That became a problem’’. (KII_North_ADHO)
Suggestions to improve use of e-cash payment system
To increase the use of e- cash, the majority of key informants identified continued training of key staff as a critical intervention with subsequent follow- up to ensure payments are well implemented.
‘’We are not yet ready; our capacity hasn’t been built. We have a big knowledge gap regarding the e- cash system here in this district. (KII East CFO) We request for more training to be conversant [with the system], and to discuss the challenges together during that training, as we share the experiences. Where we have challenges, we sit together and see how they can be addressed’’. (KII_Central_CFO)
The participants also expressed the need for feedback mechanisms to allow them to dialogue with the payers in case there was a delay in payment. Additionally, the participants also acknowledged that there was a need to gradually expand adoption of digital payments considering contextual barriers. A hybrid approach would be an alternative, especially in the remote and hard-to-reach districts.
Other suggested solutions include early preparation of campaign health worker databases to allow for the lengthy telephone validation processes, improvement of the internet infrastructure, consistent use of e- cash payments across programmes and inclusion of withdrawal charges when making payments.
Moving forward policy, the researchers recommend the need to support e- payment systems, in order to minimize challenges in the pay ment processes.
‘’Suggestions to improve the e- cash experience include training of personnel in charge of e- cash payments, timely creation of VCHWs databases, expanding e- cash payments across programmes for efficiency and inclusion of withdrawal charges for the digital payments. To ensure the institutionalisation of digital payment interventions across Uganda, several key enablers are essential. These include formal policy integration by the Ministry of Health and Ministry of Finance into operational guide lines and budget frameworks, as well as ongoing capacity strengthening at the district level to enhance digital planning, payroll management and troubleshooting. Reliable infrastructure such as mobile connectivity and access to digital financial services like mobile money must also be prioritised, especially in rural areas. Implementing routine monitoring and feedback systems will be vital for tracking payment timeliness, worker satisfaction and system performance, allowing for continuous improvement. Furthermore, fostering public–private partner ships with telecom providers and payment platforms is critical for cost- effective scaling. With strong political commitment, aligned funding and active community engagement, this model holds the potential for broader national and regional adoption, leading to more efficient and equitable health service delivery’’. The paper concludes on the way forward
To read the paper; click; https://gh.bmj.com/content/10/Suppl_4/e016666
About The DHPI-R project
The DHPI-R project was commissioned by the Bill and Melinda Gates Foundation (BMGF) to generate evidence on digital payments in Africa. Although inception, conceptualization of the proposal, and grant award were conducted earlier in 2021, the DHPIR project officially started implementing activities in November 2021, up to March 2025. DHPIR is hosted at the School of Public Health, College of Health Sciences at Makerere University and is implemented in Anglophone and Francophone hubs (countries) in Africa. The Anglophone hub is hosted at MAKSPH, while the Francophone Hub is hosted by the University of Dakar (UCAD) in Senegal.
DHP-IR was rooted in the End Polio Game Campaign, championed by WHO-Afro and partners in 28 countries in Sub Saharan Africa, where digital payments was a key strategy for timely and complete payments to campaign workers.
You may like
-
Makerere GENDIG International Conference Calls for Gender-Inclusive Digital Transformation
-
Why RUFORUM’s 22nd AGM in Zambia matters for Africa’s next generation
-
Prof. Christopher Mbazira Professorial Lecture: Examination of Uganda’s Judicial Power and Its Role in Constitutional Transformation
-
Makerere Launches Programme to Strengthen Resilience of Vulnerable Communities to Climate Change
-
Makerere-Rotary Launch Student Food for Peace Initiative
-
The Road from Climate Promises to Care in Uganda
This week, world leaders, negotiators and researchers are gathered in Antalya, Türkiye, for COP31, the United Nations climate conference, seeking to turn years of climate commitments into action countries can finance and implement. Among them is Dr. John Bosco Isunju, a climate and health researcher at Makerere University School of Public Health, named among TIME’s 100 most influential climate leaders in 2024.
Dr. Isunju led the School’s technical support to the Ministry of Health for Uganda’s 2023 Climate Change Health Vulnerability and Adaptation Assessment (VAA) and the subsequent development of the Health National Adaptation Plan (H-NAP) 2025–2030. The assessment covered 716 health facilities across 43 districts, documenting vulnerabilities that helped shape the country’s priorities for protecting healthcare from climate hazards.

That experience speaks directly to the task before the 9–20 November summit. With “Dynamic and Resilient Health Systems” among the COP31 Presidency’s Action Agenda priorities, the conference is seeking practical solutions and financing to keep services functioning through climate shocks. Adaptation, the practical changes needed to cope with a changing climate, must ultimately reach the facilities where people seek care.
Protecting facilities from floods and drought also safeguards the public investment behind them, giving Uganda’s adaptation effort an economic significance alongside its importance to patients. In a 27 October 2026 statement ahead of COP31, UN Climate Change Executive Secretary Simon Stiell placed climate action within that wider calculation of public benefit.
“More governments are taking climate action right across their economies, to bank the vast benefits of clean energy and climate resilience,” he said. “Almost every major economy, and many medium-sized and smaller economies, now see climate action as a central driver of economic growth, jobs, and affordable and secure energy.”

On 21 October, nearly three weeks before the Antalya talks, the H-NAP was before Ugandan parliamentarians in Kampala. Convened by the Ministry of Health and Parliamentary Forum on Climate Change Uganda, with support from Regenerate Africa and the Clinton Health Access Initiative, the engagement examined the plan and Parliament’s role in securing funding, scrutinising implementation and ensuring accountability.
Presenting the VAA, Dr. Isunju explained that the team examined the hazards facing each area, the extent of exposure and the weaknesses that made services vulnerable. They also considered the communities the facilities served. A flood could turn an already difficult journey to treatment into one that patients and staff could no longer make, as seen in many parts of Uganda, including Kasese.
“Either health workers will not work, or communities will not be able to access care, or outreaches will not be possible because roads are cut off,” he told legislators.

Uganda’s H-NAP grew out of commitments made at COP26 in Glasgow in 2021 to assess health vulnerabilities and develop an adaptation response. The Ministry of Health commissioned the School to undertake the VAA in 2023, with Rockefeller Foundation funding supporting both the assessment and the plan’s development. Developed through stakeholder consultation, with WHO technical support and contributions from other partners, the plan was launched on 22 August 2024.
What the assessment found
The VAA found that drought and floods were disrupting the conditions needed to deliver care. Nearly half of the assessed facilities reported drought exposure, while about two in five reported floods. Among the 284 facilities reporting flood exposure, 141 (about half) said health professionals had been unable to arrive at or leave their workplaces, and 198 (about seven in ten) reported shortages of safe water. Because districts were selected for their history of hazards, these findings describe the assessed facilities and cannot be treated as national estimates.
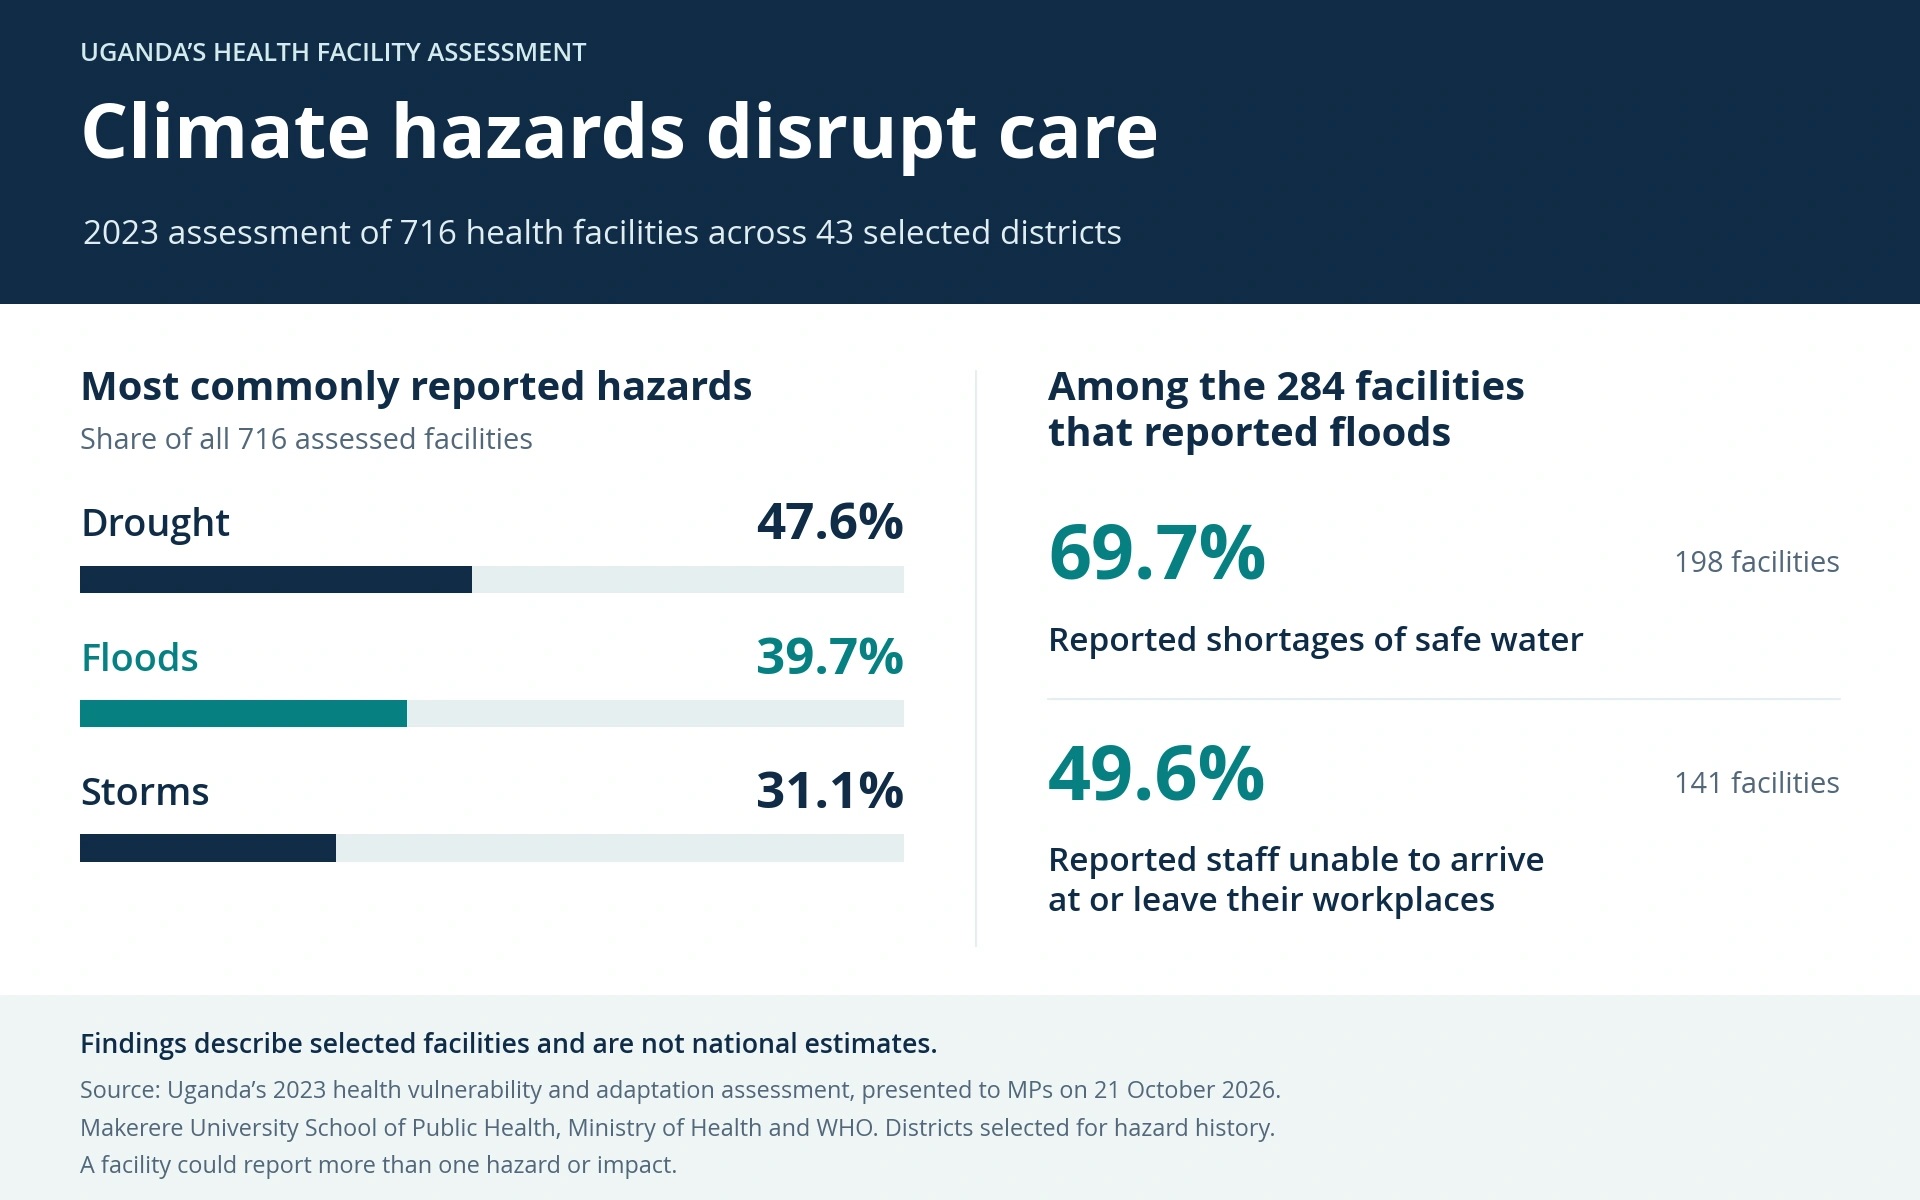
The H-NAP responds across ten components of the health system, including leadership, workforce training, risk monitoring and sustainable financing. Its proposed actions include revising infrastructure standards and using weather and disease information to warn of health risks earlier. Protecting care requires investment in buildings alongside the people and systems that make them function.
“A significant proportion of healthcare facilities lack water management and safety plans to address contamination risks,” the H-NAP states. “They lack water safety plans and contingency plans for monitoring and reducing contaminants as well as on-site water purification equipment.” Such gaps can leave facilities unable to maintain hygiene, clean equipment and provide treatment safely when water supplies fail or become contaminated.
The H-NAP already includes a budget, giving implementation a basis for resource mobilisation. The UN climate secretariat’s 2026 report on national adaptation plans across sectors identifies the difficulty of turning priorities into fundable projects. It recommends costing specific interventions and securing delivery partners, steps that can help advance Uganda’s health adaptation priorities.
At household level, climate pressures on livelihoods can leave families less able to get care or keep children in school, as community consultations showed.
“Their problems are interconnected. If climate, for example, affects their livelihoods, it directly impacts their health, because that means when they fall sick they can’t get care, and they can’t take their children to school, so things are all interconnected,” Dr. Isunju said.

The Ministry’s Focal Point for Climate Change and Health, Dr. Didacus Namanya, told MPs that resilience, the ability to withstand disruption and keep providing care, must inform how services are built and managed.
“So, our vision in the H-NAP is to have a responsive, adaptive, and resilient health system. Adaptive, we are talking about adaptation. These impacts will not stop; they will continue coming, but we must develop our adaptive capacity. The way we build our health facilities, the way we tackle the disease burden, we must be highly adaptive,” he said.
Dr. Namanya called for district-specific assessments, noting the different conditions in Nakasongola and Bududa, and described an ongoing review of infrastructure design standards. Dr. Isunju reported that guidelines for coordinating climate and health action across institutions were undergoing approval.
A partnership announced in October 2025 by the Rockefeller Foundation and the International Development Research Centre is helping the School and the Clinton Health Access Initiative, working with the Ministry of Health, build an investment case for H-NAP implementation. A separate Ministry of Health and Global Green Growth Institute initiative, begun in June 2026, is advancing climate-resilient water, sanitation and hygiene standards, investment plans for health facilities and the government’s capacity to deliver improvements.

Questions for Antalya
Legislators sought evidence of what implementation had delivered. Terego East MP Hon. Wilfred Babanga Erima asked how much of the plan had been implemented, how many facilities had been audited and refitted for climate resilience, and how funding was divided between domestic and donor sources. Hon. Shafiga Wanyenya, Vice Chairperson of Parliament’s Committee on Climate Change, proposed joint follow-up with the health committee and regular progress reviews.
“Our role is to ask the difficult questions and also identify implementation gaps, to advocate for the vulnerable communities and ensure that the national commitments translate into tangible improvements in the lives of our people,” Hon. Wanyenya said.

Those questions belong in Antalya too. The Yearbook of Global Climate Action 2026 identifies gaps in global data for assessing whether health systems are becoming more resilient, underlining the importance of tracking what adaptation efforts deliver for health.
The COP31 health programme links implementation of the Belém Health Action Plan with a financing framework intended to help turn health priorities into investable projects. Launched on 9 November, the Antalya Initiative for Health Resilience provides a platform for countries to share practical experience. The COP28 adaptation framework sets targets for climate-resilient health services by 2030 and progressively beyond, alongside national adaptation planning by 2030 and multi-hazard early-warning systems by 2027.
The H-NAP gives Uganda a practical agenda for that next stage. It calls for climate and health priorities to enter government budgets and for proposals capable of attracting finance. It also identifies academic partnerships as a route to research and capacity-building funds. Annual reviews would then assess progress and guide subsequent work.
As negotiations continue in Antalya, the next test is whether decisions there, and action at home, help keep care available, on the road to a health facility, and at the water point on which safe treatment depends.
Health
Makerere University’s Prof. Peter Waiswa Appointed to WHO Technical Working Group on Essential Child Health Services

Published
1 week agoon
November 11, 2026By
Mak Editor
Makerere University’s Professor Peter Waiswa has been appointed to the World Health Organization (WHO) Technical Working Group of Experts tasked with developing the Essential Child Health Services (ECHS) framework.
The appointment, communicated in an official letter dated October 21, 2026, and signed by Dr. Pascale Allotey, Director of WHO’s Department of Sexual, Reproductive, Maternal, Child, Adolescent and Ageing Health, runs until December 31, 2027.
The technical working group will support WHO in defining a core package of essential health services for newborns, older children and adolescents, alongside practical approaches for delivering these services effectively and equitably to improve their health and well-being.
As a member of the working group, Prof. Waiswa will contribute scientific and technical expertise to the development of the framework. His responsibilities will include participating in technical consultations, reviewing draft documents, providing written feedback and contributing to consensus-building on key technical issues.
The group is expected to hold approximately five online meetings between November 2026 and mid-2027. Members will serve in their individual capacities as independent experts rather than as representatives of their respective governments or institutions.
The appointment builds on Prof. Waiswa’s longstanding service and contributions to WHO. He previously served for seven years on WHO’s Strategic and Technical Advisory Group of Experts (STAGE) on Maternal, Newborn, Child and Adolescent Health and Nutrition, with his tenure concluding in June 2026.
Congratulations Prof. Peter Waiswa.
Health
Mak Staff Receive Prestigious International “Future of the Field” Recognition in Global Research Administration Class of 2026.
Published
1 week agoon
November 9, 2026By
Zaam Ssali
Makerere University proudly celebrates the recognition of Mr. Mordecai Tayebwa, Senior Grants Manager, Makerere University Lung Institute and Ms. Bonny Tusiime, Grants and Contracts Officer, Makerere University College of Health of Sciences (MakCHS) as recipients of the prestigious Future of the Field Award of Society of Research Administrators International (SRAI), an international recognition that Honors emerging leaders making outstanding contributions to the advancement of research administration. This year’s ‘Future of the Field’ honorees were formally recognized at SRAI’s Annual Meeting held in Honolulu, Hawaii, USA in October, 2026.
The Future of the Field Award recognizes professionals who demonstrate exceptional leadership, innovation, and commitment to strengthening research management and administration. The award celebrates individuals whose work is shaping the future of the profession by improving research support systems, fostering collaboration, and advancing excellence in research administration.
At Makerere University, Mr. Tayebwa and Ms. Tusiime have played key roles in strengthening grants and contracts management, supporting researchers throughout the grant lifecycle, promoting compliance with sponsor requirements, and contributing to the development of sustainable research management systems. Their efforts have enhanced institutional capacity to attract, manage, and administer competitive research funding while ensuring accountability and excellence. Commenting on the recognition, the award recipients expressed their gratitude for the opportunity to contribute to the growth of research administration. “This recognition reflects not only our individual efforts but also the collaborative environment at MakCHS and Makerere University. It inspires us to continue strengthening research administration and supporting researchers in generating impactful scientific discoveries that improve lives.” They said.
The achievement highlights the growing international recognition of research administration professionals in Africa and underscores Makerere University and MakCHS’s general commitment to building strong research support systems that enable world-class research. This also reflects the institution’s investment in professional development and its dedication to advancing research excellence through effective grants management.
Commenting on the award, Dara C. Little, President, (SRAI) said “In a field as dynamic and rapidly evolving as research administration, the need for visionary,adaptable leaders have never been greater,” . “SRAI’s Future of the Field recipients represent the next generation of changemakers – those who will not only navigate complexity but shape the future of our profession. To embrace change, is to lead your innovation, resilience, and leadership are exactly what this moment demands. Rise to the opportunity and you will do great things!”
Makerere University congratulates Mr. Mordecai Tayebwa and Ms. Bonny Tusiime on this significant achievement and wishes them continued success as they contribute to shaping the future of research administration both regionally and globally
Trending
-
General1 week agoNOTICE: Online Applications for Government Sponsorship for Programmes Offered at Public Universities & Other Tertiary Institutions 2027/2028 AY
-

General2 weeks agoMakerere Marks 2026 International Day of Persons with Disability – Lord Mayor Balimwezo Delivers Keynote
-

Health2 weeks agoMayuge Study Finds NCD Risks Emerging in Adolescence, and Shows Early Action Can Help
-

Agriculture & Environment1 week agoZambia readies to host the 22nd RUFORUM AGM in the Capital Lusaka
-

General1 week agoMakerere-Rotary Launch Student Food for Peace Initiative








