
Health
Digital Payments Boost Vaccination Campaign Efficiency in Uganda


KAMPALA, Uganda —Supporting districts to adopt digital payments can significantly improve the efficiency of mass vaccination campaigns in Uganda, even if the gains do not directly translate into higher worker motivation, a new study by Makerere University School of Public Health (MakSPH) researchers has found.
Published on September 10, 2025, in BMJ Global Health, the study examined how helping districts in Uganda transition from cash-based to electronic payments affected vaccination campaign workers. Conducted in early 2023, some four months after the nationwide oral poliovirus vaccination campaign of November 2022, the research assessed the impact of digitised payments on efficiency, timeliness, and worker satisfaction.
With generous support from the Bill & Melinda Gates Foundation, the study was led by MakSPH researchers Peter Waiswa, Juliet Aweko, Maggie Ssekitto Ashaba, Elizabeth Ekirapa-Kiracho, and Charles Opio, in collaboration with Margaret McConnell of the Harvard T.H. Chan School of Public Health, Daniel Donald Mukuye from Uganda’s Ministry of Health, and Andrew Bakainaga from the World Health Organisation (WHO)–Uganda Country Office.
The study’s Principal Investigator and lead author, Assoc. Prof. Peter Waiswa, a health systems researcher at Makerere University School of Public Health, said while the research was conducted in Uganda, its implications are global. He pointed out that some African countries, such as Côte d’Ivoire, Zambia, Tanzania, and Kenya, are already ahead in adopting digital payment systems, while others still lag behind. The study’s findings, he said, are relevant across these contexts and have already informed the work of global actors such as Gavi, WHO, and the Global Fund, who are now integrating digital payments into their own processes.
“This paper is part of several studies we are conducting, but perhaps the most significant,” said Dr. Waiswa, clearly enthusiastic about the findings. “Another outlines the research agenda for digital payments, emphasising the need for more evidence on whether they improve the quality of immunisation campaigns, ensure timeliness and efficiency, and identify which groups face barriers to their use.”

The study was coordinated by MakSPH in collaboration with a network of partners. In Uganda, these included the Ministry of Finance, the Ministry of Health, the World Health Organisation, several implementing organisations, district authorities, as well as telecommunication companies. Importantly, the involvement of Airtel as a non-traditional actor in the study demonstrated the critical role of private sector engagement, often absent in such collaborations, in generating evidence and advancing digital health solutions, particularly in addressing challenges such as timely payments for health campaign workers.
The November 2022 polio campaign, led by the government of Uganda with support from the U.S. CDC and WHO, targeted 8.7 million children under five with the novel oral polio vaccine (nOPV2). Nearly 72,000 teams, including health workers, Village Health Teams, and Local Council representatives, were mobilised nationwide, administering about 10 million doses despite the temporary exclusion of five districts due to the Ebola outbreak at the time.
Building on the campaign, the researchers conducted an exploratory cluster-randomised trial using a mixed-methods approach across 54 districts in Uganda, where they enrolled 2,665 healthcare workers. Intervention districts were trained to use Uganda’s e-cash platform, a government innovation managed by the Ministry of Finance. Introduced in 2017 and formalised in 2019, the cashless system was designed to digitise urgent government payments, enhance efficiency, and improve transparency. It now complements the Integrated Financial Management System, which, though effective for routine payments, was seen as too slow for time-sensitive transactions, including paying campaign health workers, where timely remuneration is critical for maintaining workforce readiness, sustaining campaign momentum, and promptly addressing public health challenges in the communities served.
Intervention studies usually introduce a treatment or program to a group to observe its effects, and the results are compared with a group that does not receive it. The training during the study addressed the delays, leakages, and administrative bottlenecks common in cash-based systems. Intervention districts received instruction on navigating the government e-cash platform, managing user roles, uploading beneficiary data, and generating payment reports, while control districts maintained standard cash payment procedures, serving as a baseline.
Dr. Juliet Aweko, co-author and Research Associate at MakSPH, said the study was timely, observing that health workers are central to successful vaccination campaigns and delayed payments can demotivate them and compromise campaign effectiveness.
“To make digital payments truly work, campaigns must be planned with the workforce in mind. Government and partners need to ensure funds are disbursed on time, streamline and automate registration and verification, and keep accurate records of health workers and their performance. Making mobile money systems compatible and giving workers real-time updates on their payments would not only build trust but also keep them motivated, ultimately improving turnout and ensuring smoother service delivery,” Dr. Aweko stated.

The study found that electronic cash adoption was significantly higher in intervention districts, where 57.5% of workers were paid digitally compared to 44.1% in control districts. What’s more, digital payments did not delay disbursement, as 97.6% of all workers received payment after campaign completion, regardless of method. Still, workers paid via e-cash consistently described the cashless system as convenient, transparent, and cost-effective, citing reduced travel time, lower personal costs, and fewer security risks.
Today, Uganda’s rapidly expanding digital ecosystem provides ground for scaling up cashless payment systems. The Uganda Communications Commission reports that the country has over 43 million active mobile subscriptions, nearly 88% of the estimated 49 million population. Its latest market report shows 26.1 million active internet users, while mobile money continues to dominate financial transactions with more than 33 million accounts and transaction values growing by over 25% annually, according to reports by the Bank of Uganda as of March 2025. This trend reflects a population increasingly reliant on digital platforms, creating a strong opportunity to embed e-payment systems in health service delivery.

For MakSPH researchers Dr. Waiswa and Dr. Aweko, the study evidence confirms that digital payments are both feasible and practical for strengthening the delivery of mass campaigns in low- and middle-income countries like Uganda. With relatively modest support, districts can adopt e-cash systems, providing a scalable model for the health sector. This approach, they suggest, would streamline compensation, reduce administrative delays, and provide a stronger basis for integrating digital payments into future immunisation drives and other public health interventions in the country, thereby strengthening our health systems.
The researchers further emphasised that digitising campaign payments reduces transaction costs and minimises leakages, enabling more funds to reach frontline workers quickly. E-cash also simplifies logistics, strengthens accountability, and enhances financial tracking in health campaigns. These advantages, they found, directly align with the global effort to advance digital transformation in health systems and ensure reliable, transparent worker compensation. The implications also extend beyond just polio, as Uganda continues to rely on mass campaigns for routine immunisation and other outbreak responses, such as measles and yellow fever, where digital payments could improve the efficiency of scarce health resources.
Still, the study acknowledged barriers that could hinder full adoption of a cashless system. Some districts lacked the technical capacity to operate the government’s e-cash platform, upload beneficiary data, and manage user roles. Connectivity issues, limited digital literacy among staff, and occasional system downtimes further disrupted implementation. Additionally, many campaign workers lacked national identity cards or mobile money accounts, making them ineligible for digital payments. To address these challenges, the researchers, among others, recommend targeted capacity building for district finance and health teams, expanded identity and mobile registration for campaign workers, improved internet connectivity, and integration of e-payment systems into routine health planning.












This week, world leaders, negotiators and researchers are gathered in Antalya, Türkiye, for COP31, the United Nations climate conference, seeking to turn years of climate commitments into action countries can finance and implement. Among them is Dr. John Bosco Isunju, a climate and health researcher at Makerere University School of Public Health, named among TIME’s 100 most influential climate leaders in 2024.
Dr. Isunju led the School’s technical support to the Ministry of Health for Uganda’s 2023 Climate Change Health Vulnerability and Adaptation Assessment (VAA) and the subsequent development of the Health National Adaptation Plan (H-NAP) 2025–2030. The assessment covered 716 health facilities across 43 districts, documenting vulnerabilities that helped shape the country’s priorities for protecting healthcare from climate hazards.

That experience speaks directly to the task before the 9–20 November summit. With “Dynamic and Resilient Health Systems” among the COP31 Presidency’s Action Agenda priorities, the conference is seeking practical solutions and financing to keep services functioning through climate shocks. Adaptation, the practical changes needed to cope with a changing climate, must ultimately reach the facilities where people seek care.
Protecting facilities from floods and drought also safeguards the public investment behind them, giving Uganda’s adaptation effort an economic significance alongside its importance to patients. In a 27 October 2026 statement ahead of COP31, UN Climate Change Executive Secretary Simon Stiell placed climate action within that wider calculation of public benefit.
“More governments are taking climate action right across their economies, to bank the vast benefits of clean energy and climate resilience,” he said. “Almost every major economy, and many medium-sized and smaller economies, now see climate action as a central driver of economic growth, jobs, and affordable and secure energy.”

On 21 October, nearly three weeks before the Antalya talks, the H-NAP was before Ugandan parliamentarians in Kampala. Convened by the Ministry of Health and Parliamentary Forum on Climate Change Uganda, with support from Regenerate Africa and the Clinton Health Access Initiative, the engagement examined the plan and Parliament’s role in securing funding, scrutinising implementation and ensuring accountability.
Presenting the VAA, Dr. Isunju explained that the team examined the hazards facing each area, the extent of exposure and the weaknesses that made services vulnerable. They also considered the communities the facilities served. A flood could turn an already difficult journey to treatment into one that patients and staff could no longer make, as seen in many parts of Uganda, including Kasese.
“Either health workers will not work, or communities will not be able to access care, or outreaches will not be possible because roads are cut off,” he told legislators.

Uganda’s H-NAP grew out of commitments made at COP26 in Glasgow in 2021 to assess health vulnerabilities and develop an adaptation response. The Ministry of Health commissioned the School to undertake the VAA in 2023, with Rockefeller Foundation funding supporting both the assessment and the plan’s development. Developed through stakeholder consultation, with WHO technical support and contributions from other partners, the plan was launched on 22 August 2024.
What the assessment found
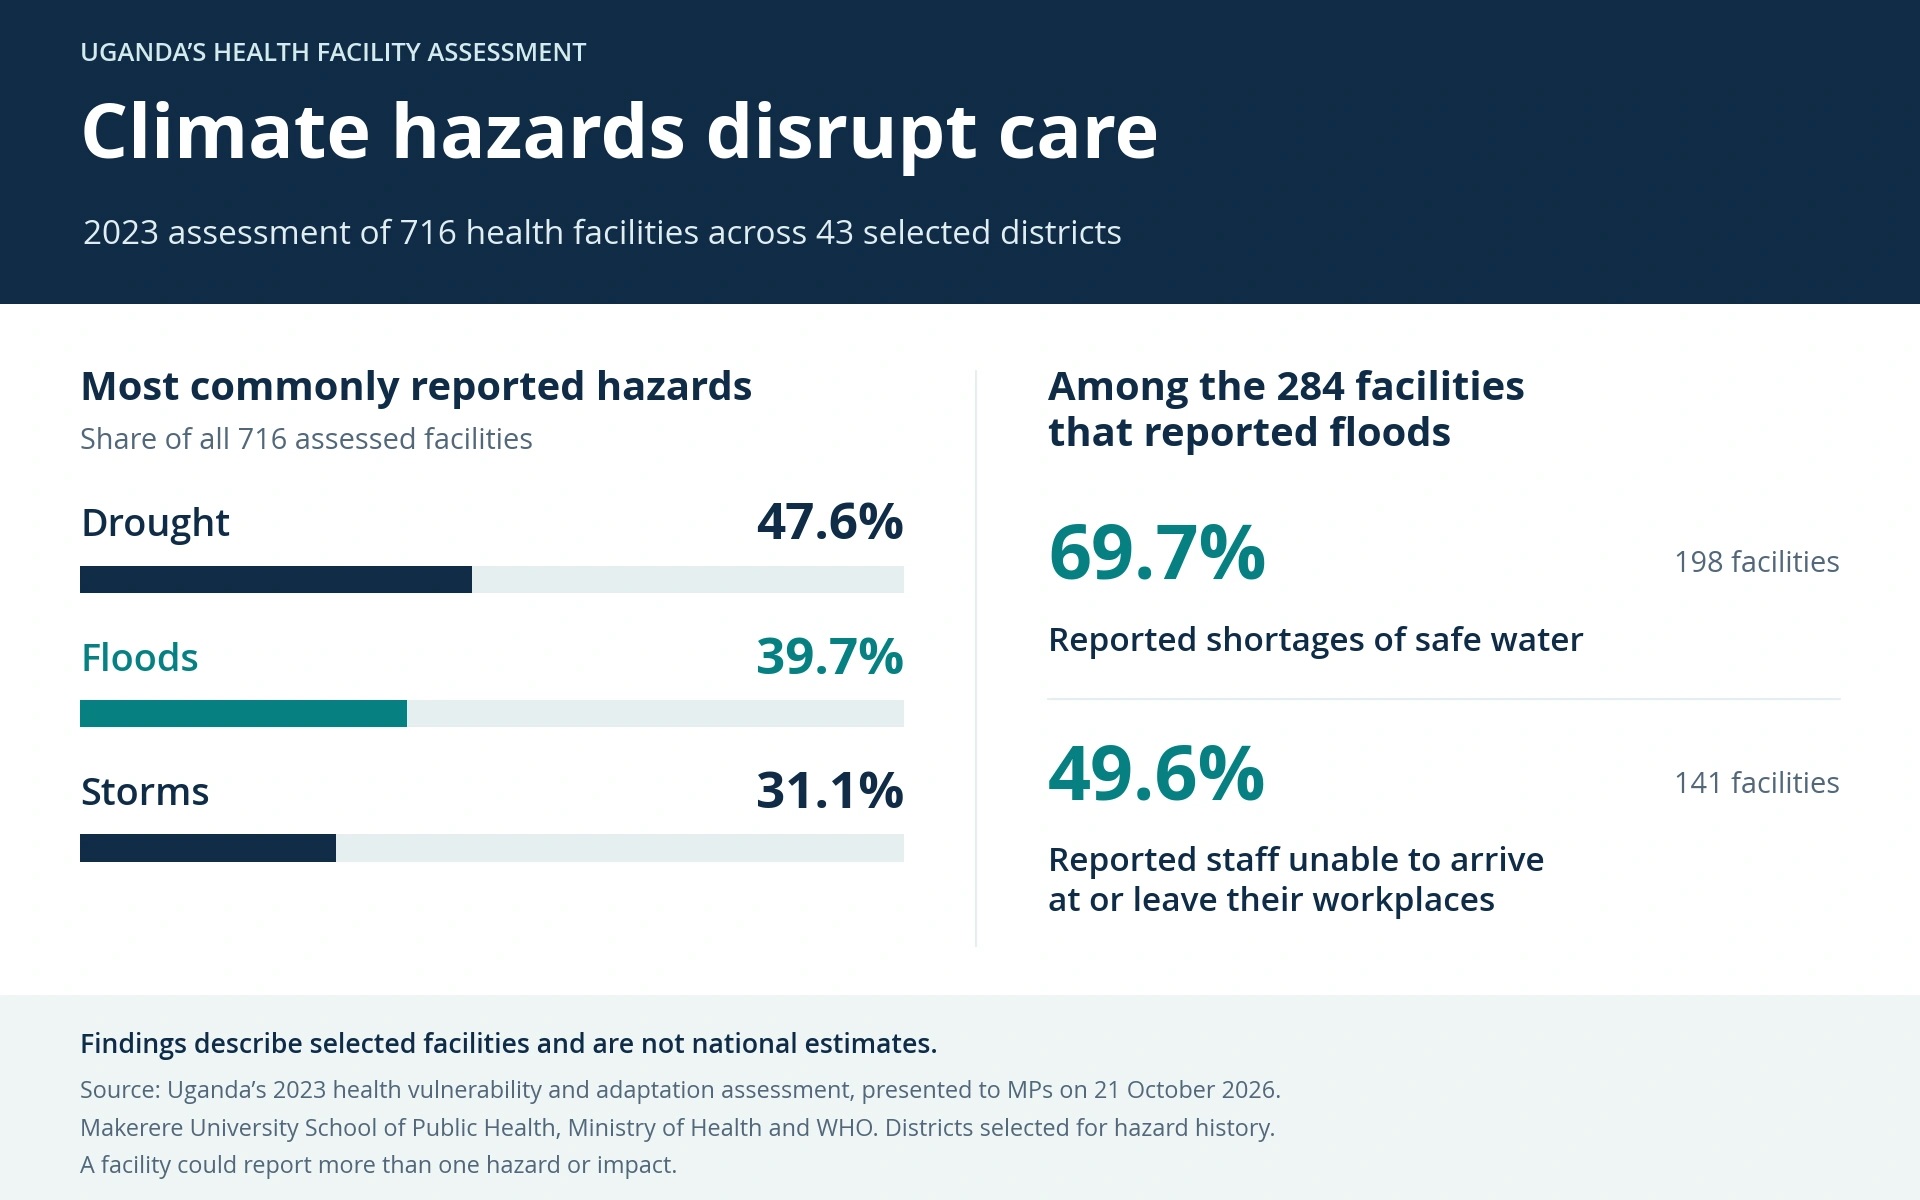
The VAA found that drought and floods were disrupting the conditions needed to deliver care. Nearly half of the assessed facilities reported drought exposure, while about two in five reported floods. Among the 284 facilities reporting flood exposure, 141 (about half) said health professionals had been unable to arrive at or leave their workplaces, and 198 (about seven in ten) reported shortages of safe water. Because districts were selected for their history of hazards, these findings describe the assessed facilities and cannot be treated as national estimates.
The H-NAP responds across ten components of the health system, including leadership, workforce training, risk monitoring and sustainable financing. Its proposed actions include revising infrastructure standards and using weather and disease information to warn of health risks earlier. Protecting care requires investment in buildings alongside the people and systems that make them function.
“A significant proportion of healthcare facilities lack water management and safety plans to address contamination risks,” the H-NAP states. “They lack water safety plans and contingency plans for monitoring and reducing contaminants as well as on-site water purification equipment.” Such gaps can leave facilities unable to maintain hygiene, clean equipment and provide treatment safely when water supplies fail or become contaminated.
The H-NAP already includes a budget, giving implementation a basis for resource mobilisation. The UN climate secretariat’s 2026 report on national adaptation plans across sectors identifies the difficulty of turning priorities into fundable projects. It recommends costing specific interventions and securing delivery partners, steps that can help advance Uganda’s health adaptation priorities.
At household level, climate pressures on livelihoods can leave families less able to get care or keep children in school, as community consultations showed.
“Their problems are interconnected. If climate, for example, affects their livelihoods, it directly impacts their health, because that means when they fall sick they can’t get care, and they can’t take their children to school, so things are all interconnected,” Dr. Isunju said.

The Ministry’s Focal Point for Climate Change and Health, Dr. Didacus Namanya, told MPs that resilience, the ability to withstand disruption and keep providing care, must inform how services are built and managed.
“So, our vision in the H-NAP is to have a responsive, adaptive, and resilient health system. Adaptive, we are talking about adaptation. These impacts will not stop; they will continue coming, but we must develop our adaptive capacity. The way we build our health facilities, the way we tackle the disease burden, we must be highly adaptive,” he said.
Dr. Namanya called for district-specific assessments, noting the different conditions in Nakasongola and Bududa, and described an ongoing review of infrastructure design standards. Dr. Isunju reported that guidelines for coordinating climate and health action across institutions were undergoing approval.
A partnership announced in October 2025 by the Rockefeller Foundation and the International Development Research Centre is helping the School and the Clinton Health Access Initiative, working with the Ministry of Health, build an investment case for H-NAP implementation. A separate Ministry of Health and Global Green Growth Institute initiative, begun in June 2026, is advancing climate-resilient water, sanitation and hygiene standards, investment plans for health facilities and the government’s capacity to deliver improvements.

Questions for Antalya
Legislators sought evidence of what implementation had delivered. Terego East MP Hon. Wilfred Babanga Erima asked how much of the plan had been implemented, how many facilities had been audited and refitted for climate resilience, and how funding was divided between domestic and donor sources. Hon. Shafiga Wanyenya, Vice Chairperson of Parliament’s Committee on Climate Change, proposed joint follow-up with the health committee and regular progress reviews.
“Our role is to ask the difficult questions and also identify implementation gaps, to advocate for the vulnerable communities and ensure that the national commitments translate into tangible improvements in the lives of our people,” Hon. Wanyenya said.

Those questions belong in Antalya too. The Yearbook of Global Climate Action 2026 identifies gaps in global data for assessing whether health systems are becoming more resilient, underlining the importance of tracking what adaptation efforts deliver for health.
The COP31 health programme links implementation of the Belém Health Action Plan with a financing framework intended to help turn health priorities into investable projects. Launched on 9 November, the Antalya Initiative for Health Resilience provides a platform for countries to share practical experience. The COP28 adaptation framework sets targets for climate-resilient health services by 2030 and progressively beyond, alongside national adaptation planning by 2030 and multi-hazard early-warning systems by 2027.
The H-NAP gives Uganda a practical agenda for that next stage. It calls for climate and health priorities to enter government budgets and for proposals capable of attracting finance. It also identifies academic partnerships as a route to research and capacity-building funds. Annual reviews would then assess progress and guide subsequent work.
As negotiations continue in Antalya, the next test is whether decisions there, and action at home, help keep care available, on the road to a health facility, and at the water point on which safe treatment depends.
Health
Makerere University’s Prof. Peter Waiswa Appointed to WHO Technical Working Group on Essential Child Health Services


Health
Mak Staff Receive Prestigious International “Future of the Field” Recognition in Global Research Administration Class of 2026.


-

 General4 days ago
NOTICE: Online Applications for Government Sponsorship for Programmes Offered at Public Universities & Other Tertiary Institutions 2027/2028 AY
-

 General2 weeks ago
Update On Payment of Endowment Fund Fees
-

 General2 weeks ago
Institutionalizing ORCID at Makerere University: Strengthening Researcher Identification, Visibility and Research Output Tracking
-

 General1 week ago
Makerere Marks 2026 International Day of Persons with Disability – Lord Mayor Balimwezo Delivers Keynote
-

 Health1 week ago
Mayuge Study Finds NCD Risks Emerging in Adolescence, and Shows Early Action Can Help