
Health
Olivia Nakisita and the Quiet Urgency of Adolescent Refugee Health


Kampala wakes early, but for some girls, the day begins already heavy. In Uganda, nearly three-quarters of the population is under 30, growing up happens fast, and often without protection. One in four Ugandan girls aged 15–19 has already begun childbearing, giving Uganda the highest teenage pregnancy rate in East Africa.
Layered onto this is displacement. The country hosts about 1.7 million refugees, many living in cities like Kampala, where survival depends on navigating systems not designed with them in mind. Also, nationally, 1.4 million people live with HIV, and 70 per cent of new infections among young people occur in adolescent girls, a reminder that vulnerability is rarely singular. When COVID-19 shut the country down, the consequences were immediate, with pregnancies among girls aged 15–19 rising by 25.5 per cent, while pregnancies among girls aged 10–14 surged by 366 per cent.
The numbers tell a story of youth, risk, and quiet urgency. But they do not tell it all. For years, Olivia Nakisita, a public health researcher,has followed how adolescent girls, many of them refugees, navigate pregnancy in Kampala: how far they must travel for care, how early they arrive or delay, and how often services that exist fail to meet them where they are. Her work lives at the uneasy intersection of policy and lived reality, where access does not always translate into care.
February 25th 2026, is the day that her work on whether urban health systems are truly ready for the youngest mothers they now serve will bring her to Freedom Square at Makerere University, where she will graduate with a PhD in Public Health.

Her doctoral journey, focused on maternal health services for adolescent refugees in urban Uganda, has unfolded at the intersection of scholarship, community service, and the daily realities of young girls navigating pregnancy far from home.
The Work That Came Before the Question
Long before she began writing a PhD proposal, Olivia Nakisita was already immersed in adolescent health. As a Research Associate in the Department of Community Health and Behavioral Sciences at Makerere University’s School of Public Health, she taught graduate and undergraduate students, supervised Master’s research, and worked closely with communities. Beyond the university, she led New Life Adolescent and Youth Organization (NAYO), a women-led organisation she founded in 2021 to strengthen access to sexual and reproductive health and rights (SRHR) information and services for adolescents and young people.
It was through this community work that a troubling pattern began to surface.
“During our community service,” she explains, “we noted increasing teenage pregnancies, and we also noted challenges with access to maternal health services by teenage pregnant girls.”

Among those girls were adolescents living as urban refugees in Kampala, young, displaced, often poor, and navigating pregnancy in a city not designed with them in mind.
For Nakisita, the concern deepened through her academic training in Public Health Disaster Management, one such programme that prepares multidisciplinary professionals with the technical expertise and leadership competencies required to plan for, mitigate, respond to, and recover from complex disasters through a public health lens. This programme sharpened Nakisita’s interest in how displaced populations survive within complex urban systems. Uganda’s integrated health model, where refugees and host communities are expected to use the same facilities, appears equitable on paper. In practice, it can be unforgiving.
“I got interested in understanding how these refugees who get pregnant manage to navigate the complexities of integration in host societies like Kampala,” she says. “This was driven by the desire to address their needs and to inform and evaluate existing refugee health policies.”

That desire became the foundation of her PhD.
Asking Hard Questions in a Crowded City
Her doctoral research, “Maternal Health Services for Adolescent Refugees in Urban Settings in Uganda: Access, Utilisation, and Health Facility Readiness,” was conducted in Kampala between November 2023 and August 2024. It combined quantitative surveys with qualitative interviews, engaging 637 adolescent refugees aged 10–19 years, alongside health workers and facility assessments.
Her findings showed high perceived access to maternal health services. Clinics existed. Services were available. Yet utilisation, particularly of antenatal care (ANC), lagged. “About three-quarters of the girls attended at least one antenatal visit,” she explains, “but only about four in ten attended in the first trimester.”
And that gap matters. Public health research shows that early and regular antenatal care allows health workers to detect high-risk pregnancies, initiate supplements such as iron and folic acid, monitor fetal development, and provide psychosocial support. Without it, risks compound silently.
By contrast, her study found that facility-based deliveries were remarkably high, with nearly all adolescent refugees (98.3%) giving birth in health facilities, suggesting that the system was reachable, but uneven.

Where the System Falls Short
Her research went beyond utilisation to examine whether health facilities were actually ready to serve adolescent refugees.
Findings show that lower-level health centres in Kampala were moderately prepared to offer adolescent-friendly maternal health services. Some staff were trained. Some spaces existed. Despite this, critical gaps remained. For instance, facilities lacked essential equipment and supplies. Non-provider staff were often untrained. Separate, private spaces for adolescents were limited. Language barriers complicated care. Overcrowding strained already stretched health workers.
In her qualitative interviews, health workers expressed empathy and willingness to help. Many relied on peer educators and community health workers to reach adolescent refugees. But good intentions were not enough.
“They recommended training of healthcare workers, translators for refugees, and improvement in the availability of essential drugs, supplies, and equipment,” Nakisita notes.
She notes that readiness is not just about infrastructure but about the people, preparation, and priorities.
Research with an Emotional Cost
For Nakisita, working with adolescent refugees required care, not only methodologically, but emotionally.
Finding participants in Kampala was itself a challenge. Unlike settlement settings, urban refugees are dispersed, often invisible. Ethical considerations were constant. Adolescents who had given birth were legally considered emancipated minors, but their vulnerability remained.
Though the thesis focused on systems rather than personal narratives, Nakisita’s earlier work with adolescents informed every decision she made. It shaped how she framed questions, interpreted data, and weighed policy implications. This was not detached research, but careful, deliberate, and grounded.
The Scholar Formed by Continuity
Nakisita’s PhD sits atop more than 18 years of experience in training, research, and community service. She is an alumna of Makerere College School (UCE), 1996 and Greenhill Academy Secondary School (UACE), 1998, a long journey through Uganda’s education system before her Diploma in Project Planning and Management at Makerere University completed in early 2000s.
She would later return eight years later to Makerere University for her Bachelor’s degree in Social Sciences and a Master’s in Public Health Disaster Management, and now a PhD in Public Health.
Her academic rigor is reflected in extensive training across SRHR, impact evaluation, research methods, ethics, disaster resilience, and humanitarian health. She has presented at regional and international conferences and published in peer-reviewed journals on adolescent health, refugee maternal care, gender-based violence, and health systems readiness.
As a PhD student, she supervised three Master’s students to completion, with another currently progressing, quietly extending her influence through mentorship.

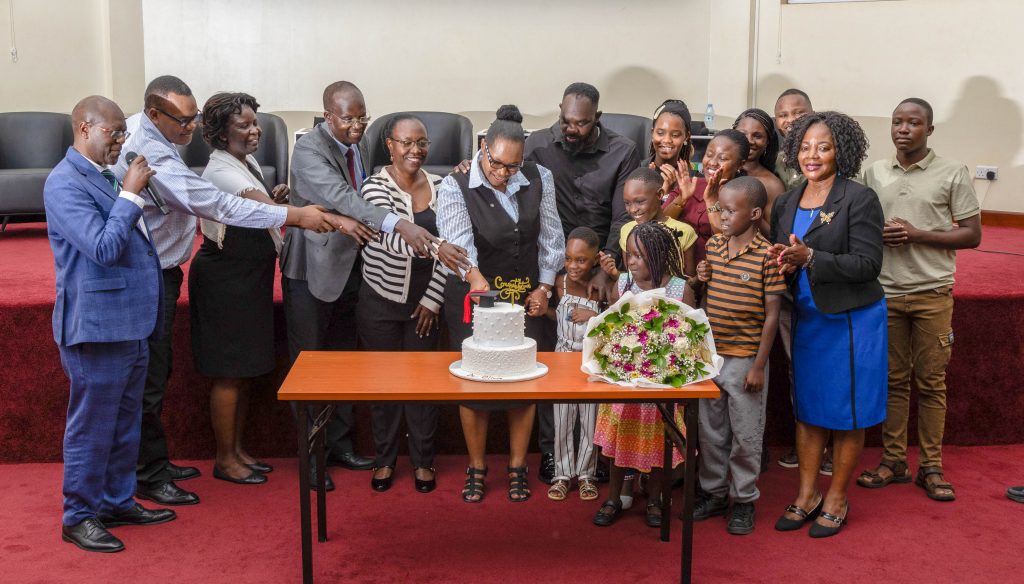


When Evidence Demands Action
If policymakers were to act on one lesson from her research, Nakisita says; “Emphasis should be given to maternal health services for adolescents.” “They are high-risk mothers,” she adds.
Her findings call for targeted community-based interventions, outreaches, home visits, and financial support for adolescents who cannot afford prescribed drugs, delivery requirements, or critical tests like ultrasound scans.
They also call for health systems to move beyond one-size-fits-all models, recognising that age, displacement, and poverty intersect to shape how care is accessed and experienced.
Now that her PhD is complete, Nakisita plans to translate research into action. Several papers from her study have already been published. A policy brief is planned to influence decision-making in urban and humanitarian health settings.
When asked what she would say directly to adolescent refugee girls navigating pregnancy in unfamiliar cities, her response is simple and direct.
“If it happens,” she says, “as soon as you find out, go to the nearest health facility and seek care. Always return for the visits as asked by the health worker. Ensure that you deliver in a health facility with a skilled health worker.”
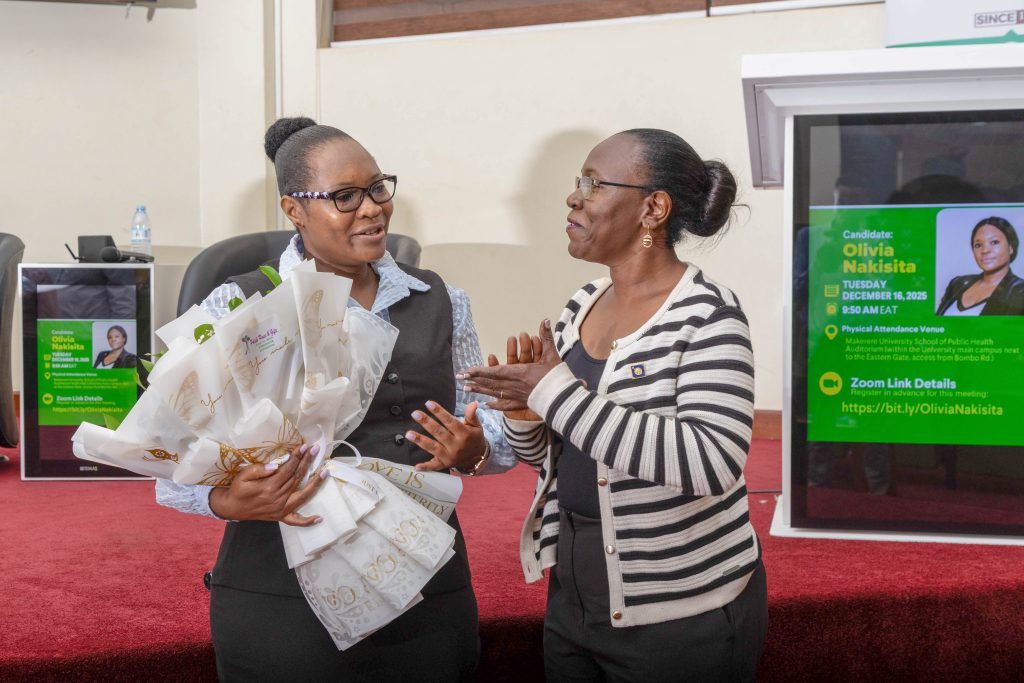
Arrival, Without Illusion
When Dr. Olivia Nakisita steps onto the graduation stage at Freedom Square, applause will follow. But the true significance of that moment lies in health facilities still struggling to adapt; in adolescent refugees whose pregnancies unfold quietly in rented rooms and crowded neighborhoods; in policies waiting to be sharpened by evidence.
Her scholarship does not promise quick fixes but offers clarity.
Among the PhDs conferred at Makerere University’s 76th graduation, her work reminds us that some research does not begin in libraries and does not end with theses. It lives on in the slow, necessary work of making health systems see those they have long overlooked.
— Makerere University School of Public Health Communications Office, Graduation Profiles Series, 76th Graduation Ceremony















Uganda has strengthened its ability to respond rapidly to Ebola and Marburg outbreaks once cases are confirmed, but delays in frontline detection, health worker exposure, emergency financing bottlenecks and incomplete implementation of lessons from previous outbreaks continue to undermine preparedness, a study has found.
The findings were presented today, October 6, 2026, during a country validation workshop convened by the Meeting Targets and Maintaining Epidemic Control (EPiC) project, to examine lessons from Uganda’s response to filovirus disease outbreaks. The study was undertaken by Makerere University School of Public Health and FHI 360.
Presented by Dr. Steven Kabwama, the synthesis examined Uganda’s experience with recurrent Ebola virus disease (EVD) and Marburg virus disease (MVD) outbreaks between 2000 and 2026, drawing particularly on After-Action Reviews from the 2017 Marburg outbreak and the 2019, 2022 and 2025 Ebola outbreaks. The work seeks to consolidate recurring strengths, weaknesses, innovations and lessons that had previously been documented separately.

Uganda has recorded 12 filovirus outbreaks over the 26-year period, including nine Ebola and three Marburg outbreaks, according to the research team. Among the four outbreaks examined closely were the 2017 Marburg outbreak in Kween and Kapchorwa, the cross-border Ebola outbreak in Kasese in 2019, the multi-district Sudan Ebola virus outbreak in 2022, and the 2025 outbreak whose index case was a health worker.
Strong systems after confirmation
Across the outbreaks reviewed, the synthesis found that Uganda has developed significant capacity to mobilise after laboratory confirmation. National and district task forces and technical response structures are activated quickly, supported by strong laboratory capacity, established coordination mechanisms and increasingly sophisticated surveillance systems.
The country has also built laboratory capacity around the Uganda Virus Research Institute, mobile laboratories, genomic sequencing, sample referral systems and the Results Dispatch System. Digital surveillance tools, Village Health Teams, survivor champions and established national and district coordination structures have further strengthened response capacity.
Detection remains a weak point
However, the findings point to a critical problem before confirmation: recognising a possible outbreak early enough.
For outbreaks originating within Uganda, the synthesis found that the period between a patient’s first presentation and confirmation ranged from nine to 27 days. This the study found is linked to low clinical suspicion and weaknesses in screening. Other recurring challenges included delayed access to emergency financing, infections among health workers, disruptions to essential health services, community mistrust and stigma, and limited follow-through on recommendations from previous After-Action Reviews.
Opening the workshop, the Dean, Prof. Rhoda Wanyenze, said understanding these delays requires going beyond identifying broad weaknesses to examining where response systems fail in practice.
“We can identify a broad challenge such as delayed detection from the literature, but your experience on the ground can help us understand the specific factors that create that challenge,” Prof. Wanyenze said while addressing district health officials from across the country.

“When we begin looking for solutions, we need to be able to target the actual problems rather than simply identifying broad challenges.”
The workshop brought together partners and colleagues from districts, including people directly involved in outbreak response, to validate the synthesis against frontline experience. Prof. Wanyenze noted that published literature, scientific papers and response reports cannot capture every operational reality, making practitioner experience essential to understanding where delays occur and what interventions have worked. Remarks validation workshop
Turning outbreak experience into continuous readiness
Among the priority actions proposed are stronger screening and alert systems for earlier detection; ring-fenced emergency financing and more reliable responder payment systems; routine infection prevention and control training; stronger occupational protection for health workers; continued investment in laboratories and genomic sequencing; and preparedness extending beyond districts traditionally considered outbreak hotspots. The study also recommends stronger community engagement and a formal mechanism to track and finance implementation of recommendations from After-Action Reviews.

Dr. Andrew Acero, Director of the EPiC project at FHI 360’s Uganda Office said the central challenge is ensuring that experience accumulated during successive outbreaks translates into lasting institutional capacity.
“The real value lies in ensuring that what we learn changes what we do. Our findings should inform policy, shape guidelines and training, strengthen systems and ultimately improve practice.”
He noted that preparedness cannot begin only after an emergency has been declared, but must be built through sustained relationships, systems and capacity before outbreaks occur. Remarks validation workshop
The EPiC project is led by FHI 360 with core partners including Right to Care, Palladium and Population Services International.


Uganda’s latest national HIV survey reveals lower viral suppression among adolescents and young adults living with HIV than among older adults, even as the country records substantial improvements in controlling the virus. The findings come from Uganda Population-Based HIV Impact Assessment (UPHIA 2025), a national household survey examining HIV prevalence and whether people living with the virus know their status, receive treatment, and achieve viral suppression.
Releasing the preliminary UPHIA 2025 findings at the Uganda Media Centre on 1 October 2026, Minister of Health Hon. Dr. Chris Baryomunsi called for earlier prevention and testing, particularly among adolescent girls and young women, alongside support for treatment adherence. “We must reach out to the young people, ensure that they have information, they test, take treatment, and adhere to the treatment guidance,” he urged.
Hon. Baryomunsi recalled how fear had discouraged testing during his university years: “I remember when we were at university, we went for testing at the university hospital. We sat there for three hours. Some of us left without even testing because it was scary.” Today, he explained, “even if you test HIV positive, you can be initiated on treatment, and you live normally like the rest of those who don’t have HIV.”

UPHIA 2025 was locally led under the Ministry of Health’s overall leadership, with Makerere University School of Public Health serving as the prime implementer, a role ICAP at Columbia University held in the previous two surveys. The Uganda Bureau of Statistics led sampling, while the Uganda Virus Research Institute and National Health Laboratory and Diagnostic Services led laboratory operations. Regional referral hospitals and local governments supported implementation, and the U.S. government provided US$10 million through PEPFAR, along with technical assistance from the U.S. CDC.
UPHIA collected data from July to September 2025 among people aged 15 and above, including those outside routine treatment services. Of 6,283 eligible households, 94.4% completed interviews. Researchers interviewed 13,801 people and tested 13,477 for HIV.
Testing followed Uganda’s national algorithm, with laboratory confirmation of positive samples, viral-load measurement, and checks for antiretroviral medicines to establish treatment use. Researchers weighted the estimates to account for the sampling design. Participants received counselling and results, and those who tested positive were referred for treatment.
Hon. Baryomunsi thanked participants and their families for welcoming survey staff and contributing their time, information and samples, without which the national evidence would not have been available.

National progress and the youth gap
The survey estimated HIV prevalence, which means the proportion of people living with HIV, at 5.9% among those aged 15 and above, corresponding to about 1.496 million people in this age group nationwide. Prevalence was 7.3% among women and 4.1% among men, ranging from 1.3% in Karamoja to 8% in the South Western region.
Among people aged 15 and above living with HIV, 86% had achieved viral suppression, meaning a low amount of HIV in the blood, measured in UPHIA as fewer than 1,000 copies per millilitre. Suppression stood at 69.3% among adolescents and young adults aged 15–24 living with HIV, compared with 89.9% among those aged 50 and above. These estimates cover people living with HIV regardless of whether they know their status or receive treatment.

HIV prevalence among people aged 15–24 was 1.5%, including 2% among young women and 1% among young men. Among young women, prevalence was 1.3% at ages 15–19 and 2.8% at ages 20–24. These differences support attention to earlier prevention and testing, although they do not establish when infections occurred.
The highest prevalence estimates occurred among middle-aged adults: 15.7% among women aged 40–44 and 11.7% among men aged 45–49. Lower suppression among young people therefore requires attention alongside the higher HIV prevalence among middle-aged adults. Comparing the same age group across both surveys, viral suppression among people aged 15–64 increased from 74.9% in 2020–21 to 86.1% in 2025, while HIV prevalence remained at 5.9%.

Diagnosis and the path to 2030
The treatment results identify diagnosis as the main national gap. Among people aged 15 and above living with HIV, 85.3% knew their status. Of those aware, 99.1% were receiving treatment; among those receiving treatment, 96.5% had achieved suppression.
The 95-95-95 targets aimed for 95% of people living with HIV to know their status, 95% of those diagnosed to receive treatment, and 95% of those receiving treatment to achieve viral suppression by 2025. Among people aged 15 and above, Uganda exceeded the treatment and suppression targets, while diagnosis remained below target. UNAIDS’s Global AIDS Strategy 2026–2031 retains these targets towards ending AIDS as a public health threat by 2030.
According to WHO, viral suppression protects health and helps prevent HIV transmission. Uncontrolled HIV weakens the immune system, increasing the risk of serious illness. With continued treatment as prescribed, sexual transmission risk is negligible when HIV remains suppressed but detectable, and zero when undetectable. The Uganda AIDS Commission estimated over 34,000 new HIV infections in 2025, underscoring the importance of early diagnosis, timely treatment, and sustained suppression alongside other prevention measures.

The demographic stakes are substantial. People aged 15–24 constituted 21.2% of Uganda’s population in the 2024 census. The country’s Fourth National Development Plan, covering 2025–2030, prioritises a healthy, knowledgeable, skilled and productive population and reducing HIV through primary health care. Protecting young people’s health, therefore, supports their participation in education, work, and national development; UPHIA helps identify where services need greater attention.
Turning evidence into action
The study’s conclusions identify three priorities: sustain treatment outcomes, find people unaware of their status, and improve suppression among younger people. Permanent Secretary Dr. Diana Atwine connected the findings to the Ministry’s planning.
“We do believe that these results are a true reflection of what is happening in our country as far as the HIV status is concerned, and we do believe that it will give us a very clear direction and the roadmap that we are going to take in the next five years to target and to get our targets achieved.”

Acting on these priorities requires funding for services and research. Hon. Baryomunsi outlined plans to target resources where needs are greatest, strengthen district services and align partner support with government priorities. Responding to journalists’ questions, he noted the government’s intention to increase domestic funding for the HIV response, including research.
“The HIV/AIDS response, including research and surveys such as this one, has largely been funded by partners in the past. The government of Uganda is committed to allocating more resources from our domestic budget to support the response and research,” he noted.
For the first time in the UPHIA series, the survey assessed selected noncommunicable disease indicators among people aged 15 and above: 15.5% had elevated blood pressure, 24.8% were overweight or obese, and 0.9% had raised random blood glucose. These screening findings align with the Ministry’s integration agenda and Hon. Baryomunsi’s call to bring HIV and chronic care services together to address people’s wider health needs.
Speaking at the release of the preliminary results, U.S. Embassy Chargé d’Affaires Mikael (Mika) Cleverley described UPHIA 2025 as the first Population-Based HIV Impact Assessment worldwide fully led and implemented by the country itself.

“The study was led by Ugandan scientists, Ugandan managers, Ugandan public servants, Ugandan field teams, from design to data collection to analysis. And this is what two decades of focused strategic U.S. foreign investments in the public health sector was meant to produce, is to reinforce Ugandan leadership and Ugandan-led efforts.”
At the survey launch on 29 May 2025, MakSPH Dean Prof. Rhoda Wanyenze highlighted the partnership’s contribution: “The partnership between Makerere University and CDC has not only helped build national capacity in surveillance and epidemiology, but has also strengthened our ability to lead high-quality, large-scale national surveys.”

The Dean added: “After two decades of joint work, we are proud that UPHIA is now a fully Ugandan-led effort. This is critical to the sustainability of the skills and knowledge generation to inform our local response.”
UPHIA 2025 shows how far Uganda’s HIV response has advanced and where gaps remain. As the country works towards ending AIDS as a public health threat by 2030, reaching young people with testing, treatment, and continued care will be essential to extending those gains.

Read the full UPHIA 2025 summary results here:


-

 General7 days ago
Statement on Concerns Circulating Regarding a Member of Academic Staff
-

 Research2 weeks ago
Call for Makerere Staff PhD Completion Grant Applications, 2026-27
-

 General1 week ago
Press Statement: Incident Involving Death of a Student at Makerere University
-
 General2 weeks ago
Makerere Marathon 2026 – Running to Equip the Disability Support Center
-

 General1 week ago
JNLC Leadership Symposium Equips Young Leaders for Responsible and Transformative Leadership